Related Experiment Video
Updated: May 12, 2026

Percutaneous Endoscopic Unilateral-Approach Bilateral Decompression for Lumbar Spinal Stenosis
Published on: February 9, 2024
Stable low-grade degenerative spondylolisthesis does not adversely affect clinical outcome of full-endoscopic
Yi-Hao Liang1,2, Maria Auron2,3, Yi-Hyun Roh2
1Minimally Invasive Spine Center, Orthopedic Department of Guangdong Provincial Hospital of Chinese Medicine, Guangzhou University of Chinese Medicine, Guangzhou, China.

Background And Objectives:
The optimal surgical management of lumbar spinal stenosis (LSS) in the presence of stable low-grade degenerative spondylolisthesis remains a subject of ongoing debate. This study aimed to evaluate the clinical outcomes and radiological stability of Lumbar full-endoscopic unilateral laminotomy with bilateral decompression (LE-ULBD) in this patient population. Specifically, we sought to determine whether this minimally invasive approach compromises spinal stability or leads to progression of spondylolisthesis over time.
Materials And Methods:
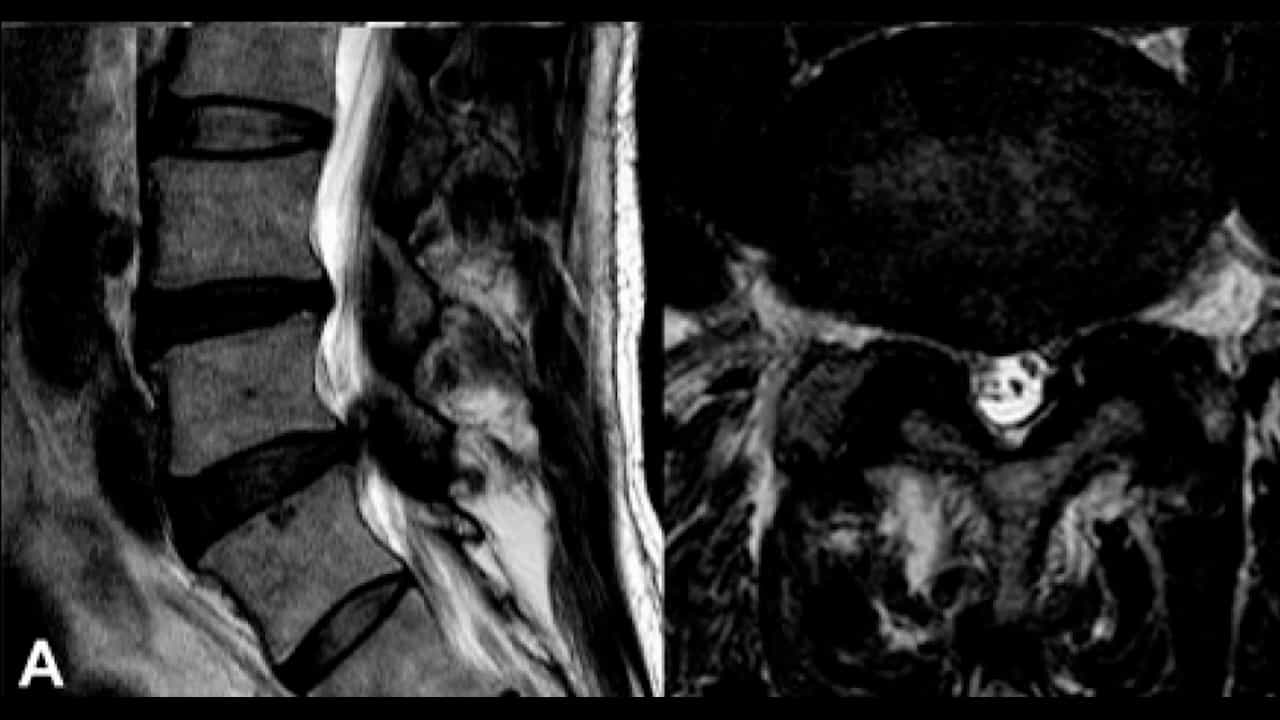
A total of 36 patients diagnosed with LSS and grade I degenerative spondylolisthesis who underwent LE-ULBD at the Minimally Invasive Spine Center between February 2019 and December 2023 were retrospectively reviewed. All patients completed at least 12 months of follow-up. Clinical outcomes were assessed preoperatively, at 12 months, and at the final follow-up using the visual analog scale for back pain (VAS back), visual analog scale for leg pain (VAS leg), and Oswestry Disability Index (ODI). Radiological evaluations included canal cross-sectional area (CSA), lumbar lordosis (LL), segmental lumbar lordosis (SLL), sagittal vertical axis (SVA), slip percentage (Slip%), pelvic tilt (PT), and other sagittal alignment parameters.
Results:
All clinical outcome measures demonstrated statistically significant improvement from baseline at both 12 months and final follow-up (p < 0.001 for all comparisons). Pain scores and functional disability were markedly reduced, indicating sustained clinical benefit of the procedure. Notably, the canal cross-sectional area (CSA) significantly increased at final follow-up (from 51.49 ± 28.41 mm2 preoperatively to 90.30 ± 50.60 mm2, p = 0.001), suggesting effective and lasting neural decompression. While lumbar lordosis and segmental lumbar lordosis angles did not exhibit statistically significant changes (p > 0.1), the slip percentage remained stable throughout the postoperative period (preoperative: 12.40 ± 5.33%; final follow-up: 11.99 ± 4.62%, p = 0.724), indicating no progression of vertebral slippage. Additionally, pelvic tilt improved significantly at the 12-month mark (from 20.37 ± 7.92° to 12.77 ± 8.47°, p < 0.001), although this change was not maintained at the final follow-up.Subgroup analysis (baseline: age, BMI, slip percentage, gender, lumbar lordosis) showed no significant differences in 12-month VAS back scores, VAS leg scores, or ODI changes across all subgroups (all p > 0.05), but lumbar lordosis subgroup had significant VAS back difference at the final follow-up(p = 0.03), marginal VAS leg trend, and no ODI difference.
Conclusion:
LE-ULBD appears to be a safe and effective option for carefully selected patients with stable grade I degenerative spondylolisthesis, providing durable symptom relief without compromising spinal stability. Future prospective studies with larger cohorts and extended follow-up are warranted to further substantiate these findings.