Related Experiment Video
Updated: May 12, 2026
Novel Mini-open Transforaminal Lumbar Interbody Fusion
Published on: June 6, 2025
Clinical and spinopelvic outcomes of Transforaminal versus Anterior Lumbar Interbody Fusion at L5-S1: a short-term
Silvia Suárez-Monsalve1,2,3, Nelcy Rodríguez Malagón1, Santiago Campos-Fajardo2
1Department of Clinic Epidemiology and Statistics, Pontificia Universidad Javeriana, Bogotá, Colombia.

Design:
Observational ambispective cohort.
Objectives:
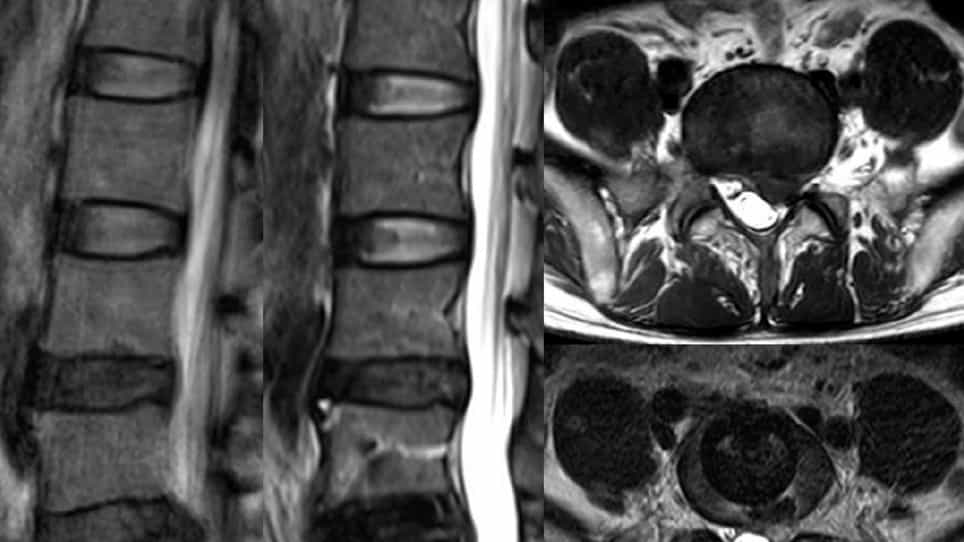
To compare the clinical and radiological effectiveness of Transforaminal Lumbar Interbody Fusion (TLIF) versus Anterior Lumbar Interbody Fusion (ALIF) in patients with chronic low back pain and single-level L5-S1 degenerative disc disease.
Methods:
An analytical ambispective cohort was conducted at two high-complexity private clinics in Bogotá, Colombia, between 2019 and 2024, including adults with chronic low back pain (≥3 months) and symptomatic L5-S1 degenerative disc disease undergoing minimally invasive fusion. The exposure was the surgical technique (TLIF vs. ALIF). The primary outcome was change in Visual Analog Scale (VAS) pain score, with secondary outcomes including changes in segmental (L5-S1) and regional (L1-S1) lumbar lordosis. Analyses included descriptive, bivariate, and multivariable models (multiple linear and ordinal logistic regression), adjusting for baseline imbalances such as BMI, facet joint signs, and spinal canal stenosis.
Results:
300 patients were included (120 TLIF, 180 ALIF), 61.7% female, mean age 45 years. Pain reduction was comparable (mean VAS reduction 6 points TLIF vs. 5 points ALIF; p = 0.0026; 95% CI: -1.19 to -0.25). Segmental lordosis gain was greater with ALIF (median 4.8° vs. 1.0°; p = 1.32 × 10⁻⁶; 95% CI: 2.31 to 5.38), and remained significant after adjustment (ALIF 3.83° greater; p = 2.4 × 10⁻⁶; 95% CI: 2.27 to 5.40), while regional lordosis changes did not differ (p = 0.161). Obesity appeared to modify the effect, with greater segmental correction in obese TLIF patients. Complication rates were low and similar (TLIF 5% vs. ALIF 7.2%).
Conclusions:
TLIF and ALIF provide comparable clinical improvement, while greater lordotic correction with ALIF does not yield additional meaningful pain relief. TLIF is a safe, efficient, and potentially cost-effective alternative, supporting its use as a first-line option for monosegmental L5-S1 fusion.