

Is an ED discharge safe after a single cardiac troponin: Analysis of the FAST-TRAC study
W Frank Peacock1, Christian Mueller2, Stefan D Anker3
1Baylor College of Medicine, Houston, TX, United States of America.

Background:
Serial Highly Sensitive Cardiac Troponin I (hscTnI) measures are commonly performed in patients presenting to the ED to exclude suspected Acute Myocardial Infarction (AMI). The previously published FAST-TRAC study prospectively enrolled patients presenting to the ED within 6 h of onset of symptoms consistent with suspected AMI. Our purpose was to evaluate the performance of a single hscTnI measurement, termed "one-and-done" using this cohort.
Methods:
In emergency department suspected acute coronary syndrome patients, serial blood samples were prospectively obtained for blinded hscTnI measurement (Access TnI, Beckman Coulter, Brea, CA) at 1, 2, 3-4, and 6-12 h after presentation. Patients were followed for 30-day Major Adverse Cardiac Events (MACE) determined by adjudicators blinded to hsTnI results.
Results:
Of 1520 patients enrolled, 113 (7.4%) were adjudicated as AMI, with 59% male, median (IQR: Interquartile Rank) age of 57 years (48-67), 66% White, 28% African American, and 3% Asian American. The overall median (IQR) time to first hscTnI draw after symptom onset was 3.67 (2.50-5.09) hours. Serial hscTnI and one-and-done strategies had comparable C-statistics for AMI; 0.95 (0.93-0.98) vs 0.93 (0.91-0.96), respectively. In no circumstance did the 99th percentile cutpoint meet an adequate rule-out AMI sensitivity of 99%. Serial measures using either the 10% or 20% Coefficient of Variation (CV) Level of Quantification (LOQ) cutpoint had the same sensitivity of 99.1%, but the 10% CV LOQ had higher specificity, 61.7%, (95% CI = 59.1-64.2). For a "one-and-done" strategy, only the 20% CV LOQ, with a sensitivity of 99.1 (95.2-99.8), met the 99% sensitivity goal. Using the 20% CV LOQ, a "one-and-done" strategy would have immediately ruled out 39% (n = 550) of patients for AMI, with only 61% (n = 857) requiring additional serial hscTnI testing.
Conclusions:
A "one-and-done" strategy using a hscTnI <20% CV LOQ provides the most efficient AMI rule-out performance.
Registration:
NCT00880802.

Related Concept Videos
 01:20
Blood Studies for Cardiovascular System I: Cardiac Biomarkers
The essential diagnostic tools for detecting myocardial necrosis and monitoring individuals suspected of having acute coronary syndrome (ACS) include:
Troponins
Troponins, particularly cardiac troponins I and T, are the most precise and sensitive markers of myocardial injury. They are detectable within 4-6 hours of myocardial injury and remain...
 01:30
Acute Coronary Syndrome III: Diagnostic Studies
 01:30
Acute Coronary Syndrome I: Introduction
 01:28
Acute Coronary Syndrome IV: Interprofessional Care
 01:19
Acute Coronary Syndrome II: Pathophysiology and Clinical Manifestations
 01:26
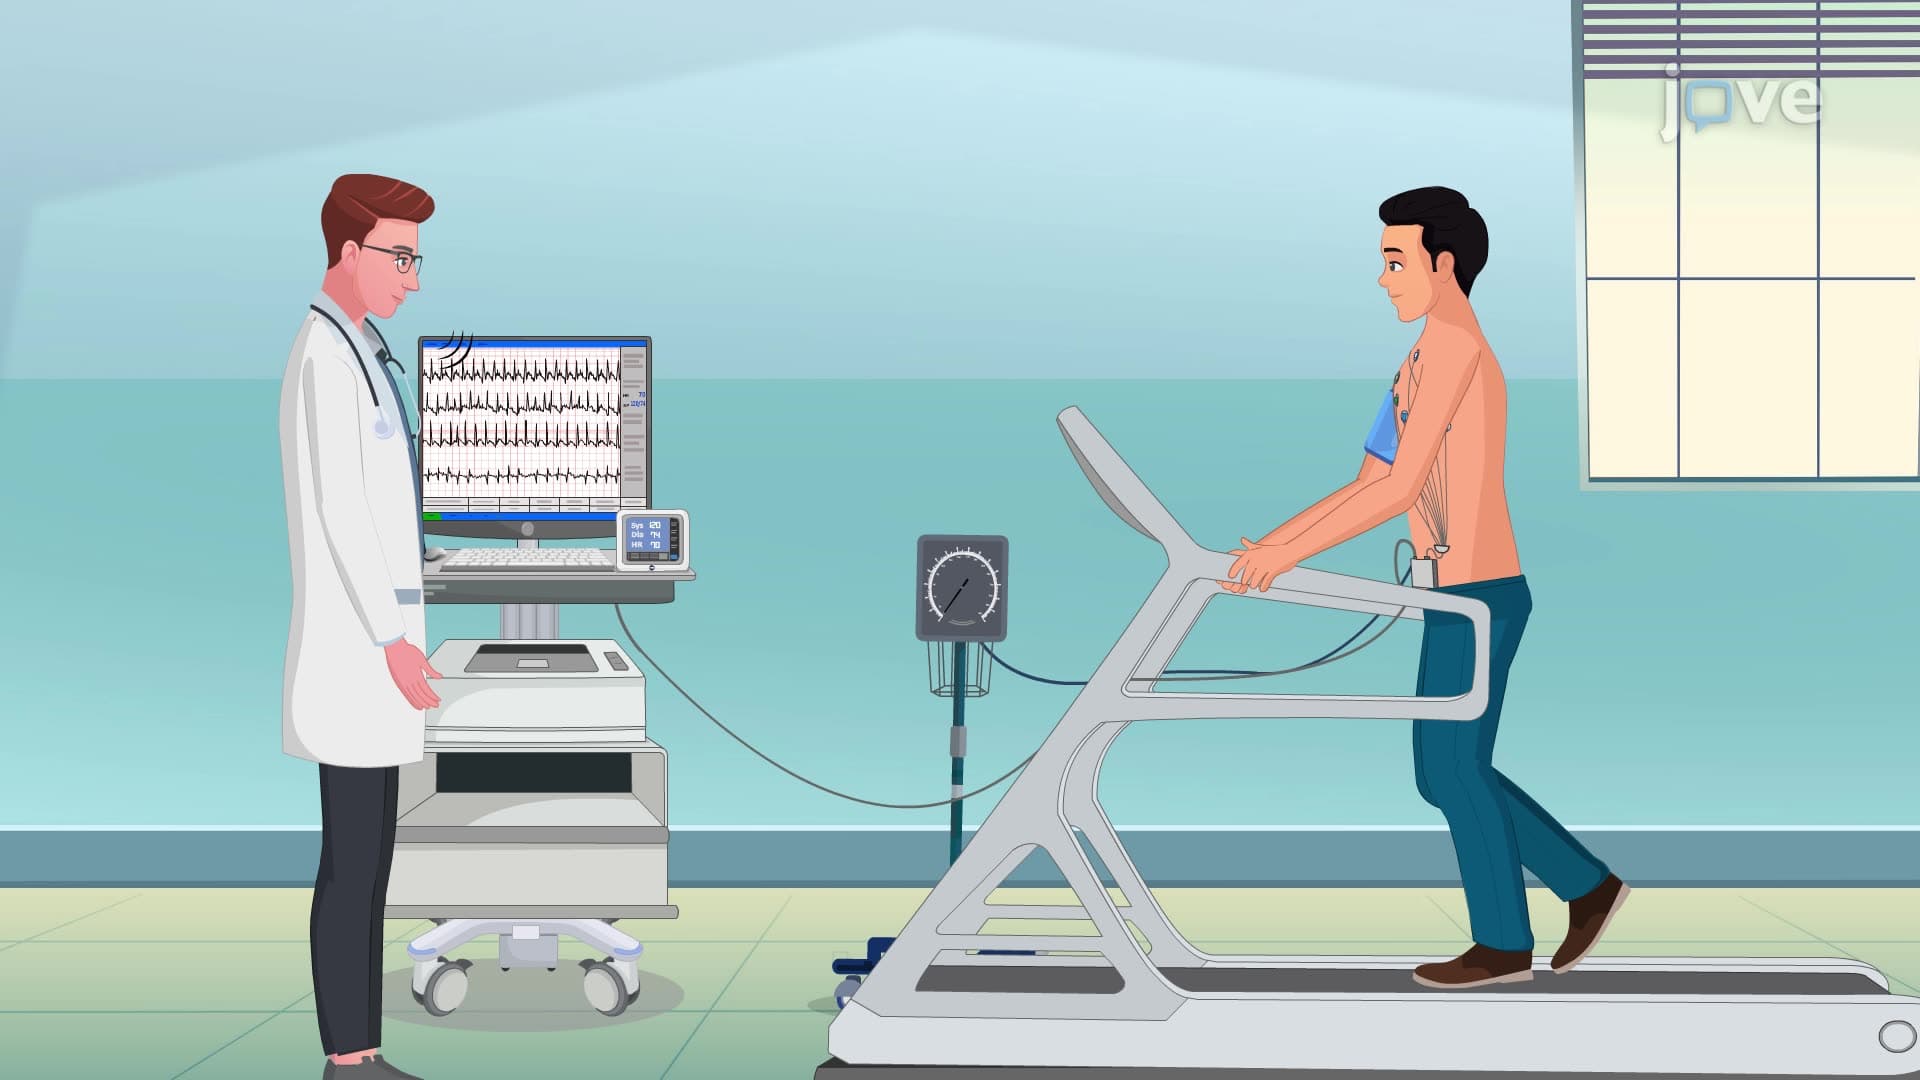
Exercise Stress Test
Exercise stress testing, commonly known as a treadmill test, is a noninvasive procedure used to evaluate cardiovascular function and diagnose heart conditions.
Definition
An exercise stress test measures the heart's response to exertion using a treadmill or stationary bicycle. Chest electrodes record the heart's electrical activity through an ECG, and blood pressure is monitored regularly.
Purposes