Related Experiment Video
Updated: May 13, 2026


Measuring Carbon Content in Airway Macrophages Exposed to Carbon-Containing Particulate Matters
Published on: July 12, 2024
Aerosol deposition in the lung as a biomarker in asthma and chronic obstruction
Hugo Öhrneman1, Andrei Malinovschi2, Gui-Hong Cai3
1Division of Ergonomics and Aerosol Technology, Department of Design Sciences, Lund University, Box 118, Lund, 221 00 LUND, Sweden.

Background:
The objective of this study was to explore the potential of Airspace Dimension Assessment (AiDA) to rapidly determine the type and severity of airway obstruction, detect emphysema in individuals with chronic airflow limitation (CAL), and distinguish it from non-emphysematous obstruction, asthma, and absence of respiratory disease with normal spirometry.
Methods:
Among the 744 participants measured with AiDA within the Swedish CArdioPulmonary bioImage Study (SCAPIS) cohort, 40 had asthma, and 34 had a CAL (defined by a post-bronchodilator FEV1/FVC < 0.7), whereof 12 had CT-detected emphysema. AiDA measurements were compared across these groups and to 111 healthy controls (never-smokers with normal spirometry and no history of respiratory disease).
Results:
Subjects with CAL had significantly larger distal airspaces radii (median rAiDA=298 μm) than controls (rAiDA=278 μm, p < 0.001), but no significant difference was observed in asthmatics (rAiDA=273 μm, p = 0.79). Subjects with CT-detected emphysema in the CAL group displayed further differentiation from the control (rAiDA=349 μm, p < 0.001), while those without emphysema displayed no significant increase. Unlike rAiDA, neither low attenuation volume nor 15th percentile density could clearly distinguish between obstruction and radiologist-assessed emphysema. In addition, the zero-second particle recovery (R0), which is theorized to reflect conducting airway dysfunction, was decreased in both asthmatics (R0 = 0.41, p = 0.011), and in the CAL group (R0 = 0.45, p = 0.020) when compared to controls (R0 = 0.56).
Conclusions:
These findings display AiDA's potential in identifying emphysema as well as obstructive airway disease. The absence of an increased distal airspace radius in asthmatics confirm that rAiDA is a measure of the distal airspaces, unaffected by abnormalities in the conducting airways. However, the decreased R0 in both asthma and CAL suggests that R0 does reflect conducting airway abnormality.


Related Concept Videos
 01:24
Chronic Obstructive Pulmonary Disease III: Chronic Bronchitis Features
 01:20
Chronic Obstructive Pulmonary Disease-II: Pathophysiology
Chronic Inflammation
 01:23
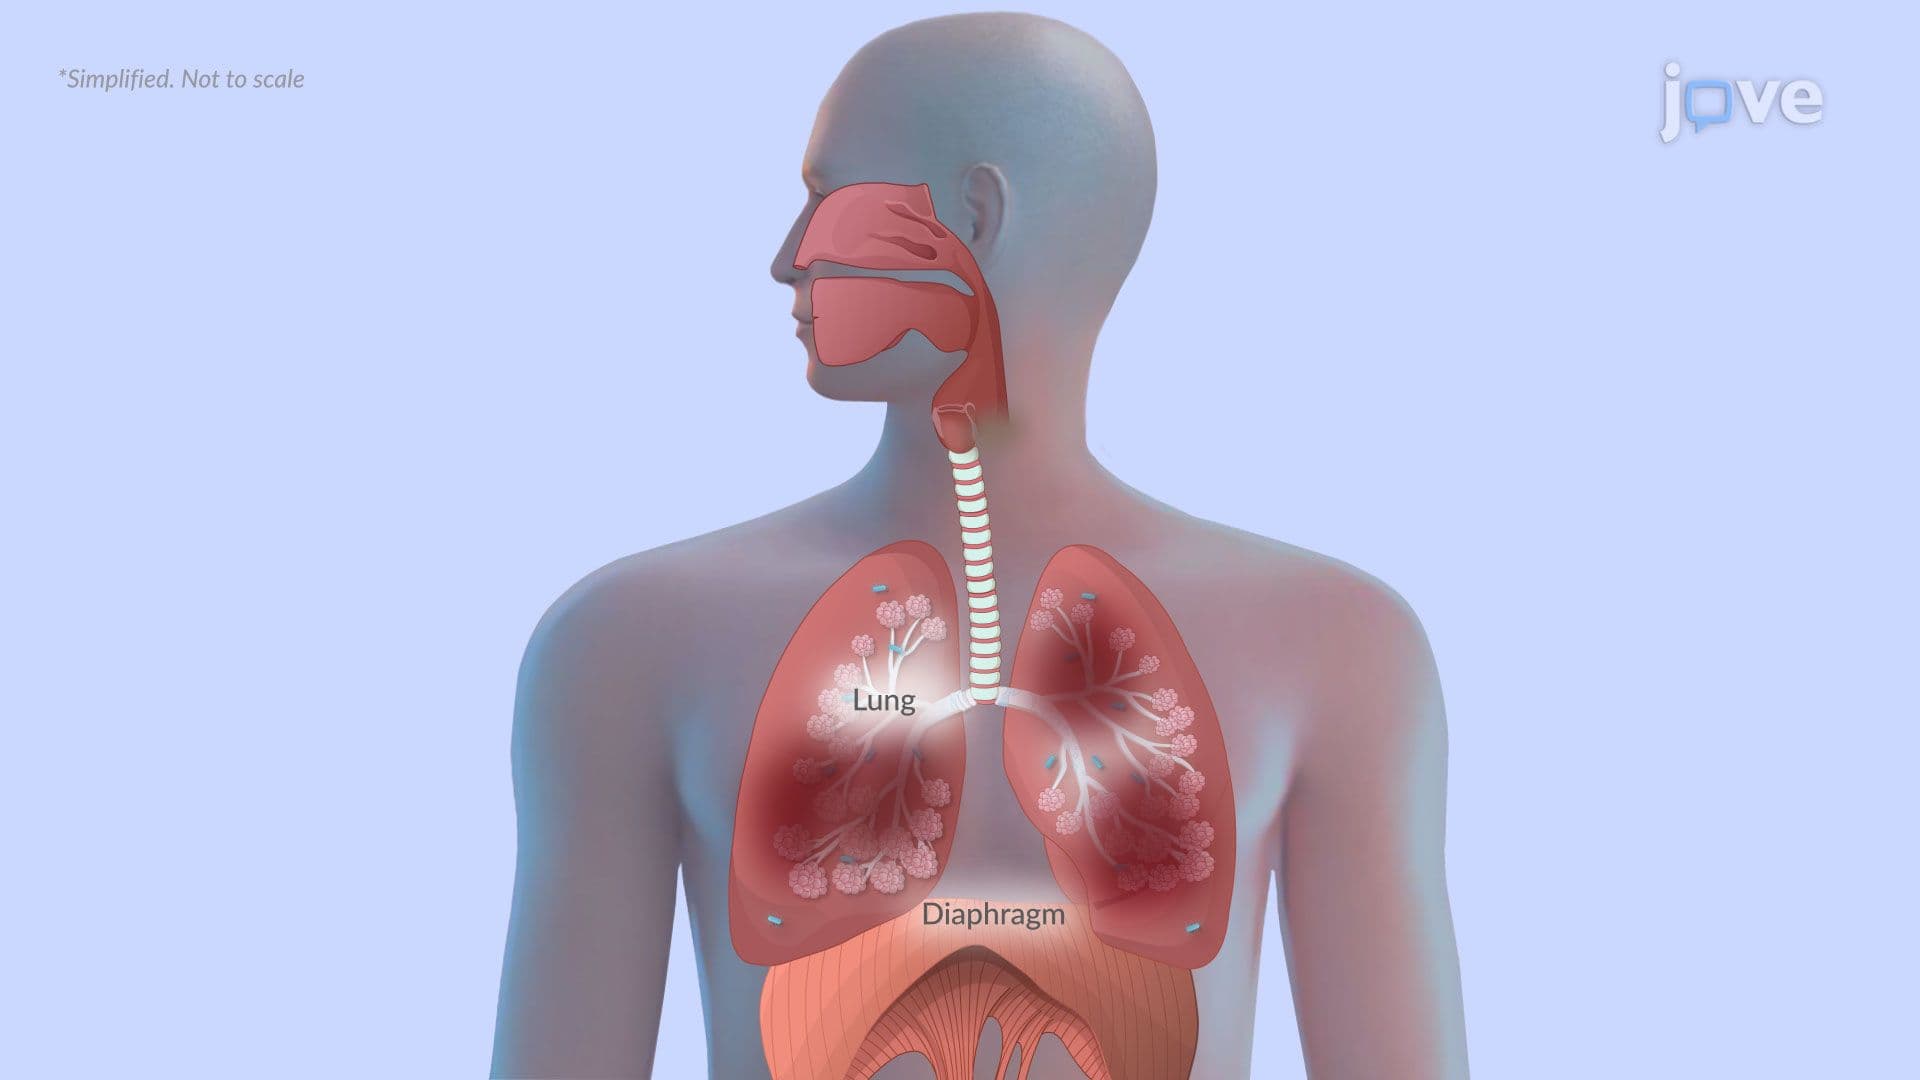
Chronic Obstructive Pulmonary Disease I: Introduction
 01:27
Chronic Obstructive Pulmonary Disease-IV: Assessement and Diagnostic Studies
Medical History
 01:23
Chronic Obstructive Pulmonary Disease II: Emphysema
 01:24
Chronic Obstructive Pulmonary Disease
Smoking is a primary risk factor for COPD, with over 80% of patients having a history of it. Patients typically experience progressive dyspnea or labored breathing, frequent coughing, and recurrent pulmonary infections. Many eventually succumb to respiratory failure, characterized by...