Related Experiment Video
Updated: Jul 12, 2026
Fluorescence-Activated Cell Sorting-Radioligand Treated Tissue (FACS-RTT) to Determine the Cellular Origin of Radioactive Signal
Published on: September 10, 2021
A radioimmunoassay for measurement of 3,3',5'-triiodothyronine (reverse T3)

A highly specific antiserum to 3,3',5'-triiodothyronine (reverse T(3), rT(3)) was prepared by immunization of rabbits with D,L-rT(3)-human serum albumin conjugate. Of the various thyroid hormone derivatives tested, only 3,3'-diiodothyronine (3,3'-T(2)) cross-reacted significantly (10%) with rT(3)-binding sites on the antiserum, while thyroxine (T(4)) and triiodothyronine (T(3)) cross-reacted by less than 0.1%. The antiserum was used in a simple, sensitive, precise, and reproducible radioimmunoassay (RIA) for measurement of rT(3) in ethanolic extracts of serum. The dose-response curves of inhibition of the binding of [(125)I]rT(3) to antibody obtained by serial dilutions of serum extracts were essentially parallel to the standard assay curve. Recovery of nonradioactive rT(3) added to serum before extraction averaged 93%. Serum rT(3) concentrations were found to be (mean+/-SD) 41+/-10 ng/100 ml in 27 normal subjects, 103+/-49 ng/100 ml in 22 hyperthyroid patients, 19+/-9 ng/100 ml in 12 hypothyroid patients, and 54+/-7 ng/100 ml in five subjects with elevated serum thyroxine-binding globulin: the values in each of the latter three groups of individuals were significantly different from normal. Reverse T(3) was detected regularly in normal or supranormal concentrations in serum of 12 hypothyroid patients rendered euthyroid or mildly hyperthyroid by treatment with synthetic T(4). It is suggested that serum rT(3) values noted here should be taken to reflect the relative changes in serum rT(3) rather than its absolute values in health and thyroid disease. True serum rT(3) may be somewhat different because: (a) D.L-rT(3) employed in the standard curve and L-rT(3) present in human serum may react differently with anti-D,L-rT(2). (b) Even though 3,3'-T(2), which cross-reacted 10% in rT(3) RIA, has been considered unlikely to be present in human serum, it may circulate in low levels. (c) Cross-reaction of T(4) in rT(3) RIA of 0.06% although small, could contribute to RIA estimates of rT(2); the effect of T(4) would be particularly important in case of serum of hyperthyroid patients. Thus, serum rT(3) concentration in hyperthyroid patients averaged 89+/-48 mug/100 ml after correction for cross-reaction effects of T(4): this value was about 14% lower than that before correction (see above). Serum rT(3) concentration in cord sera of seven newborns averaged 136+/-19 ng/100 ml; it was clearly elevated and within the range of values seen in hyperthyroid patients. This was the case when the mean T(4) concentration in the newborn cord sera was moderately higher than normal and about one-half that in hyperthyroid patients, whereas serum T(3) was markedly below the normal adult level. A Pronase hydrolysate of thyroglobulin prepared from pooled normal thyroid glands contained 0.042, 3.0, and 0.16 mug/mg protein of rT(3), T(4), and T(3), respectively. The various data suggest that: (a) rT(3) is a normal component of human serum and thyroglobulin: (b) peripheral metabolism of T(4) is an important source of the rT(3) present in serum: (c) peripheral conversion of T(4) to T(3) and rT(3) may not necessarily be a random process.
A highly specific antiserum to 3,3',5'-triiodothyronine (reverse T(3), rT(3)) was prepared by immunization of rabbits with D,L-rT(3)-human serum albumin conjugate. Of the various thyroid hormone derivatives tested, only 3,3'-diiodothyronine (3,3'-T(2)) cross-reacted significantly (10%) with rT(3)-binding sites on the antiserum, while thyroxine (T(4)) and triiodothyronine (T(3)) cross-reacted by less than 0.1%. The antiserum was used in a simple, sensitive, precise, and reproducible radioimmunoassay (RIA) for measurement of rT(3) in ethanolic extracts of serum. The dose-response curves of inhibition of the binding of [(125)I]rT(3) to antibody obtained by serial dilutions of serum extracts were essentially parallel to the standard assay curve. Recovery of nonradioactive rT(3) added to serum before extraction averaged 93%. Serum rT(3) concentrations were found to be (mean+/-SD) 41+/-10 ng/100 ml in 27 normal subjects, 103+/-49 ng/100 ml in 22 hyperthyroid patients, 19+/-9 ng/100 ml in 12 hypothyroid patients, and 54+/-7 ng/100 ml in five subjects with elevated serum thyroxine-binding globulin: the values in each of the latter three groups of individuals were significantly different from normal. Reverse T(3) was detected regularly in normal or supranormal concentrations in serum of 12 hypothyroid patients rendered euthyroid or mildly hyperthyroid by treatment with synthetic T(4). It is suggested that serum rT(3) values noted here should be taken to reflect the relative changes in serum rT(3) rather than its absolute values in health and thyroid disease. True serum rT(3) may be somewhat different because: (a) D.L-rT(3) employed in the standard curve and L-rT(3) present in human serum may react differently with anti-D,L-rT(2). (b) Even though 3,3'-T(2), which cross-reacted 10% in rT(3) RIA, has been considered unlikely to be present in human serum, it may circulate in low levels. (c) Cross-reaction of T(4) in rT(3) RIA of 0.06% although small, could contribute to RIA estimates of rT(2); the effect of T(4) would be particularly important in case of serum of hyperthyroid patients. Thus, serum rT(3) concentration in hyperthyroid patients averaged 89+/-48 mug/100 ml after correction for cross-reaction effects of T(4): this value was about 14% lower than that before correction (see above). Serum rT(3) concentration in cord sera of seven newborns averaged 136+/-19 ng/100 ml; it was clearly elevated and within the range of values seen in hyperthyroid patients. This was the case when the mean T(4) concentration in the newborn cord sera was moderately higher than normal and about one-half that in hyperthyroid patients, whereas serum T(3) was markedly below the normal adult level. A Pronase hydrolysate of thyroglobulin prepared from pooled normal thyroid glands contained 0.042, 3.0, and 0.16 mug/mg protein of rT(3), T(4), and T(3), respectively. The various data suggest that: (a) rT(3) is a normal component of human serum and thyroglobulin: (b) peripheral metabolism of T(4) is an important source of the rT(3) present in serum: (c) peripheral conversion of T(4) to T(3) and rT(3) may not necessarily be a random process.


Related Concept Videos
 01:20
Synthesis and Regulation of Thyroid Hormones
Upon reaching the thyroid gland, TSH stimulates the follicular cells' active uptake of iodide ions from the blood. The ions diffuse to the apical surface of the cells and are oxidized to iodine. The iodine is then...
 01:26
Therapeutic Drug Monitoring: Drug Analysis Methods
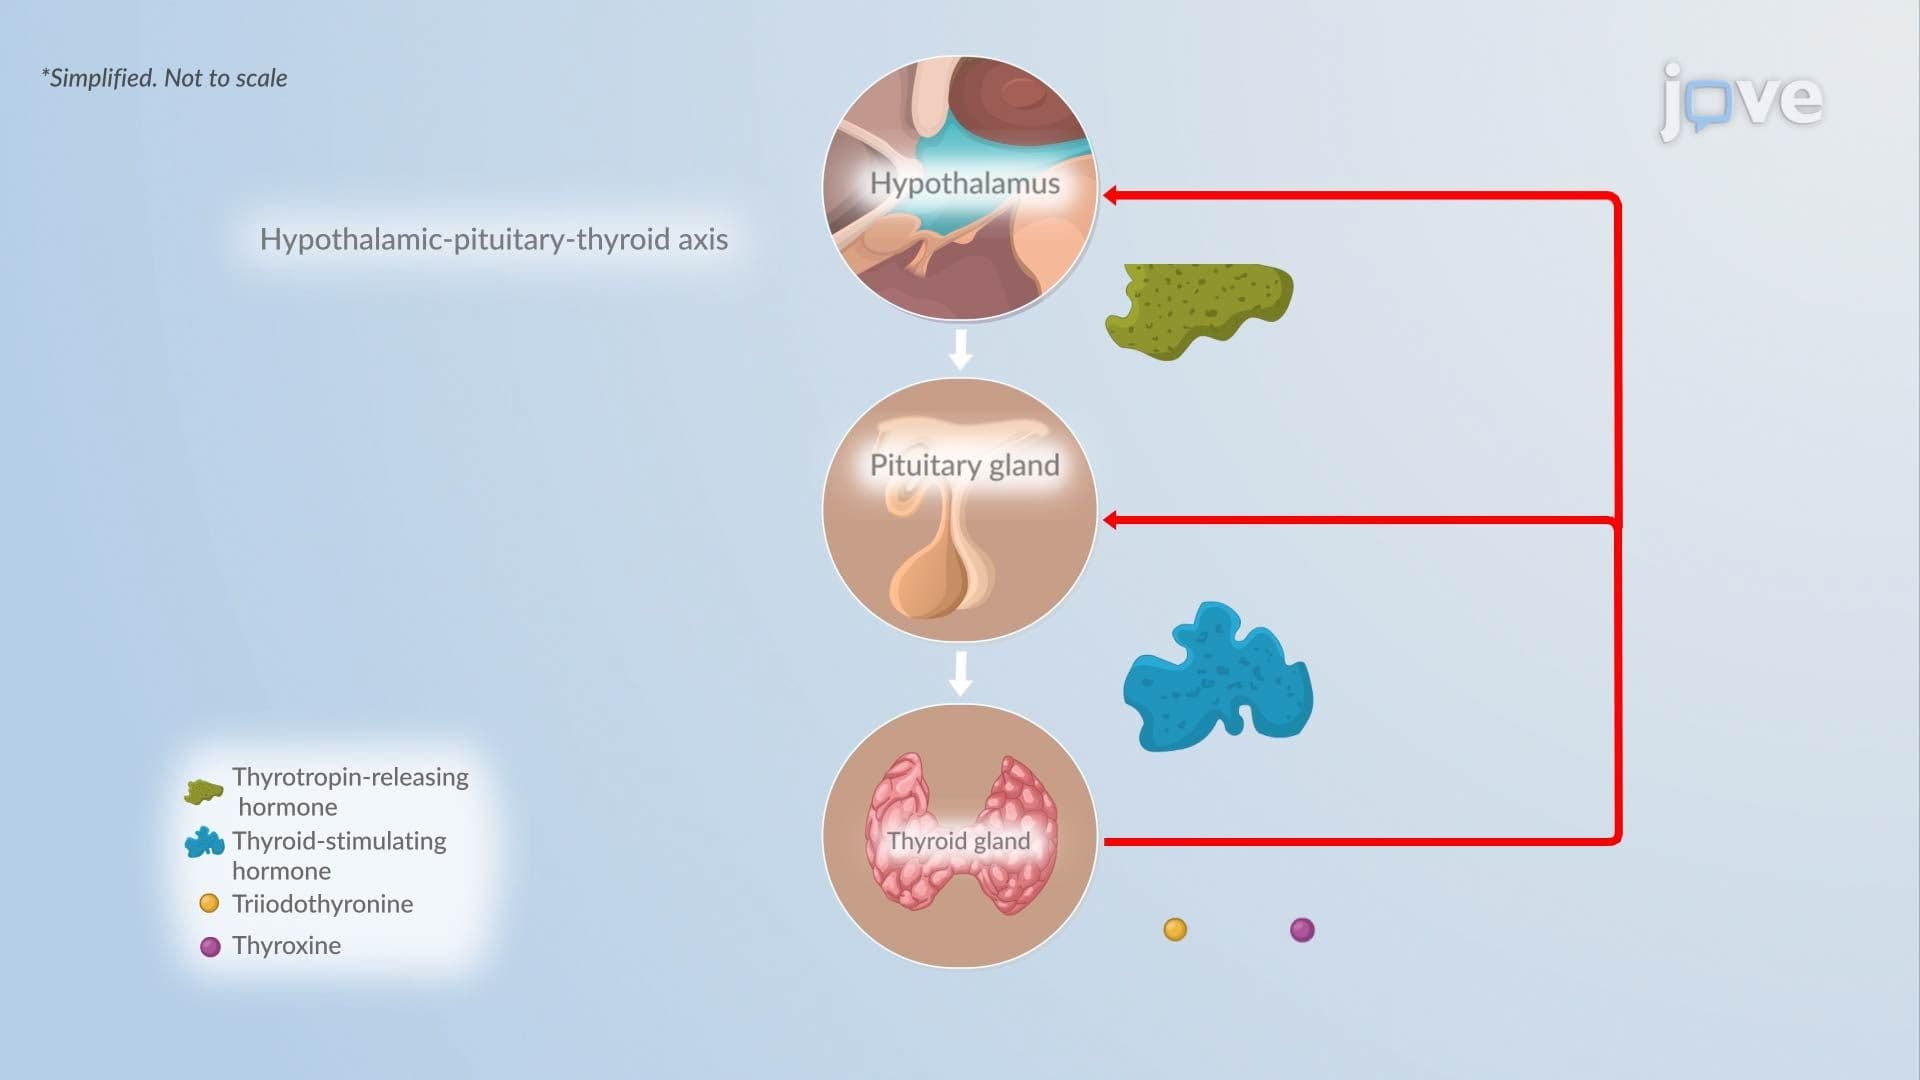 01:25
Hyperthyroidism I: Introduction
 01:27
Goiter