Related Experiment Video
Updated: May 14, 2026
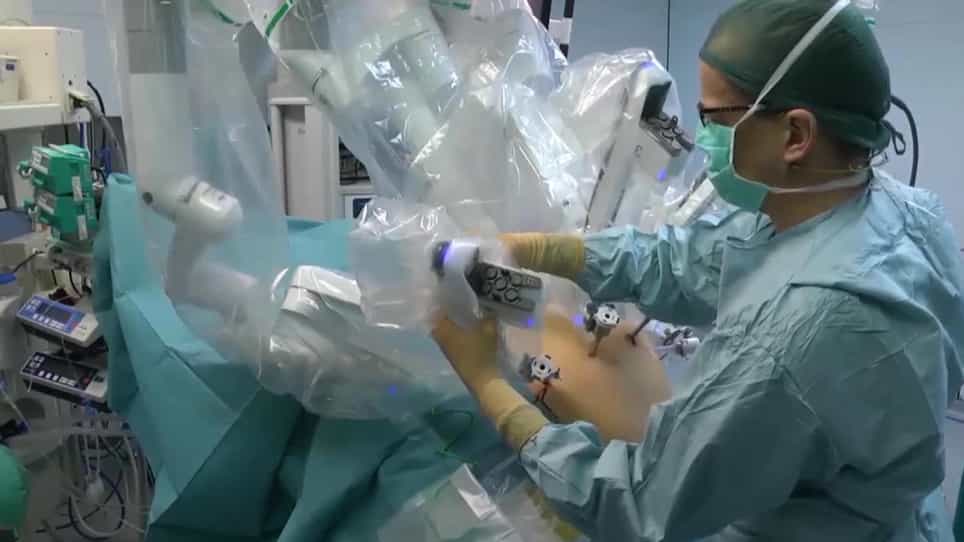

Robot-Assisted Radical Antegrade Modular Pancreatosplenectomy Including Resection and Reconstruction of the Spleno-Mesenteric Junction
Published on: January 3, 2020
Neoadjuvant Chemotherapy and Stereotactic Body Radiation Therapy in Patients with Early-Onset Pancreatic Cancer:
Shuchi Sehgal1, Abhinav V Reddy2, Suqi Ke1
1Department of Radiation Oncology and Molecular Radiation Sciences, Johns Hopkins University School of Medicine, Baltimore, MD 21287, USA.

Abstract:
Purpose/Objective: This purpose of this study is to report on a cohort of patients with Early-onset pancreatic cancer (EOPC) (age < 55 years) who were treated with neoadjuvant chemotherapy and stereotactic body radiation therapy (SBRT) with or without surgical resection. Materials/Methods: This was a single-institution, retrospective review of patients with EOPC that was staged as either borderline resectable (BRPC) or locally advanced (LAPC) based on NCCN criteria and who were treated with upfront chemotherapy followed by SBRT, with or without subsequent surgical resection. Endpoints included overall survival (OS), local progression-free survival (LPFS), distant metastasis-free survival (DMFS), progression-free survival (PFS), and treatment-related toxicity. Results: From 2016 to 2021, 47 patients met the inclusion criteria. The median age was 50.4 years (range, 36.4-54.7 years). The median duration of induction chemotherapy was 4 months (range, 2.5-9.0 months). The SBRT dose for the majority (46/47, 97.9%) of patients was 33 Gy in five fractions. Surgical resection was performed in 33 patients (70.2%). The median OS, LPFS, DMFS, and PFS were 14.2 months, 11.6 months, 8.9 months, and 8.1 months respectively. Six-month and 1-year LPFS were 88.3% and 45.4%, respectively. Chemotherapy duration (≥4 months) was associated with improved median OS (16.5 vs. 10.1 months, p = 0.005), LPFS (10.1 vs. 4.9 months, p = 0.002), DMFS (9.7 vs. 5.2 months, p = 0.014), and PFS (9.7 vs. 5.2 months, p = 0.020). The normalization of CA 19-9 (≤34 vs. >34 U/mL) after chemotherapy was associated with improved median DMFS (not reached vs. 5.6 months, p = 0.003) and PFS (11.3 vs. 5.6 months, p = 0.022). Grade 3+ rates of chemotherapy and radiation-related toxicity were 14.9% and 2.1% respectively. The Clavien-Dindo 3b toxicity rate was 3.0%. Conclusions: In EOPC, an induction chemotherapy duration ≥4 months and the normalization of CA 19-9 after chemotherapy were associated with improved outcomes, suggesting a role for extended durations of systemic therapy titrated to CA 19-9 response before transitioning to local therapy. The high rate of local failure and the low rate of grade 3+ toxicity also suggest a role for intensifying local therapy in this population.

