Related Experiment Video
Updated: May 14, 2026
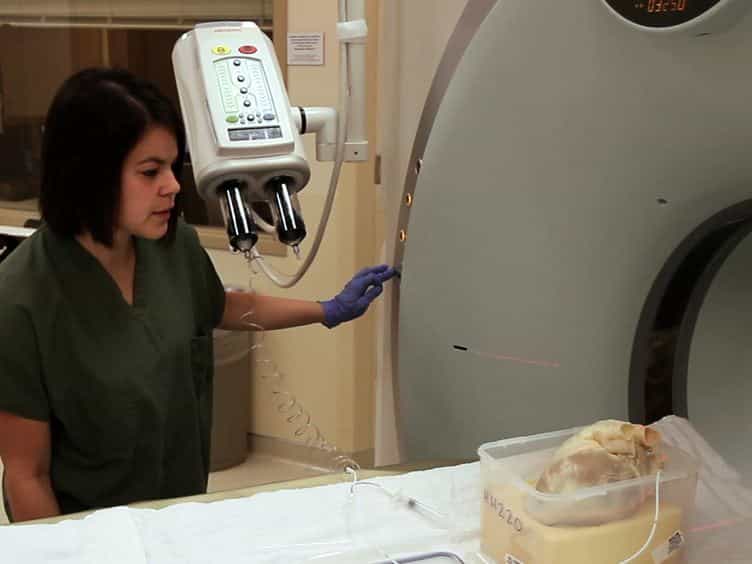
Anatomical Reconstructions of the Human Cardiac Venous System using Contrast-computed Tomography of Perfusion-fixed Specimens
Published on: April 18, 2013
Risk Factors, Not Low-Osmolar Contrast, Predict Acute Kidney Injury Following Contrast-Enhanced Computed Tomography:
1Medicine, University of the West Indies, Kingston, JAM.

Background:
The safety of a low-osmolar contrast agent, iopromide (Ultravist, Bayer, Leverkusen, Germany), currently being used is unknown. This study aimed to evaluate whether iopromide use was associated with acute kidney injury (AKI) in patients undergoing contrast-enhanced computed tomography (CT) imaging.
Methods:
This retrospective cohort study included 1915 participants who had CT scans during 2023. AKI was defined as an absolute rise in serum creatinine (sCr) ≥26.5 µmol/L within 48 hours or ≥1.5 times increase from baseline within seven days. The differences in the means of pre-CT and post-CT sCr with and without contrast exposure were determined using the independent samples t-test and variance ratio (F-test). Paired t-test was used to find the mean difference between pre- and post-CT creatinine levels. Pearson's chi-squared (X2) test, along with pairwise correlation analysis, was applied to find the relationship between contrast exposure and AKI as well as AKI and renal outcomes. To find out the independent predictors of contrast-associated acute kidney injury (CA-AKI), a multivariable binary logistic regression model was conducted.
Results:
Of 1915 participants who underwent CT imaging, 869 (45.4%) were exposed to contrast, while 1046 (54.6%) were not exposed to contrast. No statistically significant difference was found between exposed and non-exposed groups for the development of AKI (10.6% vs. 8.8%; p=0.188). Both groups were found to have lower mean post-procedure sCr compared to pre-procedure sCr (-2.2 and -12.7 µmol/L, respectively). The AKI occurrence was not directly associated with whether patients were exposed to iopromide or not (r=0.03; p=0.178). Noteworthy risk factors identified were active malignancy (aOR: 2.43; 95% CI: 1.54-3.84; p<0.001), pre-existing renal dysfunction (aOR: 2.31; 95% CI: 1.27-4.18; p=0.006), and cardiac disease (aOR: 2.09; 95% CI: 1.22-3.58; p=0.007).
Conclusion:
Use of low-osmolar contrast agents for CT imaging was not independently associated with AKI. Our results suggest that contrast-enhanced CT may be considered when clinically indicated without unnecessary delay while acknowledging that individual patient risk assessment remains essential. Greater emphasis should instead be placed on identifying and optimizing certain factors, like active malignancy, pre-existing renal dysfunction, and cardiac diseases, to prevent CA-AKI.

Related Concept Videos
 01:30
Acute Kidney Injury IV: Diagnostic Studies and Prevention
 01:22
Acute Kidney Injury I: Introduction
 01:29
Acute Kidney Injury II: Pathophysiology
 01:29
Acute Kidney Injury III: Clinical Manifestations
 01:27
Imaging Studies III: Computed Tomography
 01:19
Imaging Studies VII: Vascular Imaging