Related Experiment Video
Updated: May 15, 2026

Full-Endoscopic Interlaminar Approach for Decompression of Lateral Recess Stenosis
Published on: February 24, 2023
Upright MRI Follow-Up for Decompression and Interlaminar Stabilization in Low-Grade L4/L5 Spondylolisthesis Suggests
Julia E Reich1,2, Andrei Slavici2, Juan M Vinas-Rios3,4
1Department of Otolaryngology, Head and Neck Surgery, J.W. Goethe University Hospital, Frankfurt am Main, Germany julia.reich@unimedizin-frankfurt.de.

Purpose:
While spinal fusion is the standard treatment for symptomatic low-grade spondylolisthesis, evidence on motion-preserving alternatives such as decompression with interlaminar stabilization (D+ILS) remains limited. This study aims to descriptively evaluate clinical and radiological outcomes after D+ILS at L4/L5 under strict inclusion criteria, with a specific focus on dynamic spinal assessment using upright magnetic resonance imaging (MRI).
Methods:
This prospective observational study involved 30 patients with degenerative low-grade spondylolisthesis at L4/L5 treated with D+ILS using the Coflex interlaminar stabilization device. Further inclusion criteria included symptomatic spinal canal stenosis, significant pain relief following facet joint injections, maintained disc height, and unsuccessful conservative treatment. Outcomes were assessed using functional upright MRI and validated questionnaires.
Results:
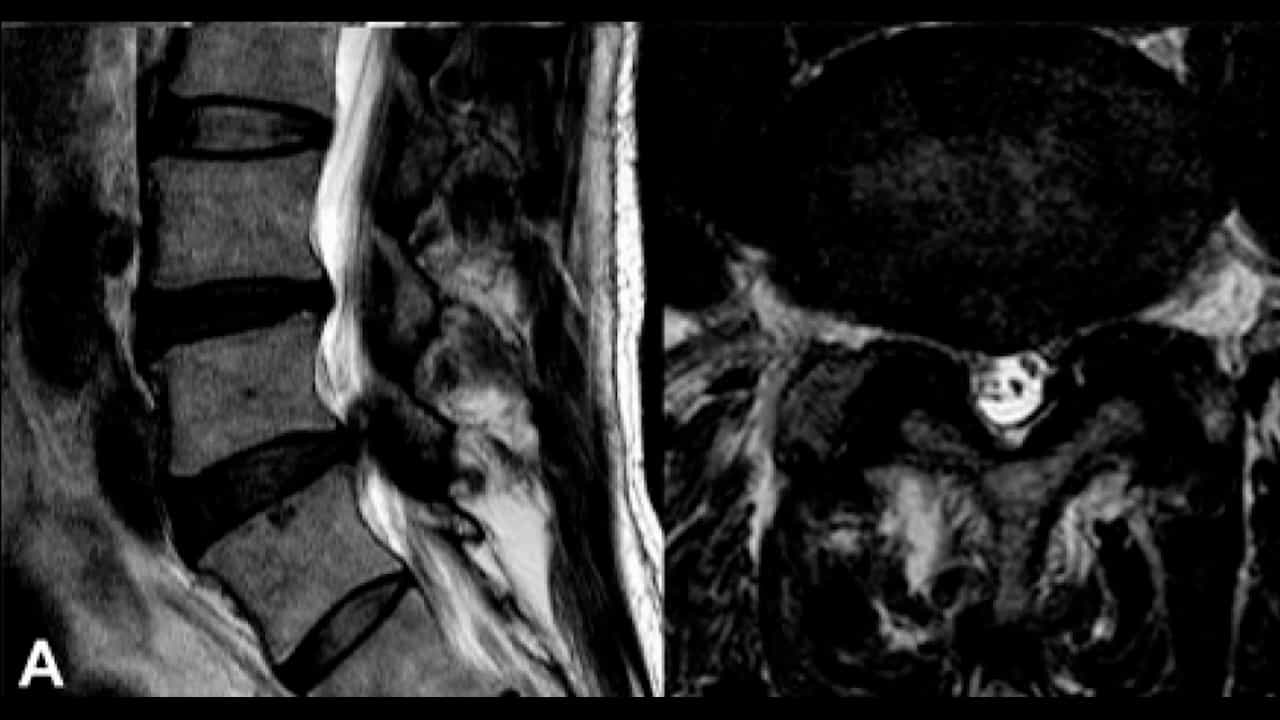
The cohort consisted of 13 women and 17 men with a mean age of 69 ± 9 years and an average follow-up of 43 ± 7 months. At last follow-up, upright MRI showed preserved segmental alignment without signs of increased translational motion, along with reductions in spinal canal stenosis and facet cysts. Radiological progression of facet joint osteoarthritis and disc degeneration was mild. Spinopelvic parameters and multifidus muscle morphology remained largely unchanged. Clinically, there were significant improvements in pain, functional disability, and ambulation. One patient (3%) required reoperation for symptomatic adjacent segment degeneration.
Conclusion:
This study is the first to assess D+ILS in a strictly selected cohort using upright MRI to evaluate postoperative mechanics at mid-term follow-up under physiological load. Our findings suggest that D+ILS may be a feasible motion-preserving treatment concept in carefully selected patients with stable L4/L5 spondylolisthesis. However, given the exploratory design and small cohort, these observations should be interpreted as descriptive and hypothesis generating and warrant confirmation in controlled trials.