Related Experiment Video
Updated: May 15, 2026
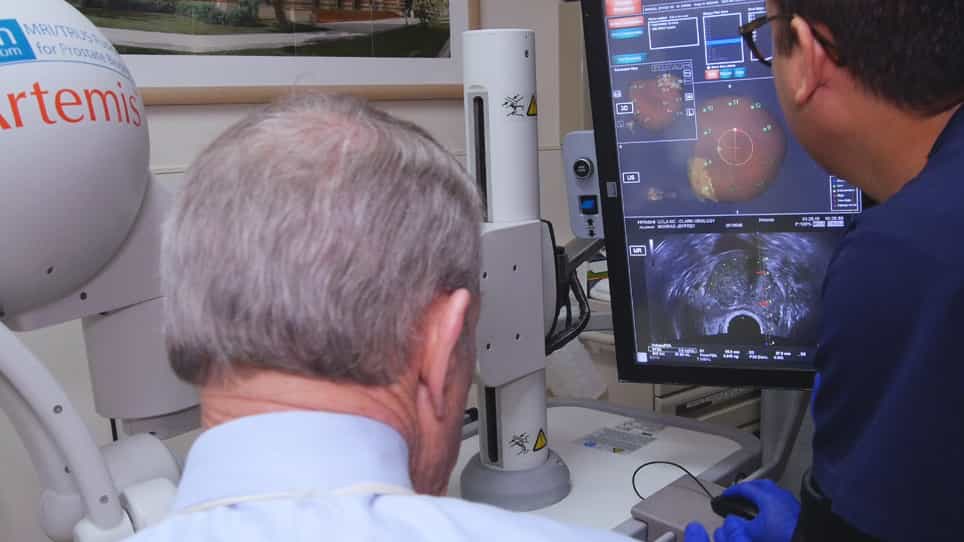

Use of MRI-ultrasound Fusion to Achieve Targeted Prostate Biopsy
Published on: April 9, 2019
Imaging-based clinical decision tree enables risk stratification of extraprostatic extension before radical
Charlie A Hamm1,2, Tim Rüterhenke3, Georg L Baumgärtner3
1Department of Radiology, Charité-Universitätsmedizin Berlin, Corporate Member of Freie Universität Berlin and Humboldt-Universität zu Berlin, Berlin, Germany. charlie.hamm@charite.de.

Objectives:
Extraprostatic extension (EPE) significantly impacts surgical planning for prostate cancer (PCa) patients, influencing nerve-sparing surgery and neoadjuvant therapy decisions. However, Likert-scale-based radiological (r)EPE assessment lacks sufficient diagnostic accuracy for reliable clinical decision-making. Therefore, the aim was to evaluate rEPE scoring alongside clinical parameters to develop a clinically feasible decision tree for preoperative risk stratification.
Methods:
This retrospective single-center study included 429 consecutive PCa patients undergoing radical prostatectomy between January 2012 and October 2018. All patients underwent multiparametric MRI with PI-RADS scoring and rEPE grading (grades 0-3). Clinical parameters included PSA density (PSAD) and ISUP grade group (GG) at biopsy. Univariate and multivariate logistic regression identified predictors of EPE. A clinical decision tree was developed using binary classification to stratify patients into risk groups.
Results:
EPE was confirmed in 145 patients (33.8%). Multivariate analysis identified rEPE grade (OR 2.64, p < 0.001) and GG at biopsy (OR 1.41, p < 0.001) as independent predictors. The decision tree assigned 48% of patients to the high-risk (rEPE grade 3: 89% EPE risk) and low-risk group (rEPE < 3 + PSAD < 0.2 ng/mL² + GG < 4: 13% EPE risk), while 52% showed intermediate risk (28-45% EPE risk).
Conclusions:
The developed decision tree combining MRI-derived rEPE grading, PSAD, and biopsy GG enables reliable identification of patients at high and low risk for EPE. This tool supports informed decision-making regarding nerve-sparing surgery and neoadjuvant therapy, potentially contributing to personalized treatment planning.
Critical Relevance Statement:
Decision tree combining routine MRI-based and clinical markers reliably stratifies prostate cancer patients into high-risk and low-risk groups for EPE, supporting personalized surgical planning.
Key Points:
EPE affects surgical planning decisions in prostate cancer patients. Combining EPE grade at MRI, PSAD, and biopsy grade improves risk stratification. The developed decision tree reliably stratified every second patient into distinct EPE-risk groups, potentially improving personalized surgical planning.


