Related Experiment Video
Updated: May 16, 2026

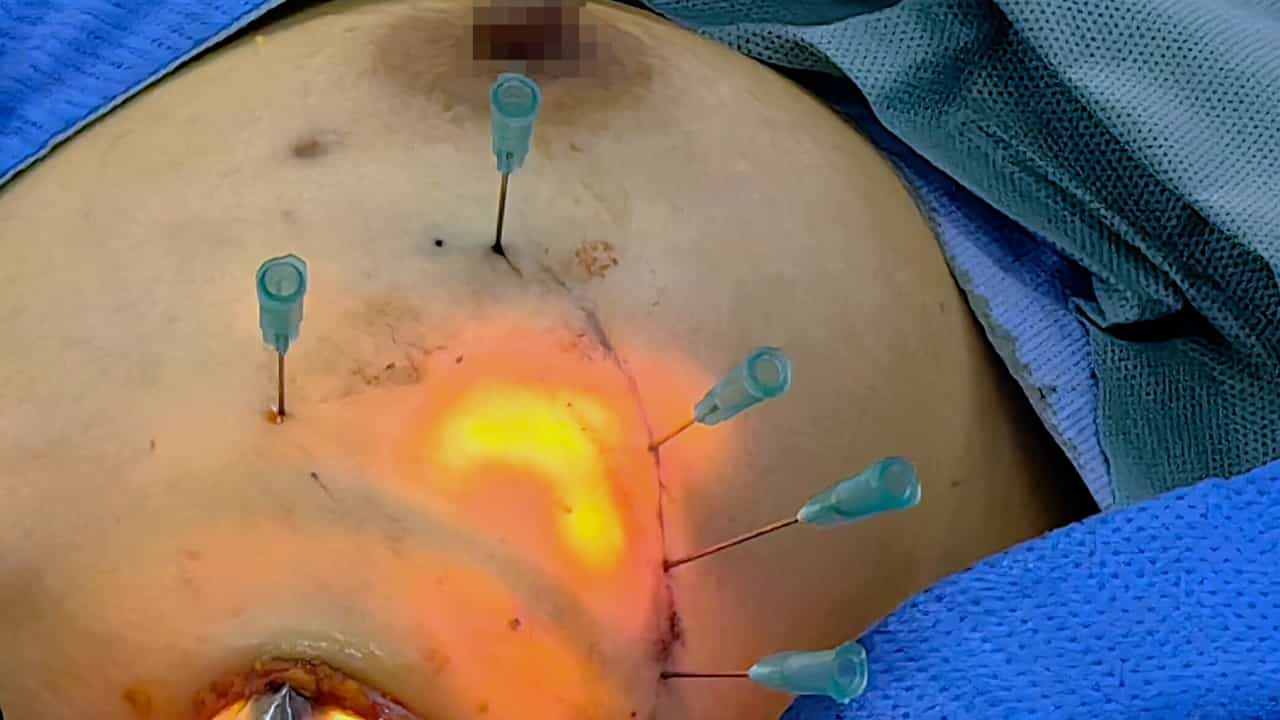
Endoscopic Bilateral Nipple-sparing Mastectomy via a Single Axillary Incision with Immediate Pre-pectoral Implant-based Breast Reconstruction
Published on: May 17, 2024
Erector spinae plane block (ESPB) versus modified pectoral plane block (PECS II) in managing post modified radical
Basma M El-Khalifa1, Ahmed S A Osman2, Eman Ayman Nada3
1Department of Clinical Oncology and Nuclear Medicine, Mansoura University, Mansoura, Egypt; Medical Research Group of Egypt (MRGE), Negida Academy, Arlington, MA, USA.

Background:
Breast cancer remains the most frequently diagnosed malignancy among females worldwide. Surgical management is the cornerstone of the therapeutic strategy, however associated with multiple postoperative complications, particularly acute pain and shoulder mobility limitations. Regional anesthetic techniques have been proposed to counteract this phenomenon, such as the modified pectoral plane block (PECS II) and erector spinae plane block (ESPB). This systematic review and meta-analysis aims to compare between ESPB and PECS II in managing post-operative pain in modified radical mastectomy patients.
Methods:
We conducted a systematic search of PubMed, Web of Science, and Scopus up to July 2025. According to our eligibility criteria, randomized controlled trials comparing PECS II and ESPB techniques in modified radical mastectomy patients were included. Our primary outcomes were post-operative analgesia duration, postoperative morphine use in the first 24 h, and postoperative pain scores. Quality assessment was conducted using the Cochrane risk of bias assessment tool 2 (RoB2). Analysis of relevant outcomes was conducted using R software Version 4.4.2.
Results:
The literature search identified 697 studies, of which 11 trials, involving 790 patients, were analyzed. Compared to ESPB, PECS II was associated with a significantly longer analgesia duration [MD = -3.16, 95%CI (-6.11; -0.21), P = 0.0361], and fewer rescue analgesia requirement [RR = 1.37, (95%CI; 1.01, 1.87), P = 0.0437]. Pain assessment at 24 h, using the numerical rating scale (NRS) or the visual analogue scale (VAS), was comparable between the two techniques. Intraoperative fentanyl consumption was comparable, whereas postoperative morphine use in the first 24 h was significantly lower following PECS II [MD 2.96, 95%CI (2.43, 3.48), P < 0.0001].
Conclusion:
PECS II was superior to ESPB, with a longer analgesia duration, reduced rescue analgesia requirement, and postoperative morphine consumption in the first 24 h. Overall, PECS II may offer modest analgesic advantages in modified radical mastectomy patients.