
Pharmacological interventions for ADHD: a systematic review and dose-effect network meta-analysis
Mikail Nourredine1, Lucie Jurek2, Tasnim Hamza3
1Developmental "Evidence synthesis, Prediction, Implementation" (EPI) Lab, Centre for Innovation in Mental Health, Faculty of Environmental and Life Sciences, University of Southampton, Southampton, UK; Department of Biostatistics, Hospices civils de Lyon, Lyon, France; CNRS, LBBE, UMR 5558, Université Claude Bernard Lyon 1, Lyon, France.

Background:
Optimising the dosage of pharmacological treatments for ADHD is key to maximising their benefits, yet most clinical guidelines provide only limited information on this issue. Dose-effect relationships have not been comprehensively assessed across all ADHD medications and age groups, despite growing concerns about subtherapeutic prescribing. We aimed to estimate dose-effect curves for efficacy and tolerability of ADHD medications (stimulants and non-stimulants) across age groups.
Methods:
We conducted a systematic review and dose-effect network meta-analysis of double-blind randomised controlled trials (RCTs) evaluating oral monotherapy (stimulants and non-stimulants) in individuals aged 5 years and older meeting standardised ADHD criteria. Studies involving genetic syndromes, treatment-resistant populations, or withdrawal-phase designs were excluded. We retrieved eligible studies from the MED-ADHD database, updated on Feb 17, 2025, without language restrictions. We included published and unpublished aggregated-level data. The primary outcome was efficacy (measured using validated clinical scales) and the secondary outcome was tolerability (discontinuation due to adverse events). Within-study bias was assessed with the Cochrane Risk of Bias Tool (version 2). We summarised dose-effect associations using a hierarchical Bayesian model with restricted cubic splines. Separate analyses were conducted for children or adolescents (aged <18 years) and adults (aged ≥18 years). The distribution of key effect modifiers was used to examine transitivity of the network. People with lived experience were involved in the conceptualisation and design of the study, and in the interpretation of the findings. The protocol was pre-registered on OSF.
Findings:
Our 2017 search identified 9948 potential references for inclusion and our Feb 17, 2025 search identified 5148 references. Of these 15 096 references, 8467 were excluded after title and abstract screening, and a further 5862 references were excluded after a full-text read. Of the 767 remaining reports, 164 were included in the systematic review and 113 RCTs (45 in adults and 68 in children and adolescents) were included in the dose-effect network meta-analysis. The 68 RCTs on children and adolescents included 14 138 participants (9981 [70·6%] males and 4157 [29·4%] females) and the 45 RCTs on adults included 11 016 participants (5958 [54·0%] males and 5056 [46·0%] females). Data on ethnicity or race were inconsistently reported across RCTs. We found distinct dose-effect patterns by medication class and age group. In children and adolescents, methylphenidate, amphetamines, and guanfacine showed increasing median efficacy up to 45 mg/day, 25 mg/day and 4 mg/day, respectively, with no evidence of additional benefit at higher doses, although estimates at higher doses were characterised by wide credible intervals. In adults, amphetamines showed a plateau above approximatively 50 mg/day, whereas methylphenidate efficacy increased without evidence of a plateau, possibly due to sparse data. Dose-dependent increases in discontinuation probability due to adverse events were observed for amphetamines (above 25 mg/day for children and 50 mg/day for adults) and methylphenidate (above 50 mg/day for adults, with no clear dose-dependent risk for children). We found no evidence of dose-effect patterns for atomoxetine (in fixed-doses studies) and modafinil. Multiple sensitivity analyses confirmed the robustness of these findings. We found no evidence of intransitivity.
Interpretation:
Our findings challenge both therapeutic inertia-accepting suboptimal response without further dose titration-and uncritical dose escalation beyond licensed limits, when potential harms outweigh expected benefits. Our findings can inform clinical guidelines and should support shared decision making regarding ADHD medication dosage.
Funding:
National Institute for Health and Care Research (NIHR303122).
More Related Videos


Related Concept Videos
 01:30
Attention-Deficit/Hyperactivity Disorder
Diagnostic Criteria and Symptoms
To diagnose ADHD, symptoms must manifest before age 12 and be evident across multiple settings.
 01:24
Drug Toxicity: Dose-Dependent Reactions
 01:24
CNS Stimulants: Cocaine, Amphetamines and Cannabinoids
 01:25
Adrenergic Agonists: Indirect-Acting Agents
One mechanism involves depleting stored catecholamines by displacing them from synaptic vesicles. These agents, known as "displacers," are transported into vesicles at the expense of noradrenaline. Examples include amphetamine and tyramine, which lack a catechol moiety, resulting in prolonged action, improved oral bioavailability, and...
 01:21
Drugs Affecting Neurotransmitter Release or Uptake
 01:29
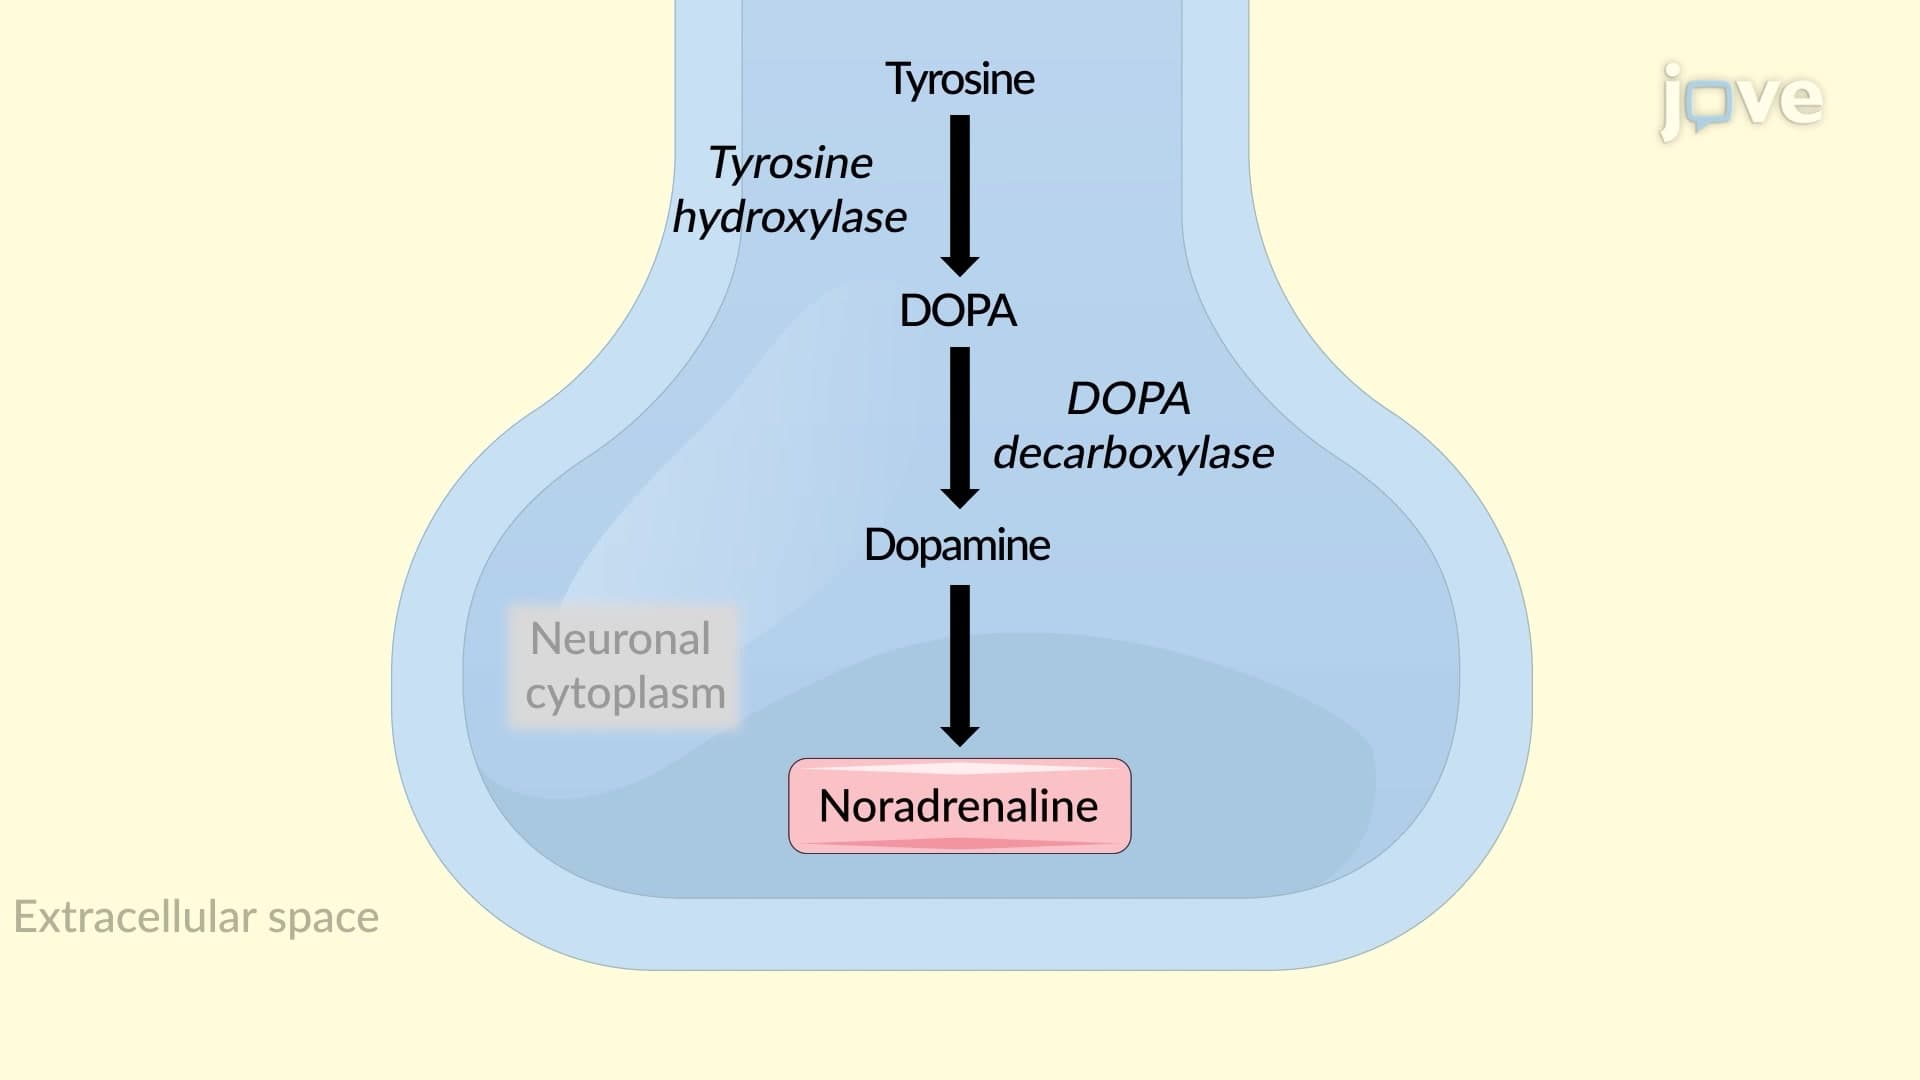
Drugs Affecting Neurotransmitter Synthesis