Related Experiment Video
Updated: May 16, 2026


High-speed Video Microscopy Analysis for First-line Diagnosis of Primary Ciliary Dyskinesia
Published on: January 19, 2022
Primary ciliary dyskinesia in pediatric persons: A microscopic movement malady
Donald E Greydanus1, Swati Y Bhave2, Narmada Ashok3
1Professor Emeritus and Founding Chair, Department of Pediatric and Adolescent Medicine, Western Michigan University Homer Stryker M.D. School of Medicine, Kalamazoo, MI, USA.

Insights
Primary ciliary dyskinesia (PCD) is a genetic disorder causing cilia dysfunction, leading to respiratory and other health issues. Diagnosis is complex due to genetic variability and requires advanced testing, with current management focusing on infection control and mucus clearance.
Area of Science:
- Respiratory Medicine
- Genetics
- Pediatrics
Background:
- The respiratory tract's role extends beyond gas exchange to protecting against environmental threats like microbes and pollution.
- Respiratory diseases pose significant health risks, with primary ciliary dyskinesia (PCD) being a complex orphan disease affecting multiple organ systems.
- PCD results from genetic mutations impacting cilia function, leading to impaired mucociliary clearance and various physiological dysfunctions.
Purpose of the Study:
- To review the pathophysiology, genetic underpinnings, diagnosis, and treatment principles of primary ciliary dyskinesia in pediatric populations.
- To highlight the phenotypic and genetic variability of PCD and its diagnostic challenges.
- To discuss current management strategies and emerging research for PCD.
Main Methods:
- Review of existing literature on primary ciliary dyskinesia.
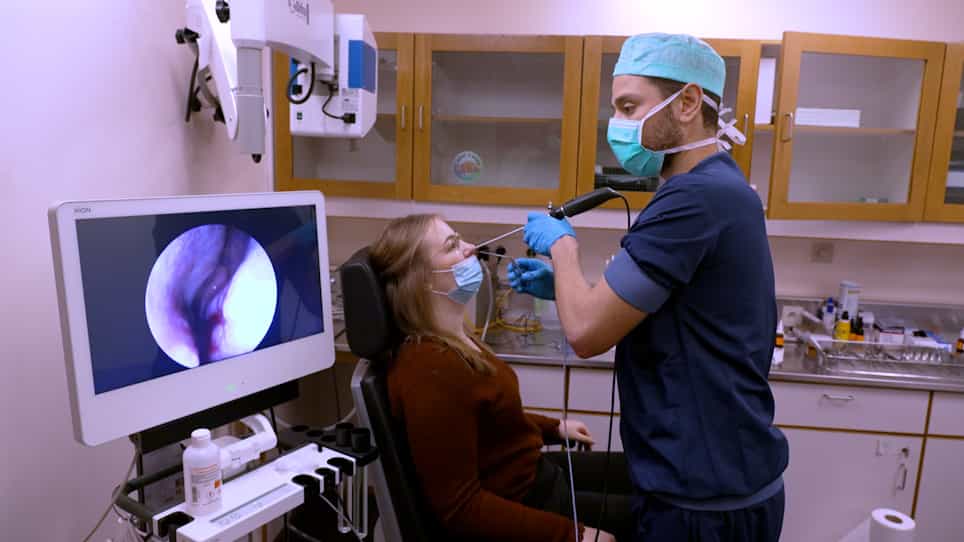
- Discussion of diagnostic techniques including nasal nitric oxide analysis, electron microscopy, immunofluorescence, high-speed video microscopy, and genetic testing.
- Analysis of genotype-phenotype correlations and differential diagnoses for PCD.
Main Results:
- PCD exhibits significant genetic and phenotypic variability, with diverse clinical presentations and disease severity.
- Diagnosis is complicated by the lack of a gold standard and requires a multidisciplinary approach with advanced testing.
- Current management focuses on treating infections and improving mucus clearance, while gene therapy is an emerging research area.
Conclusions:
- Primary ciliary dyskinesia is a complex ciliopathy with profound impacts on respiratory health and other systems.
- Accurate diagnosis requires sophisticated multidisciplinary evaluation due to its variable presentation and genetic complexity.
- Effective management involves aggressive treatment of infections and airway clearance, with future hope in gene therapy.
Abstract:
The respiratory tract (i.e., airways and alveoli) is in close contact with the milieu that is outside the human body and thus, in addition to its role in exchange of gases, it is needed to protect the human being from outside threats such as microbes and pollution. Respiratory tract diseases can have major detrimental effects on human health with increased risks for morbidity and mortality. An example of this dilemma is the orphan disease, primary ciliary dyskinesia (PCD), a complex genetic disorder linked with myriad genetic mutations involving over 50 genes and over 2000 pathogenic variants that lead to dysfunction of vital human components including the respiratory tract, auditory system, mechanisms of fertility and others. The core defect involves abnormal function and motion of microscopic organelles called cilia found throughout the human body with abnormal mucociliary clearance (i.e., aberrant mucociliary escalator). The regulation of motile cilia that are involved in various aspects of physiology such as respiration and reproduction is via thousands of genes. PCD pathophysiology, genetic underpinnings, diagnosis and principles of treatment are considered in this review of primary ciliary dyskinesia in pediatric persons (i.e., newborns, children and adolescents). Primary ciliary dyskinesia (PCD) is one of many ciliopathies that is identified as a condition with remarkable phenotypic and genetic variability. In this fluid fluctuation phenomenon, some PCD patients exhibit classic features such as chronic respiratory disease, situs abnormalities, and infertility, while others may present with milder or atypical disease. In certain cases, ultrastructural analysis of cilia may appear normal despite underlying dysfunction. Disease severity can range from early-onset bronchiectasis to relatively preserved pulmonary function into adulthood, reflecting perplexing genotype-phenotype diversity. Testing for PCD requires an experienced team with expertise in sophisticated technology that includes nasal nitric oxide (nNO) analysis, transmission electron microscopy (TEM), immunofluorescence analysis (IFA), high-speed video-microscopy analysis (HSVMA), three-dimensional explant spheroid formation (3D-E; ex vivo technique), genetic studies and others. Genetic testing is recommended for those suspected of having PCD, as for example in certain neonates (i.e., persistent respiratory distress, unexplained rhinorrhea with chronic cough, situs inversus), at-risk children (i.e., having persistent wet cough, chronic sinusitis, unexplained bronchiectasis, recurrent otitis media with airway symptomatology) and adults with early childhood respiratory symptoms often associated with infertility. The medical evaluation is complicated by various factors including the absence of a gold standard for a precise diagnosis. Also, as the clinician or clinical team considers a patient with possible PCD, the testing that is done should keep in mind the differential diagnoses of PCD; these conditions include cystic fibrosis (CF), various immune disorders, numerous infections (i.e., tuberculosis, aspergillosis, others), alpha-1-antitrypsin deficiency (AATD) and others as noted in this article. As emerging cutting-edge 21st century research seeks treatment of PCD via gene therapy, current management involves intense therapy of upper and lower respiratory tract infections (i.e., rhinosinusitis, otitis media, pneumonia) as well as bronchiectasis with focused efforts at dealing with impaired mucus clearance. Primary ciliary dyskinesia is a classic example of how microscopic (electron microscopic) maladies can lead to major macroscopic maladies in newborns, children, adolescents and adults.
Related Concept Videos
 01:05
Mechanism of Ciliary Motion
The cilia are made up of microtubules in a 9+2 arrangement, with nine microtubule doublet ring bundles, surrounding a pair of central singlet microtubule bundles. The doublet microtubule bundles are...
01:05Mechanism of Ciliary Motion
The cilia are made up of microtubules in a 9+2 arrangement, with nine microtubule doublet ring bundles, surrounding a pair of central singlet microtubule bundles. The doublet microtubule bundles are...
 01:22
Microtubules in Signaling
 01:32
Microtubule Associated Motor Proteins
 01:23
Cystic Fibrosis: Pathogenesis
CF is primarily caused by a genetic mutation in a chromosome 7 gene coding for the cystic fibrosis transmembrane conductance regulator (CFTR) protein. The most common gene mutation leading to CF is the ΔF508 mutation, but...
 01:43
The Movement of Organelles and Vesicles