Related Experiment Video
Updated: May 16, 2026


Glycemic Impact on Knee Osteoarthritis Symptoms on Physical, Radiographic, and Inflammatory Markers among Individuals Aged 50 and Over with Diabetes
Published on: March 7, 2025
Association between the triglyceride-glucose index and disease severity in non-diabetic Parkinson's disease patients
Deyan Zeng1, Min Luo1, Baojun Zhang1
1Department of Neurology, First Affiliated Hospital of Kunming Medical University, Kunming, Yunnan Province, China.

Background:
The triglyceride-glucose (TyG) index is a well-established biomarker of insulin resistance (IR) in non-diabetic populations, serving as a reliable indicator of metabolic health across diverse demographic groups. However, to date, few studies have explored the association between IR-as measured by the TyG index and disease severity in non-diabetic patients with Parkinson's disease (PD).
Methods:
PD Patients were recruited from the Department of Neurology at The First Affiliated Hospital of Kunming Medical University between 2020 and 2025. Disease severity in Parkinson's disease (PD) was assessed using the Hoehn-Yahr (HY) staging system, where stages I-II correspond to the early phase and stages beyond II indicate intermediate-to-advanced progression. The study compared TyG index differences between these groups. Spearman correlation analysis evaluated associations between individual variables and disease severity in non-diabetic PD patients. Logistic regression analysis calculated odds ratios (ORs) with 95% confidence intervals (CIs), with additional adjustment for PD-specific confounders (disease duration, age at onset, LEDD) and nutritional/metabolic markers (UA, TC, LDL, HDL, creatinine). Restricted cubic spline (RCS) analysis further examined the relationship with disease severity.
Results:
A total of 458 non-diabetic patients with Parkinson's disease (PD) were enrolled. The TyG index was significantly lower in the intermediate-to-advanced stage group compared to the early-stage group (Z = -2.257, p = 0.024). Furthermore, univariate and basic multivariate analysis revealed an independent negative association between the TyG index and disease severity (OR = 0.610, 95% CI: 0.380-0.977, p = 0.039). After adjusting for PD-specific confounders (disease duration, age at onset, LEDD), regression analysis showed a weakened association between the triglyceride glucose index and disease severity (β = -0.445, p = 0.057, OR = 0.641, 95%CI: 0.406 ~ 1.013). The association between the triglyceride glucose index and Parkinson's disease severity was no longer statistically significant after further adjustment for nutritional/metabolic indicators (β = -0.179, p = 0.598, OR = 0.836, 95%CI: 0.430 ~ 1.625).
Conclusion:
In non-diabetic PD patients, a lower TyG index was associated with greater disease severity in more advanced HY stages, but this relationship is not independent after full adjustment. Moreover, reverse causality could not be ruled out and requires validation in future prospective studies.
Related Concept Videos
 01:24
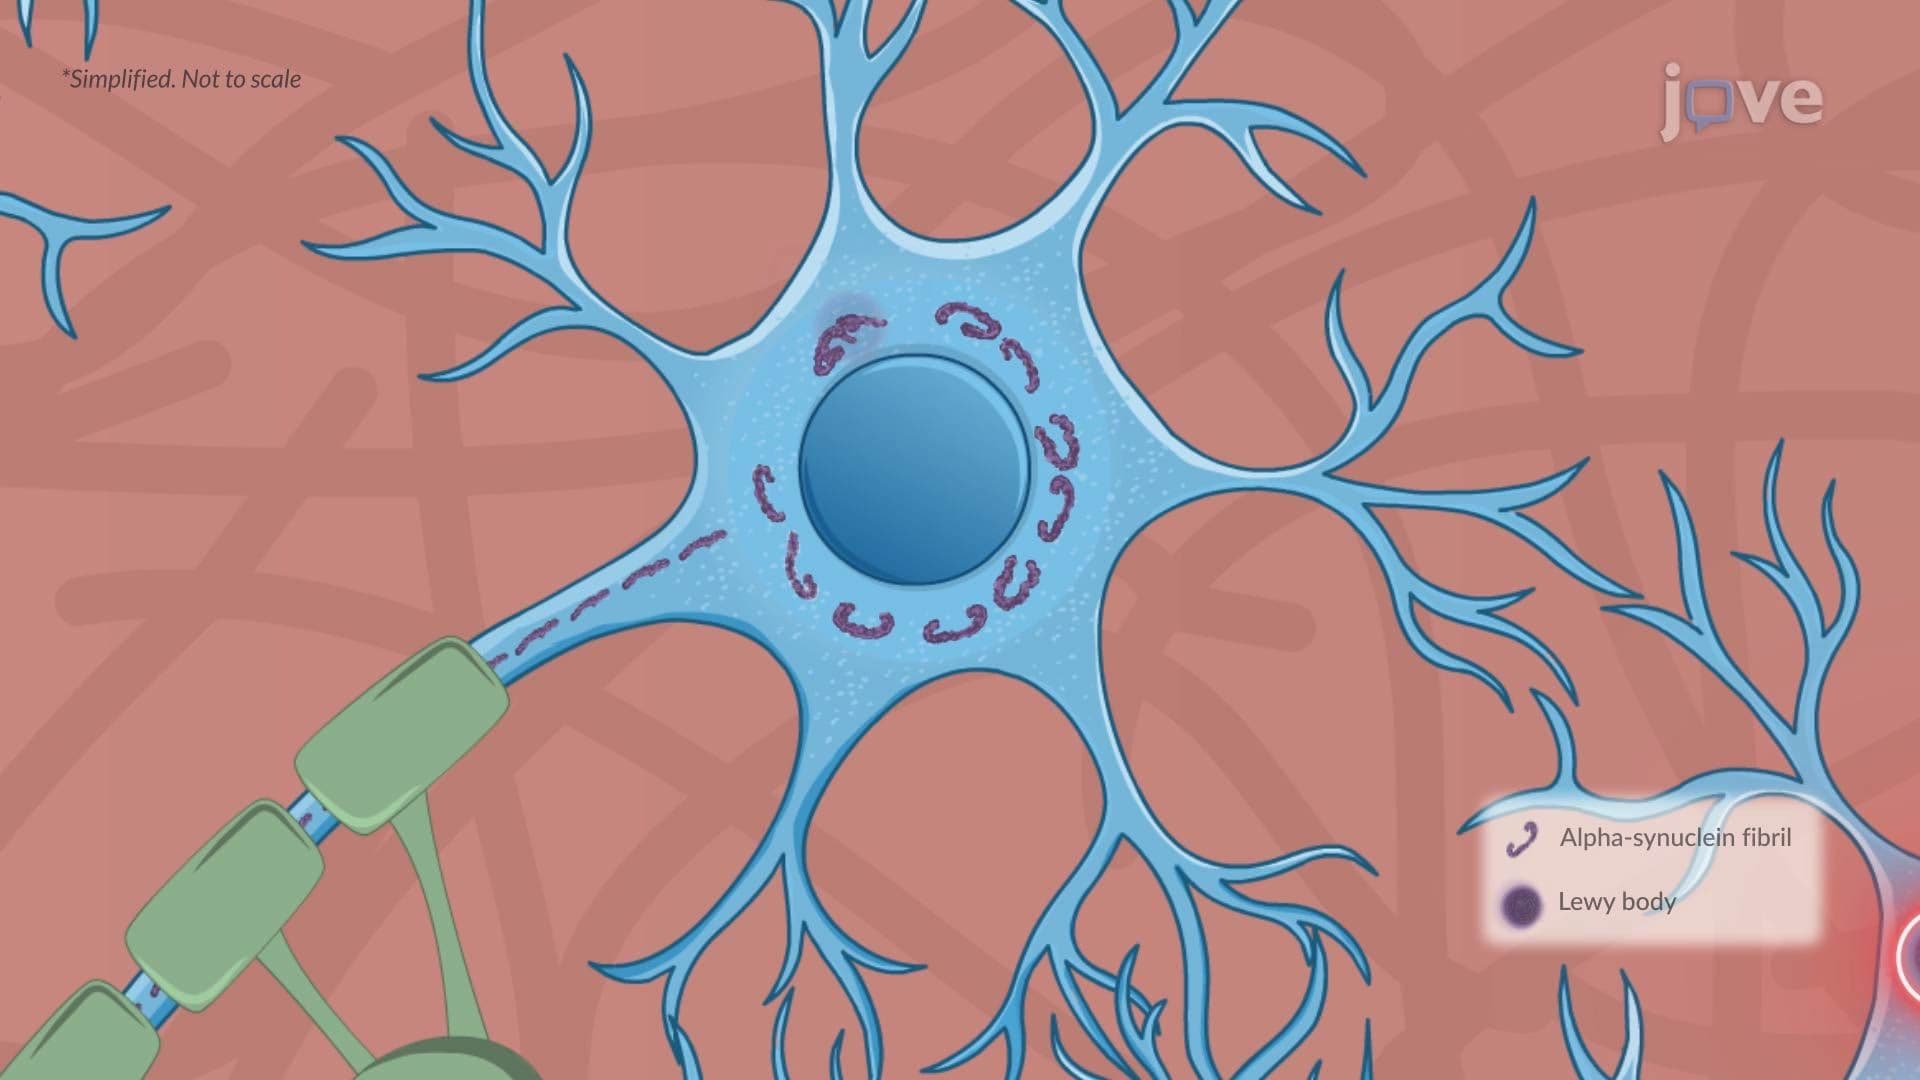
Parkinson Disease ll: Pathophysiology
 01:29
Hyperglycemia
 01:24
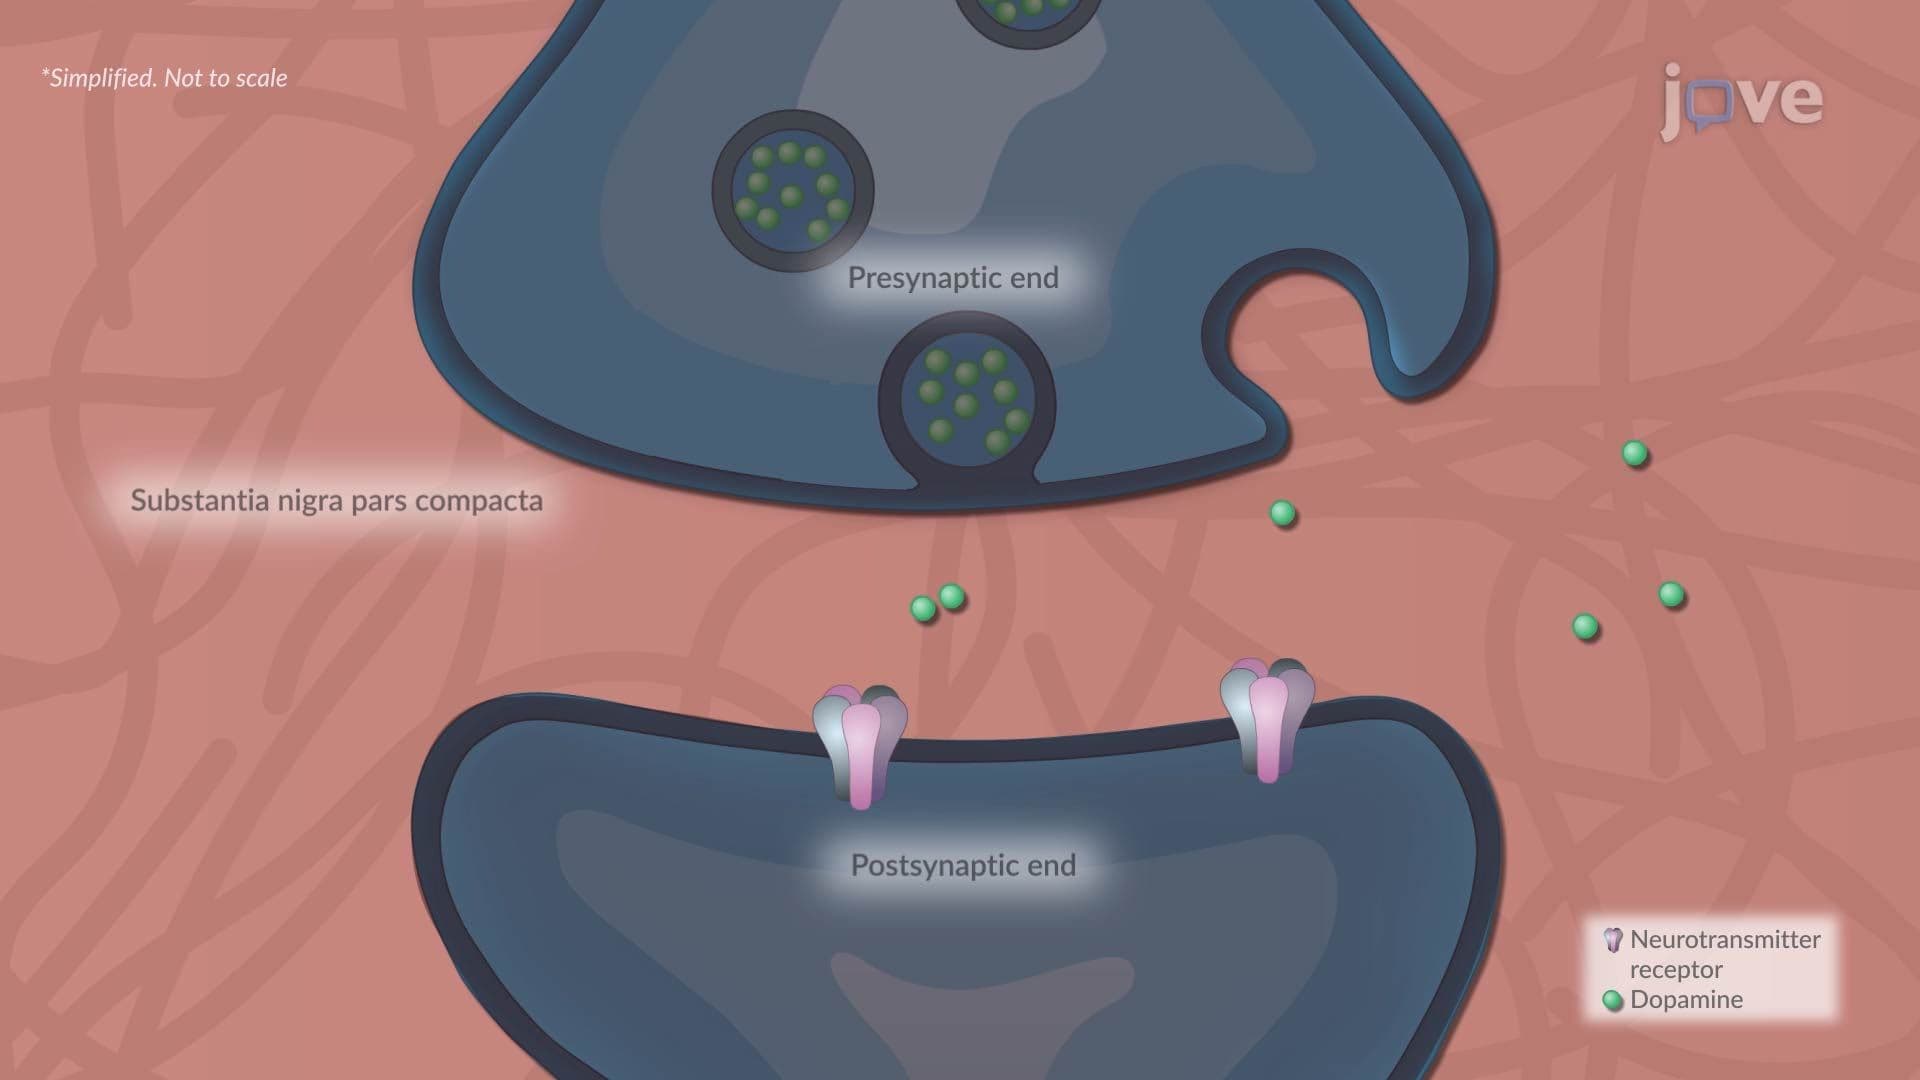
Parkinson Disease l: Introduction
 01:25
Type II Diabetes Mellitus III: Clinical Manifestations and Diagnosis
 01:26
Type I Diabetes II: Pathophysiology
 01:24
Type II Diabetes II: Pathophysiology