Related Experiment Video
Updated: May 16, 2026

Sodium Taurocholate Induced Severe Acute Pancreatitis in C57BL/6 Mice
Published on: June 28, 2021
Extreme Hyperlipasemia in End-Stage Renal Disease Mimicking Acute Pancreatitis: A Diagnostic Pitfall
Mateen Sheikh1, David Casto2, Michelle Braha2
1Medicine, Florida International University, Herbert Wertheim College of Medicine, Miami, USA.

Abstract:
Marked elevations of pancreatic enzymes are commonly interpreted as evidence of acute pancreatitis. However, in patients with end-stage renal disease (ESRD), serum amylase and lipase may be elevated without pancreatic inflammation, posing a significant diagnostic challenge. We present a case illustrating the diagnostic dilemma of extreme pancreatic enzyme elevation in an ESRD patient undergoing peritoneal dialysis without clinical or radiologic evidence of pancreatitis. A 50-year-old man with ESRD on peritoneal dialysis and known gastroparesis presented with intractable nausea and vomiting. Initial laboratory testing revealed markedly elevated pancreatic enzymes, with lipase levels peaking above 4,000 U/L and serum amylase at 545 U/L, raising concern for acute pancreatitis. However, the patient lacked characteristic epigastric pain, and contrast-enhanced abdominal CT demonstrated a normal pancreas without inflammatory changes or peripancreatic fluid collections. Autoimmune pancreatitis was excluded with negative IgG4 levels. Analysis of peritoneal dialysis fluid revealed very low amylase levels (less than 30 U/L), arguing against pancreatic enzyme leakage into the peritoneal cavity. Enzyme levels gradually declined over the course of hospitalization, and polyethylene glycol precipitation testing was pursued to evaluate for macroenzyme formation. The marked discordance between extremely elevated serum pancreatic enzymes and the absence of clinical symptoms, radiologic abnormalities, or dialysate enzyme elevation strongly suggested macrolipasemia and macroamylasemia in the context of ESRD. These findings likely reflect reduced renal clearance and macroenzyme complex formation rather than true pancreatic inflammation. This case highlights that extreme elevations of pancreatic enzymes may mimic acute pancreatitis in ESRD patients despite the absence of pancreatic disease. Careful correlation of symptoms, imaging findings, dialysis fluid analysis, and targeted laboratory testing is essential to avoid misdiagnosis and unnecessary interventions. Recognition of macroenzyme-associated hyperlipasemia should be considered when evaluating dialysis patients with markedly elevated pancreatic enzymes.
More Related Videos
 07:38
Preparing a Mice Model of Severe Acute Pancreatitis via a Combination of Caerulein and Lipopolysaccharide Intraperitoneal Injection
Published on: May 10, 2024
 03:07
Development and Validation of a Methodology for Establishing Obese Rat Models with Typical Fatty Pancreas
Published on: November 11, 2025
Related Concept Videos
 01:30
Acute Pancreatitis II: Clinical Manifestations and Management
 01:21
Acute Pancreatitis II: Pathophysiology
 01:25
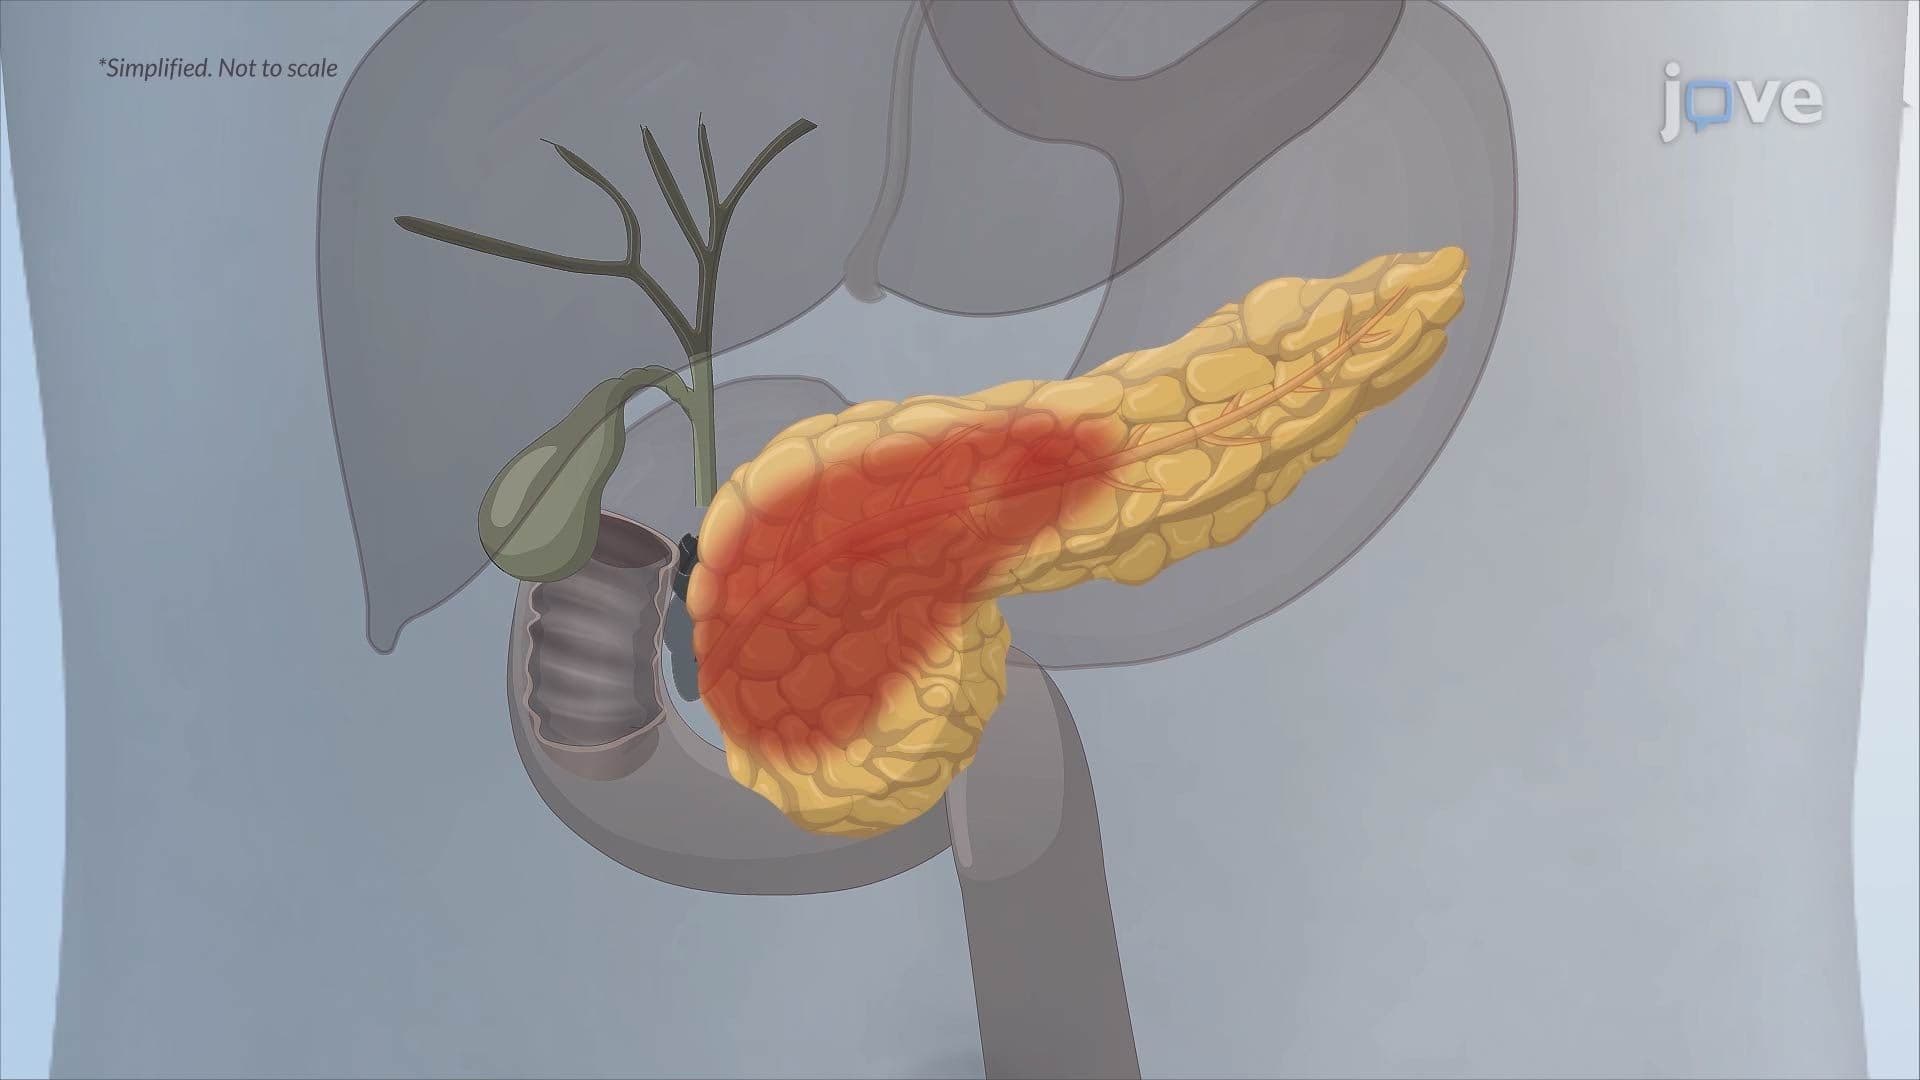
Acute Pancreatitis I: Introduction
 01:27
Acute Pancreatitis I: Introduction
Acute pancreatitis is characterized by rapid inflammation of the pancreas, often caused by factors like gallstone blockage or excessive alcohol consumption. Chronic pancreatitis, on the other hand, is a slow, progressive inflammation that may result from long-term alcohol abuse, obstructions in the pancreatic duct, or genetic factors.
The causes of acute pancreatitis include:
 01:25
Chronic Pancreatitis I: Introduction
 01:24
Chronic Pancreatitis I: Introduction
Pancreatitis is the inflammation of the pancreas, which occurs when the immune system becomes active and causes swelling, pain, and disruptions in organ function. Pancreatitis can manifest as either an acute or chronic condition.
Acute pancreatitis arises suddenly and lasts for a brief duration, while chronic pancreatitis is a long-term affliction...