Related Experiment Video
Updated: May 17, 2026


Integration of Brain Tissue Saturation Monitoring in Cardiopulmonary Exercise Testing in Patients with Heart Failure
Published on: October 1, 2019
Higher Respiratory Muscle Oxygen Cost of Breathing During Exercise in Heart Failure With Preserved Ejection Fraction
Tarin C Phillips1, Eric J Bruhn1, Gizem Cifci1
1Department of Cardiovascular Medicine, Mayo Clinic, Rochester, MN.

Background:
Patients with heart failure with preserved ejection fraction (HFpEF) have pulmonary system abnormalities resulting in impaired ventilatory reserve and heightened respiratory muscle work during submaximal exercise.
Research Question:
Do patients with HFpEF have higher respiratory muscle oxygen uptake (V˙o2) during submaximal exercise than control participants?
Study Design And Methods:
Patients with HFpEF (n = 13) and control participants (n = 16) completed 2 visits. The first visit included pulmonary function tests and an incremental exercise test. On the second visit, participants mimicked their exercise breathing patterns across a range of work rates (voluntary hyperpnea) in the absence of exercise to quantify respiratory muscle V˙o2. Respiratory muscle V˙o2 was reported during exercise at 40 W and approximately 65% peak work rates.
Results:
During exercise at 40 W, patients with HFpEF had higher respiratory muscle V˙o2 expressed as % of whole-body V˙o2 (control participants, 4.6% of whole-body V˙o2; interquartile range [IQR], 2.0-5.7 vs HFpEF, 8.3% of whole-body V˙o2; IQR, 6.1-9.2; P < .01) and mL/kg/min (control participants, 0.53 mL/kg/min; IQR, 0.24-0.68 vs HFpEF, 0.79 mL/kg/min; IQR, 0.69-1.10; P < .01). During exercise at 40 W, respiratory muscle V˙o2 was related to FVC % predicted (r = -0.64; P = .02) and breathing frequency during exercise (r = 0.70; P = .01) for patients with HFpEF, but not control participants (both r > 0.19; P > .40). During exercise at approximately 65% peak work rate, patients with HFpEF had higher respiratory muscle V˙o2 expressed as % of whole-body V˙o2 (control participants, 4.6% of whole-body V˙o2; IQR, 2.8-6.3 vs HFpEF, 7.2% of whole-body V˙o2; IQR, 6.0-8.8; P < .01). When accounting for ventilation, patients with HFpEF had higher respiratory muscle V˙o2 during exercise at 40 W and approximately 65% peak work rates (all P < .03).
Interpretation:
Our results show that respiratory muscle V˙o2 is significantly elevated in patients with HFpEF compared with control participants during submaximal exercise.
More Related Videos
 07:09
Assessment of Pulmonary Capillary Blood Volume, Membrane Diffusing Capacity, and Intrapulmonary Arteriovenous Anastomoses During Exercise
Published on: February 20, 2017
 08:44
Dual Test Gas Pulmonary Diffusing Capacity Measurement During Exercise in Humans Using the Single-Breath Method
Published on: February 2, 2024
Related Concept Videos
 01:24
Factors Affecting Respiration
 01:21
Acute Respiratory Failure-II
The underlying physiological abnormalities that contribute to hypoxemic respiratory failure include:
 01:17
Pathophysiology of Heart Failure
 01:20
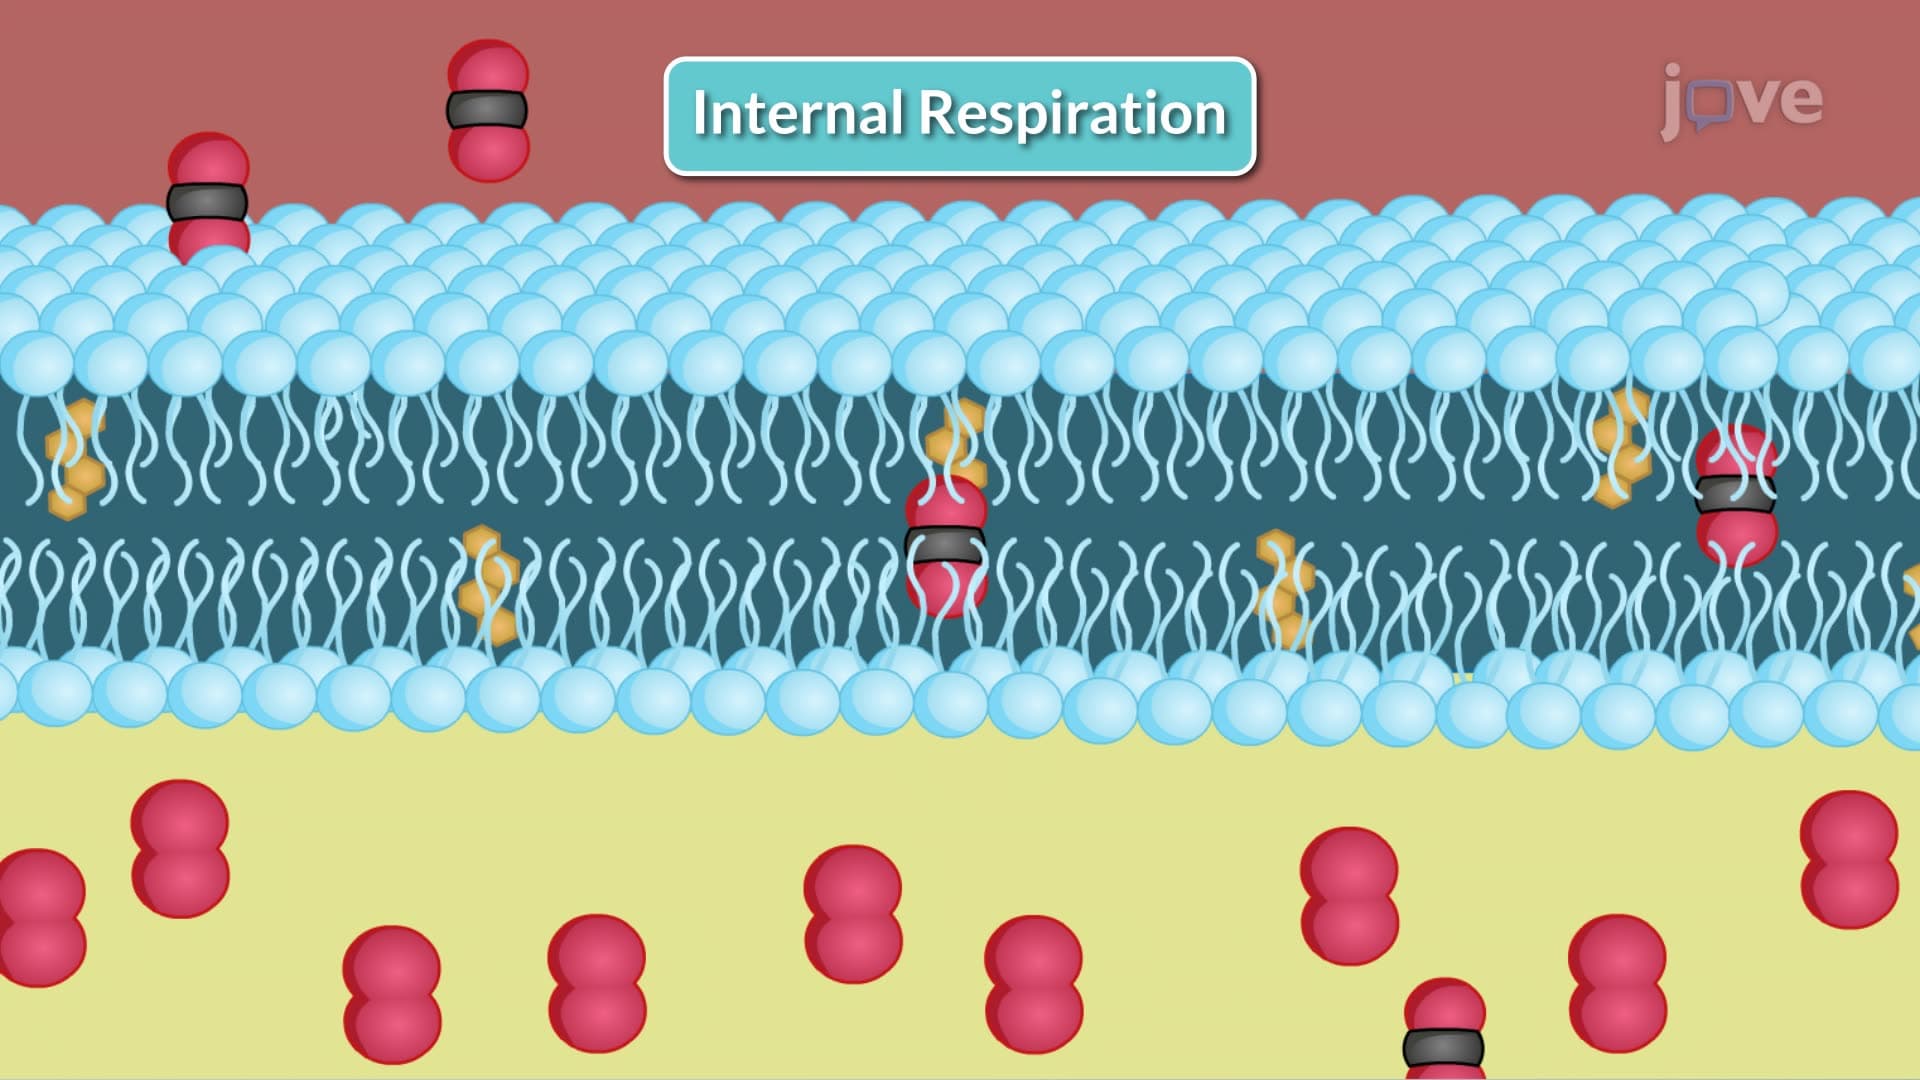
Respiration and Gaseous Exchange
Respiration involves the exchange of gases, especially oxygen (O2) and carbon dioxide (CO2), between the alveoli and body cells, a process facilitated by blood circulation. As a result, the cardiovascular system, which involves the...
 01:24
Respiratory Capacities
One key metric is the Inspiratory Capacity (IC), which represents the maximum amount of air that can be inhaled with full effort. IC is calculated by summing the tidal volume and inspiratory reserve volume, typically ranging from 2.4 to 3.6 liters.
The Functional Residual Capacity (FRC) represents the air in the...
 01:23
Acute Respiratory Failure-IV