Related Experiment Video
Updated: May 17, 2026
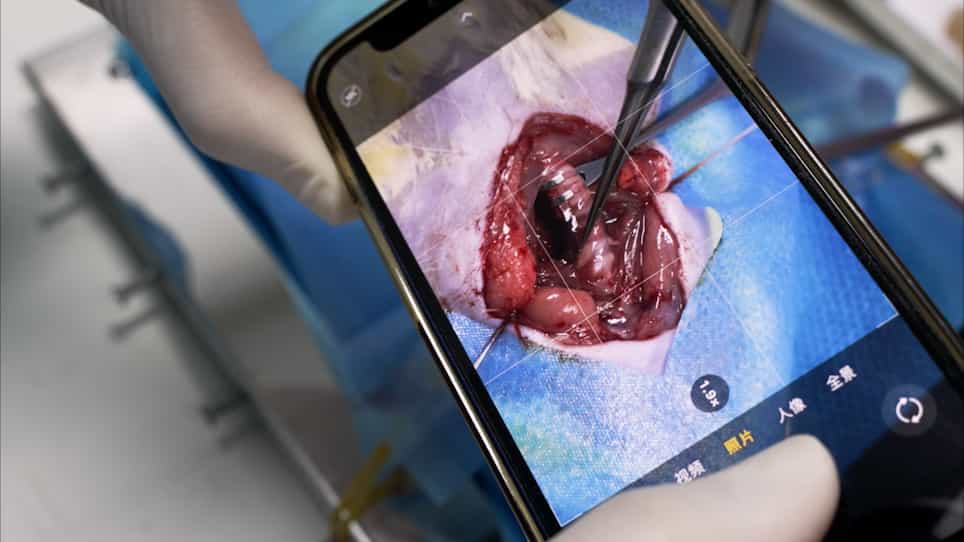

Establishment of a Simple and Effective Rat Model for Intraoperative Parathyroid Gland Imaging
Published on: August 17, 2022
Impact of cervical thymectomy on multiple endocrine neoplasia type 1 patients undergoing parathyroidectomy for
Yaser Y Bashumeel1, Ahmed Abdelmaksoud2, Mahmoud Omar1
1Division of Endocrine and Oncologic Surgery, Department of Surgery, Tulane University School of Medicine, New Orleans, LA.

Background:
Cervical thymectomy is commonly performed during parathyroidectomy for primary hyperparathyroidism in multiple endocrine neoplasia type 1. Recently, there have been several single-institutional studies that have found no added benefit to the addition of thymectomy and question its impact on postoperative outcomes. We aimed to evaluate the outcomes of concomitant cervical thymectomy in multiple endocrine neoplasia type 1 patients undergoing parathyroidectomy for primary hyperparathyroidism using a large cohort of patients.
Methods:
This retrospective study used the TriNetX research platform, a global collaborative network representing over 130 million patients. We identified 434 patients with multiple endocrine neoplasia type 1 who underwent parathyroidectomy with and without cervical thymectomy. Outcomes assessed between 129 cases of thymectomy and 305 controls without thymectomy include rates of reoperation, cure, persistent and recurrent disease, and transient and permanent hypoparathyroidism.
Results:
Adding cervical thymectomy to parathyroidectomy was associated with higher cure rates (96.9% vs 88.2%; P = .004), demonstrating a 74% reduction in the risk of persistent disease (relative risk, 0.26; 95% confidence interval, 0.10-0.72) when compared with that of parathyroidectomy alone. While transient hypoparathyroidism rates rose with the addition of thymectomy (38.0% vs 24.3%; P= .017), there was no significant difference in the rate of permanent hypoparathyroidism (3.1% vs 1.6%; P = .328).
Conclusion:
Adding cervical thymectomy to parathyroidectomy during the surgical management of multiple endocrine neoplasia type 1 patients with primary hyperparathyroidism is associated with higher cure rates without a significant increase in permanent complications. Cervical thymectomy should, therefore, be considered a standard component of care for multiple endocrine neoplasia type 1 patients undergoing parathyroidectomy for primary hyperparathyroidism.
Related Concept Videos
 00:59
The Parathyroid Glands
Oxyphil cells, whose functions remain elusive, emerge during late puberty, adding a layer of complexity to the parathyroid gland's intricacies. In contrast, principal parathyroid cells undertake a vital role by producing...
 01:27
Hyperthyroidism II: Pathophysiology
 01:23
Hypothyroidism II: Pathophysiology
 01:25
Hyperthyroidism I: Introduction
 01:24
Graves Disease II: Pathophysiology
 01:17
Hormones and Bone Tissue
Hormones That Influence Osteoblasts and/or Maintain the Matrix
Several hormones are necessary for controlling bone growth and maintaining the bone matrix. The pituitary gland secretes growth hormone (GH), which, as its name implies, controls bone growth. This happens in several ways: first, it triggers chondrocyte...