Related Experiment Video
Updated: May 17, 2026
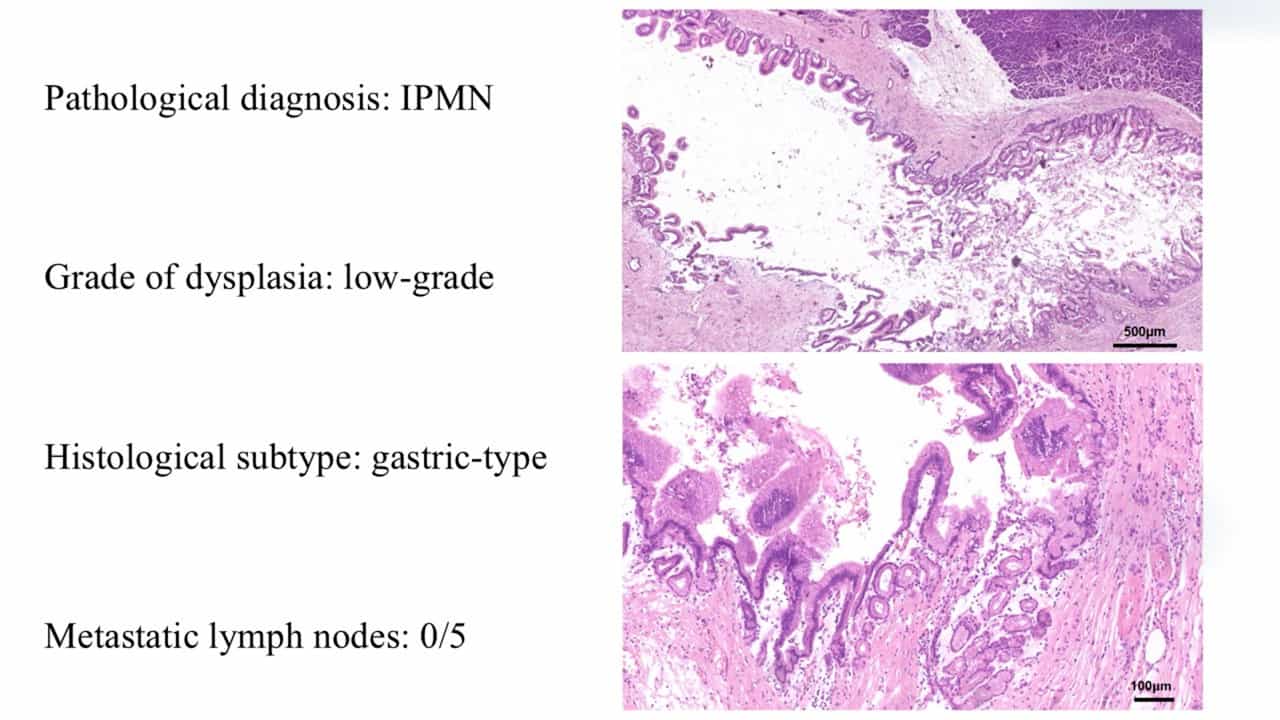

Robotic Duodenum-preserving Total Pancreatic Head Resection for Intraductal Papillary Mucinous Neoplasms
Published on: April 17, 2026
Learning curve of laparoscopic duodenum-preserving total pancreatic head resection: a single-center dual CUSUM and
Ailin Wu1, Qiangxing Chen2, Yunqiang Cai3
1Division of Pancreatic Surgery, Department of General Surgery, West China Hospital, Sichuan University, No. 37, Guo Xue Alley, Chengdu, 610041, Sichuan, China.

Background:
Laparoscopic duodenum-preserving pancreatic head resection (LDPPHR) is a parenchyma-sparing alternative to pancreaticoduodenectomy for benign and low-grade pancreatic head lesions. Although function-preserving, LDPPHR remains technically demanding, with clinically relevant postoperative pancreatic fistula (CR-POPF) and other complications. The learning trajectory and risk-adjusted quality profile of LDPPHR-t remain incompletely defined, particularly under evolving case-mix and postoperative care pathways.
Methods:
Consecutive adults undergoing LDPPHR-t were analyzed as a strictly time-ordered series. Efficiency learning was assessed using unadjusted CUSUM curves for operative time (OT) and estimated blood loss (EBL). Quality and safety learning were evaluated using risk-adjusted CUSUM (RA-CUSUM) for TO failure and CR-POPF (ISGPS grade B/C), with expected risks derived from multivariable logistic regression. Learning phases were delineated at concordant turning regions of OT- and EBL-CUSUM and interpreted alongside both RA-CUSUM curves. Sensitivity analysis used modified textbook outcome (mTO), defined as TO excluding 30-day readmission.
Results:
In 120 cases, Phase 1 (1-30), Phase 2 (31-80), and Phase 3 (81-120) were identified. OT decreased from 270 min (IQR 246.2-297.5) to 203 min (IQR 180.2-248.2) (P < 0.001), and EBL from 110 mL (IQR 100-200) to 50 mL (IQR 46.2-100) (P < 0.001). Case-mix demonstrated late-phase risk drift toward higher fistula-risk anatomy. Crude TO and mTO rates did not differ significantly across phases, but components diverged, with 30-day readmission increasing in the late phase while prolonged LOS declined to zero. In risk-adjusted monitoring, both TO failure and mTO failure RA-CUSUM showed a late-phase downward shift, whereas CR-POPF RA-CUSUM showed no sustained late upward accumulation.
Conclusions:
A dual-track CUSUM and RA-CUSUM framework characterized LDPPHR-t learning under evolving anatomical complexity. Efficiency improved earlier, whereas risk-adjusted composite-endpoint stabilization emerged later. Concordant TO and mTO analyses support the robustness of the late-phase learning interpretation while clarifying the influence of post-discharge care pathways on crude composite-endpoint behavior.