Related Experiment Video
Updated: May 19, 2026

A Mouse Model of Orthopedic Surgery to Study Postoperative Cognitive Dysfunction and Tissue Regeneration
Published on: February 27, 2018
Management of hip fracture in older adults with cognitive impairment: a narrative review
Hao Rao1, Li Luo2, Jialing Cheng2
1First Clinical College, Hubei University of Chinese Medicine, Wuhan, Hubei, China.

Background:
Hip fractures in older adults are costly and often fatal. Cognitive impairment (CI) complicates pain assessment, raises delirium risk, and hinders early mobilization and rehabilitation. This review synthesizes recent evidence on postoperative care, covering epidemiology, mechanisms, delirium, rehab, outcomes, and practical bedside strategies.
Methods:
A narrative review was performed to inform postoperative management of older adults hip-fracture patients with CI. PubMed and Web of Science were searched from 2018 to 2025 using MeSH and free-text terms for hip fracture, cognitive dysfunction/dementia/MCI, and rehabilitation, delirium, perioperative care, orthogeriatrics, and outcomes. Only English-language human studies were included. CI was defined by DSM-5/ICD-10 dementia, Petersen MCI, or MMSE <24/MoCA <26. Two reviewers independently screened studies; disagreements were resolved by a senior researcher. Case reports, protocols, abstracts, animal studies, <50 participants, non-core topics, and short follow-up were excluded. Additional 2023-2025 studies were identified by targeted searches and reference tracing. No risk-of-bias or GRADE assessment was applied.
Results:
Among older adults with hip fracture, approximately 20-40% have CI, making it a prominent clinical characteristic of this population. Dementia and even mild cognitive deficits increase the risk of falls and hip fractures by two- to threefold. After fracture, CI is linked to worse outcomes, including more delirium and complications, slower recovery, and higher mortality. Delirium is among the most prominent postoperative complications, particularly in those with pre-existing CI. Multidisciplinary care models, such as orthogeriatric co-management, early surgery within 24 to 48 h, adequate analgesia, and proactive delirium prevention, are associated with better outcomes. Rehabilitation should not be considered futile in dementia, yet patients with CI often receive less therapy and are less likely to regain pre-fracture function. One-year mortality and institutionalization are higher, while education and cognitive reserve may buffer decline, highlighting CI heterogeneity.
Conclusion:
Hip fracture in older adults with CI represents a high-risk clinical scenario that often warrants coordinated interdisciplinary care. Current clinical recommendations are supported by a hierarchy of evidence ranging from Level I (meta-analyses and RCTs) for orthogeriatric co-management and analgesia to Level II (prospective cohorts) for long-term functional outcomes. Available evidence generally supports early surgery, geriatric co-management, delirium prevention, effective analgesia, early mobilization, and tailored rehabilitation. These strategies may support recovery and may be associated with lower mortality and less loss of independence, though gaps remain in optimal rehab intensity and long-term cognitive outcomes.

Related Concept Videos
 01:30
Cognitive Development During Adulthood
 01:27
Pharmacodynamics in Geriatric Patients: Effects of Age
 01:15
Drug Dosing: Geriatric Patients
 01:18
Pharmacokinetics in Geriatric Patients: Effect of Age on Drug Metabolism
 01:30
Dementia
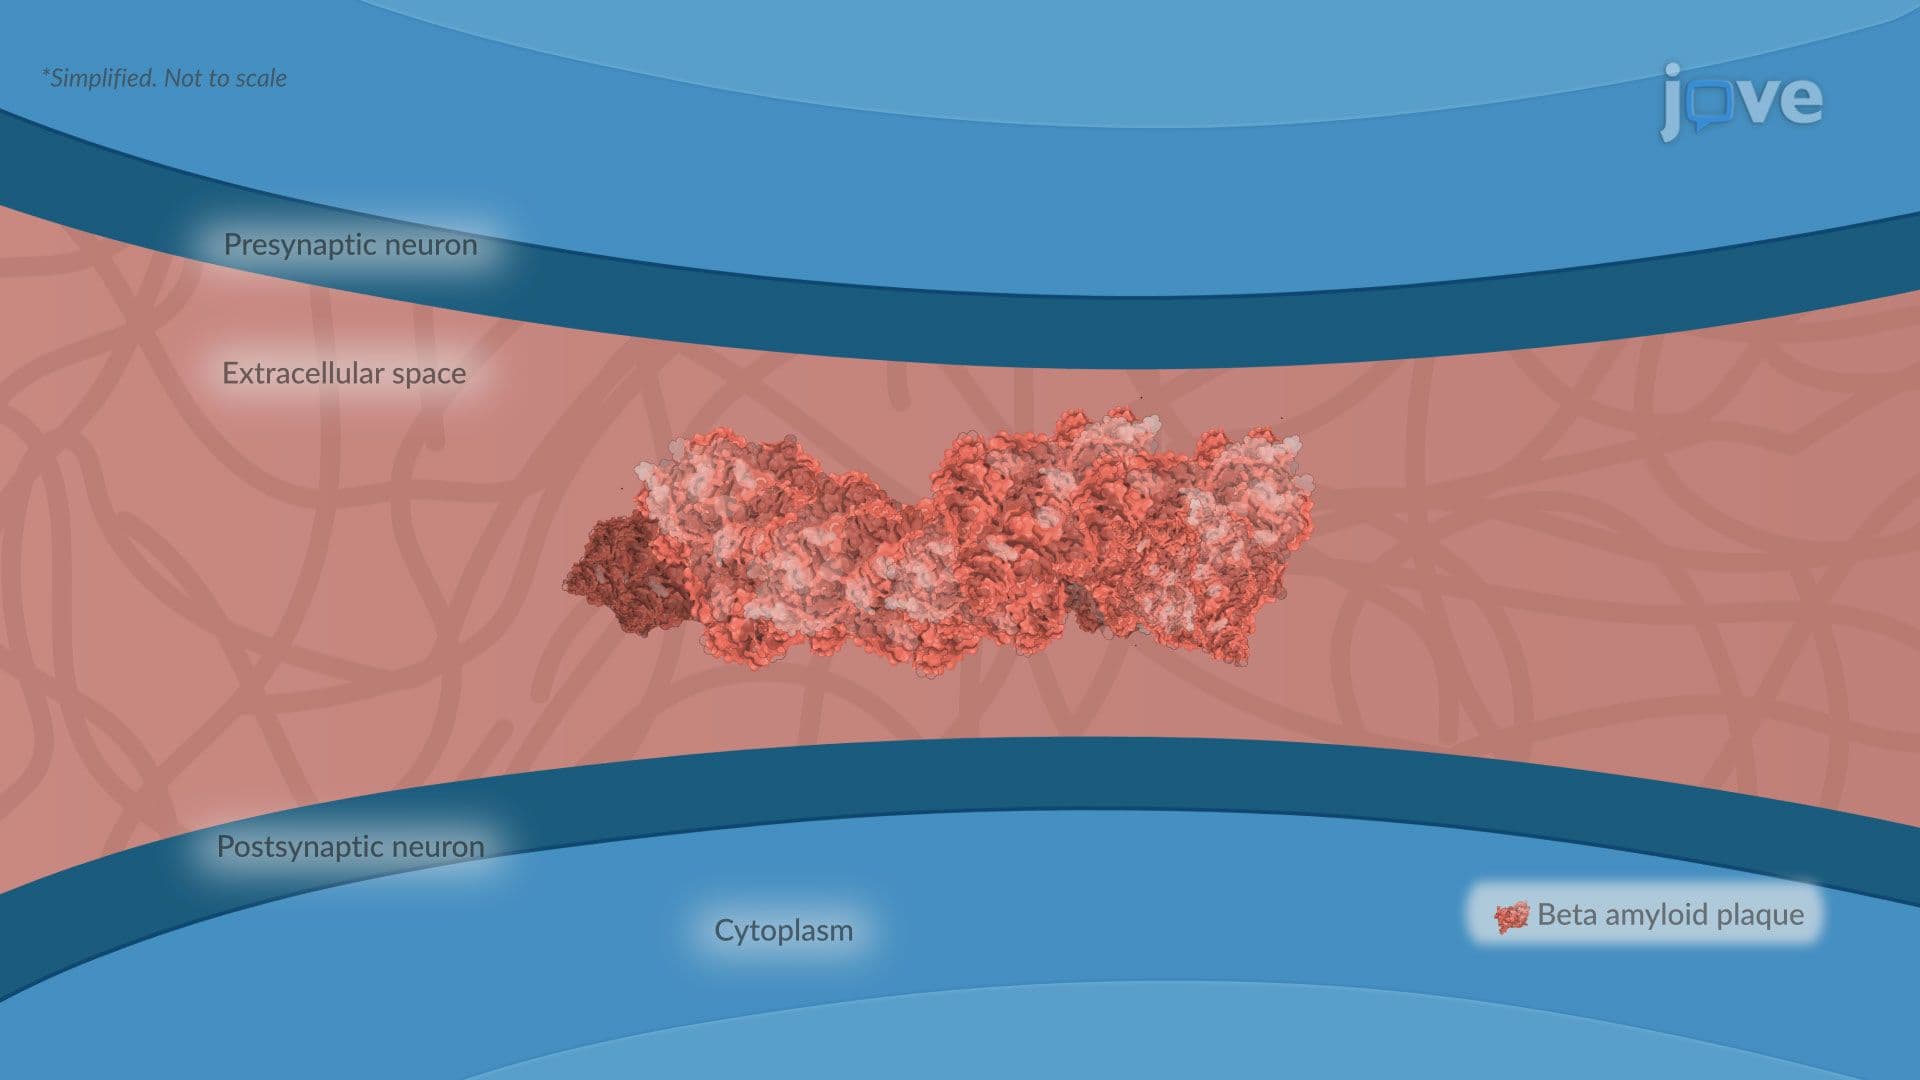
The progression of dementia is generally gradual.
 01:22
Dementia l: Introduction