Related Experiment Video
Updated: May 19, 2026
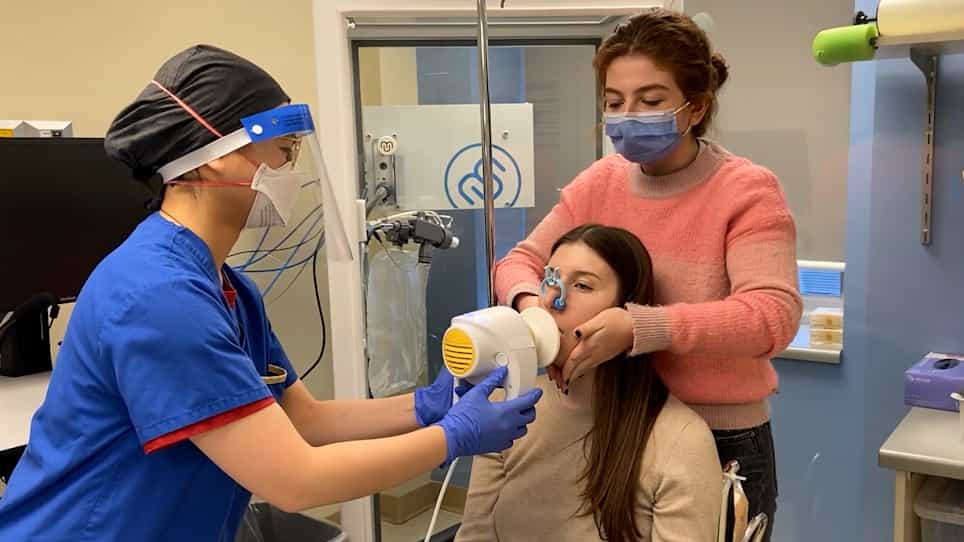

Conducting Respiratory Oscillometry in an Outpatient Setting
Published on: April 8, 2022
Impact of Fluticasone Furoate/Vilanterol on Small Airway Function in Asthma: A Real- World Study Using Impulse
Wei-Chun Huang1,2, Chia-Hung Chen1,2, Chih-Yen Tu1,2
1Division of Pulmonary and Critical Care, Department of Internal Medicine, China Medical University Hospital, Taichung, Taiwan.

Background:
Small airway dysfunction (SAD) is a key component of asthma pathophysiology that may persist despite adequate treatment. Impulse oscillometry (IOS) provides sensitive detection of peripheral airway abnormalities beyond conventional spirometry. Fluticasone furoate/vilanterol (FF/VI) is a widely used once-daily inhaled corticosteroid/long-acting β2-agonist (ICS/LABA) combination that has been shown to improve lung function and reduce exacerbation risk in patients with asthma. However, the effects of FF/VI on small airway function have not been well explored, particularly using IOS and in relation to inflammatory phenotypes. Therefore, this study evaluated the effects of once-daily FF/VI on spirometry and IOS parameters and examined whether blood eosinophil levels influence these responses.
Methods:
Patients with asthma who received FF/VI for 12 months were retrospectively reviewed. Pulmonary function tests, including forced expiratory volume in one second (FEV1) and forced vital capacity (FVC), and IOS indices-resistance at 5 Hz (R5), resistance at 20 Hz (R20), the difference between R5 and R20 (R5-R20, kPa/L/s), reactance area (AX, kPa/L), and resonant frequency (Fres, Hz)-were compared before and after treatment. Patients were stratified according to blood eosinophil count (<300 or ≥300 cells per microliter).
Results:
After one year of treatment, mean FEV1 increased from 2.51 to 2.65 liters (p < 0.001) and mean FVC increased from 3.16 to 3.23 liters (p < 0.001). Total and central airway resistance decreased, with mean R5 declining from 148 to 131% of predicted (p < 0.001) and mean R20 from 145 to 134% of predicted (p < 0.001). The AX improved from 0.90 to 0.69 kPa/L (p = 0.044). However, significant improvements in R5-R20 and Fres were observed only among patients with blood eosinophil counts below 300 cells/µL.
Conclusion:
FF/VI 92/22 μg delivered via the Ellipta device significantly improved spirometric indices and central airway resistance. Improvements in small-airway mechanics were observed in patients with lower eosinophilic inflammation, suggesting that eosinophilic inflammation may be associated with attenuated small airway response. Further prospective studies are warranted to better define the role of inflammatory status in small airway dysfunction and to validate these findings.

Related Concept Videos
 01:26
Asthma-II: Pathophysiology and Classification
Additionally, environmental and genetic factors play crucial roles in determining an individual's susceptibility to asthma and the severity of their condition.
Critical processes in asthma pathophysiology include:
 01:13
Asthma III: Clinical Manifestations
 01:30
Asthma-IV: Diagnostic and Management
Clinical Assessment for Asthma:
This is the first step in diagnosing and managing asthma. It includes:
 01:26
COPD: Management Using Bronchodilators and Corticosteroids
 01:19
Antiasthma Drugs: Leukotriene Modifiers
Leukotriene modifiers work through two distinct mechanisms:
 01:24
Asthma-III: Symptoms and Complications
Classification of Asthma