Related Experiment Video
Updated: May 19, 2026


New Thrombectomy Technique for Total Portal Vein Thrombosis in Liver Transplantation
Published on: June 27, 2025
Thromboelastography-Guided Goal-Directed Transfusion During Hepatectomy in a Fontan Patient With Life-Threatening
Tokimitsu Hibino1,2, Hitomi Tokuyama3, Yusuke Okui2
1Department of Public Health, International University of Health and Welfare, Tokyo, JPN.

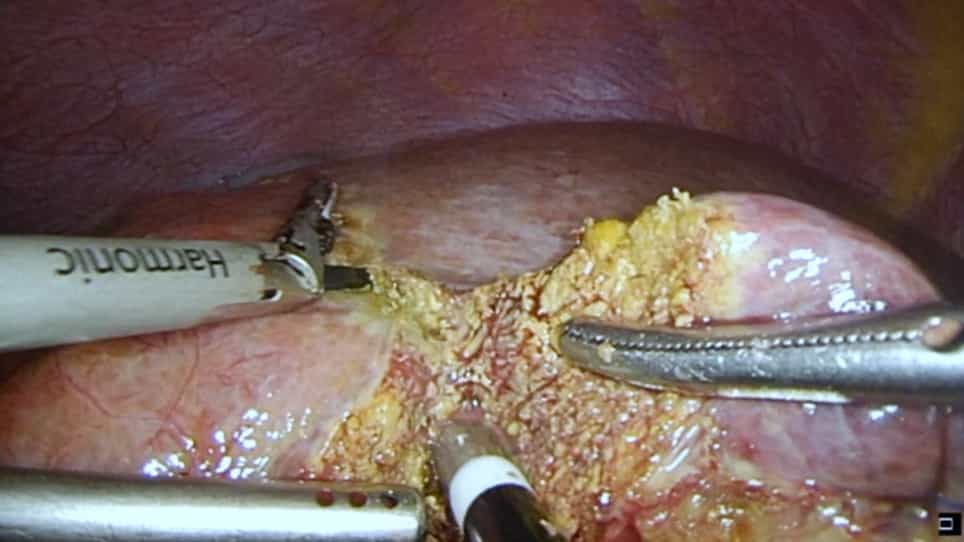
Fontan-associated liver disease (FALD) is a critical long-term complication following Fontan surgery for complex congenital heart disease. The non-physiological Fontan circulation, which relies on elevated central venous pressure (CVP) to drive pulmonary blood flow, inherently leads to chronic hepatic congestion, fibrosis, and potentially hepatocellular carcinoma. We report the anesthetic management of a 25-year-old male with FALD and hepatocellular carcinoma (8.3 cm) undergoing open hepatectomy. Our anesthetic strategy focused on maintaining cardiac contractility, preserving venous return, and reducing pulmonary vascular resistance using inotropic and inodilator support and inhaled nitric oxide. During liver resection, the patient experienced catastrophic hemorrhage (6,875 mL) characterized by diffuse oozing due to high CVP and coagulopathy, leading to hypovolemic shock. Hemodynamics were sustained by ultra-rapid transfusion (up to 200 mL/min) and vasopressor support. Intraoperative coagulation was monitored via thromboelastography (TEG), which revealed severe qualitative and quantitative deficiencies in fibrinogen function that persisted despite fresh frozen plasma transfusion. Targeted administration of 3 g of fibrinogen concentrate and 40 units of platelet concentrate based on TEG findings achieved clinical hemostasis. Despite the massive bleeding and postoperative heart failure, the patient was successfully discharged. In conclusion, this case suggests that for hepatectomy in Fontan patients, a multidisciplinary approach incorporating the Pringle maneuver and TEG-guided precision transfusion can be a vital strategy to prevent circulatory collapse and manage life-threatening hemorrhage.
Fontan-associated liver disease (FALD) is a critical long-term complication following Fontan surgery for complex congenital heart disease. The non-physiological Fontan circulation, which relies on elevated central venous pressure (CVP) to drive pulmonary blood flow, inherently leads to chronic hepatic congestion, fibrosis, and potentially hepatocellular carcinoma. We report the anesthetic management of a 25-year-old male with FALD and hepatocellular carcinoma (8.3 cm) undergoing open hepatectomy. Our anesthetic strategy focused on maintaining cardiac contractility, preserving venous return, and reducing pulmonary vascular resistance using inotropic and inodilator support and inhaled nitric oxide. During liver resection, the patient experienced catastrophic hemorrhage (6,875 mL) characterized by diffuse oozing due to high CVP and coagulopathy, leading to hypovolemic shock. Hemodynamics were sustained by ultra-rapid transfusion (up to 200 mL/min) and vasopressor support. Intraoperative coagulation was monitored via thromboelastography (TEG), which revealed severe qualitative and quantitative deficiencies in fibrinogen function that persisted despite fresh frozen plasma transfusion. Targeted administration of 3 g of fibrinogen concentrate and 40 units of platelet concentrate based on TEG findings achieved clinical hemostasis. Despite the massive bleeding and postoperative heart failure, the patient was successfully discharged. In conclusion, this case suggests that for hepatectomy in Fontan patients, a multidisciplinary approach incorporating the Pringle maneuver and TEG-guided precision transfusion can be a vital strategy to prevent circulatory collapse and manage life-threatening hemorrhage.
Related Concept Videos
 01:28
Esophageal Varices-II: Clinical Features and Management
In the initial assessment, a thorough review of the patient's medical history is vital to identify risk factors such as liver disease, alcohol abuse, or...
 01:29
Venous Thrombosis III: Interprofessional Care