Related Experiment Video
Updated: May 19, 2026
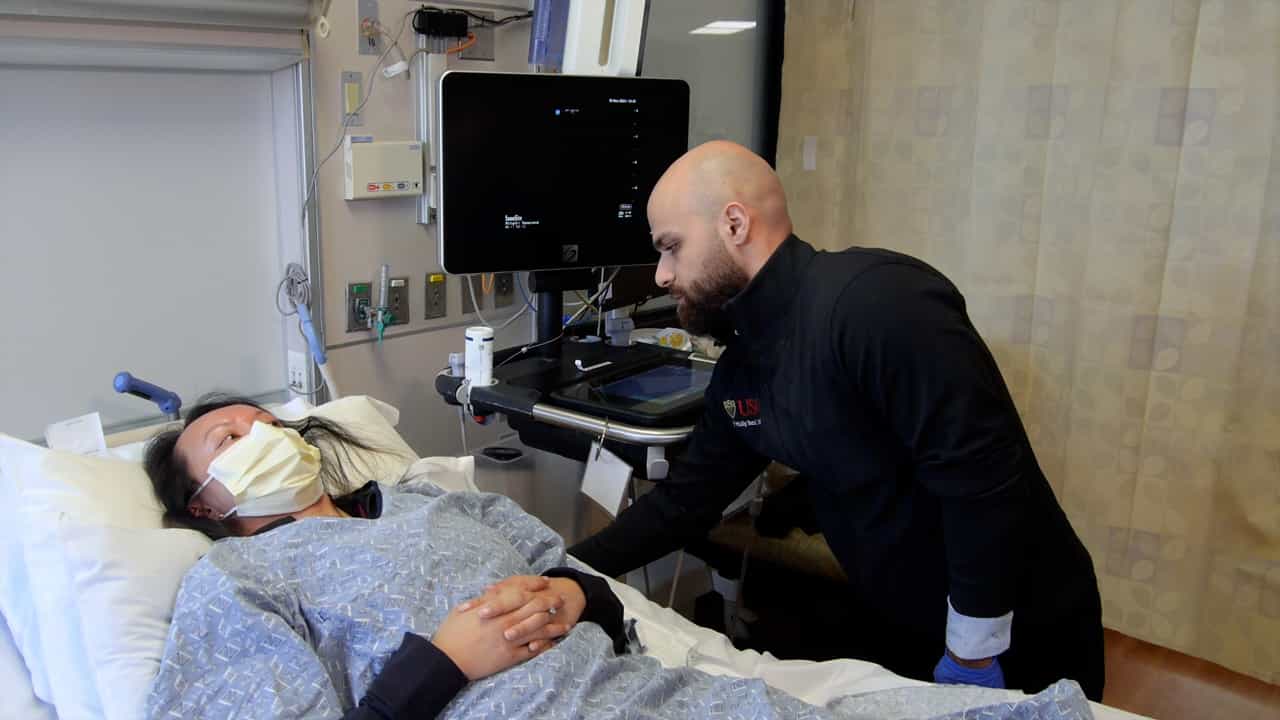

Point of Care Transcranial Color-Coded Duplex Ultrasound of the Middle Cerebral Artery
Published on: August 9, 2024
Integrated cervicocerebral ultrasound-based hemodynamic compensation scoring for anterior-circulation steno-occlusive
Yiqun Lin1, Shuai Zheng1, Sen Wang1
1Department of Ultrasound, Beijing Tiantan Hospital, Capital Medical University, Beijing, China.

Background:
Cerebral hypoperfusion underlies ischemic encephalopathy. Computed tomography perfusion (CTP) is widely used to assess cerebral perfusion, but it requires ionizing radiation and iodinated contrast, which may limit serial follow-up examinations in some patients. This study developed an integrated cervicocerebral ultrasound (ICCUS)-based scoring system for staging stenosis-related hemodynamic compensation.
Methods:
This retrospective study included patients who underwent both ICCUS and CTP, with hemisphere-level analysis of the anterior circulation, between January 2020 and April 2025. CTP status was dichotomized as compensated (Stage I1-I2) or decompensated (Stage II1-II2). Candidate ICCUS variables comprised stenosis severity of the common carotid artery (CCA), internal carotid artery (ICA), and intracranial arteries, including the anterior cerebral artery (ACA) and middle cerebral artery (MCA), as well as collateral and communicating pathway status (patent vs. non-patent) via the anterior communicating artery (ACoA) and posterior communicating artery (PCoA), ophthalmic artery (OA), and leptomeningeal routes [ACA-MCA and posterior cerebral artery (PCA)-MCA)]. The variables associated with CTP Stage II by univariate logistic regression were converted into integer points [rounded odds ratios (ORs)] to construct a weighted score, and receiver operating characteristic (ROC) analysis was used for performance evaluation.
Results:
In total, 111 patients were included in the analysis, providing 222 hemisphere-level observations, of which 59 (26.6%) were classified as CTP Stage II. Age and sex were not associated with CTP Stage II (P=0.096 and P=0.624, respectively). Compared with mild stenosis, moderate and severe ICA stenosis were associated with CTP Stage II (OR =1.57 and OR =5.05, respectively; P<0.001). Severe ACA and MCA stenosis were also associated with CTP Stage II (OR =3.92, P=0.019; OR =8.00, P<0.001). Collateral recruitment via an open OA and the PCA-MCA leptomeningeal pathway was associated with CTP Stage II (OR =2.31, P=0.028; OR =2.28, P=0.036), whereas ACoA/PCoA and ACA-MCA patency showed no significant association with CTP Stage II (all P>0.05). The ICCUS score showed good discrimination for CTP Stage II [area under the curve (AUC) =0.845]; at a cut-off value of >4 points, its sensitivity and specificity were 74.6% and 81.6%, respectively.
Conclusions:
The ICCUS-based scoring framework provides a standardized, ultrasound-based approach for identifying CTP-defined anterior circulation decompensated hypoperfusion (CTP Stage II1-II2) and may support bedside triage and follow-up assessment.

Related Concept Videos
 01:25
Imaging Studies for Cardiovascular System VI: Calcium -Scoring CT
 01:28
Imaging Studies for Cardiovascular System V: CT