Related Experiment Video
Updated: May 20, 2026

Novel Methods for Intranasal Administration Under Inhalation Anesthesia to Evaluate Nose-to-Brain Drug Delivery
Published on: November 14, 2018
Prehospital Outcomes Associated with an Initial Strategy of Intranasal versus Intramuscular Naloxone Administration
Tanner Smida1, Remle Crowe2,3, Melody Glenn4
1Department of Emergency Medicine, Division of Prehospital Care, West Virginia University School of Medicine, Morgantown, West Virginia.

Objectives:
Previous studies have suggested that intranasal (IN) naloxone is less effective than intramuscular (IM) naloxone at reversing opioid toxicity but may result in a lower prevalence of precipitated withdrawal. Because limited real-world comparisons have been performed, we aimed to compare initial strategies of IM or IN naloxone administration by emergency medical services (EMS) clinicians using a nationwide dataset.
Methods:
We included all adult (>18 years of age) patients in the 2023-2024 ESO Data Collaborative research datasets who received intranasal or intramuscular (IN or IM) naloxone from EMS following a 9-1-1 call. We used multilevel mixed-effects logistic regression with EMS agency as a random intercept to estimate the association between initial naloxone route and the outcomes of post-naloxone cardiac arrest, hypoxia (SpO2 < 90%), additional naloxone dosing, return to a respiratory rate >12, return to a Glasgow Coma Scale (GCS) >12, treatment for nausea/vomiting or agitation, and EMS transport. We included age, sex, race/ethnicity, time to naloxone (dispatch to drug administration), overdose location, documented history of intravenous drug use, and treatment year in our regression models.
Results:
We analyzed 16,550 patients treated by 1,481 EMS agencies, of whom 3,286 (20%) received their first dose of naloxone via the IM route. In comparison to patients treated with an initial strategy of IN administration, patients who received IM naloxone had lower odds of receiving additional naloxone (aOR: 0.39 [0.35, 0.44]), lower odds of receiving EMS transport (aOR: 0.82 [0.71, 0.95]), and higher odds of returning to a GCS >12 (aOR: 1.15 [1.01, 1.30]). The initial route of naloxone administration was not associated with the odds of cardiac arrest (aOR: 0.84 [0.57, 1.26]), hypoxia (aOR: 0.90 [0.80, 1.00]) return to a respiratory rate >12 (aOR: 1.02 [0.83, 1.26]), or treatment for nausea/vomiting (aOR: 0.97 [0.80, 1.17]) or agitation (aOR: 1.06 [0.81, 1.39]).
Conclusions:
In this large cohort, initial IM naloxone administration was associated with more favorable physiologic and operational outcomes compared with an initial IN strategy. Importantly, IM administration was not associated with increased EMS treatment for agitation or nausea/vomiting, which suggests no observed increase in precipitated withdrawal in the prehospital setting.

Related Concept Videos
 01:18
Drug Delivery: Enteral Route
Drugs in...
 01:24
Parenteral Anesthetics: Overview
 01:25
Cardiopulmonary Resuscitation IV: Pharmacological Management
 01:29
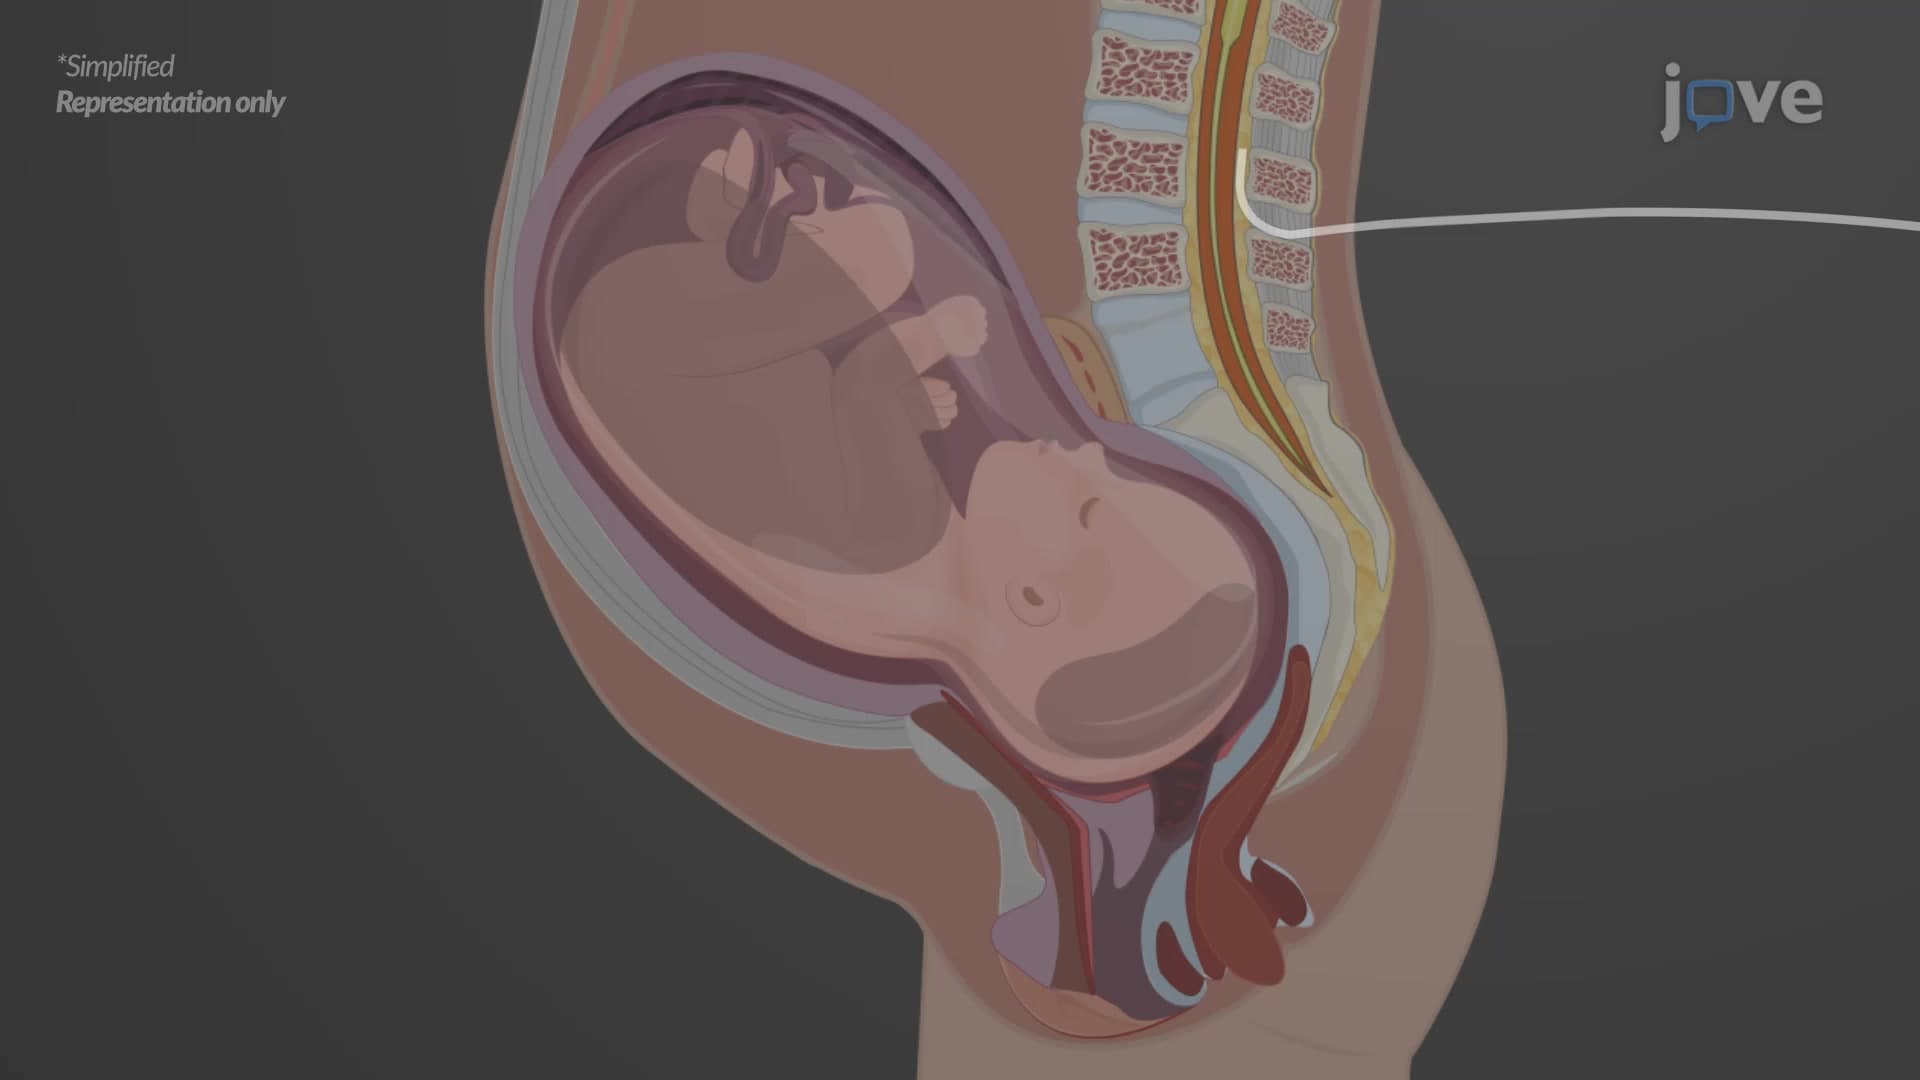
Local Anesthetics: Clinical Application as Epidural Anesthesia
Since epidural anesthetics can be infused through an epidural catheter, all types of drugs, including short-acting ones, can be administered. Chloroprocaine and lidocaine are examples of short and long-duration anesthetics, respectively. Bupivacaine...
 01:26
Pharmaceutical Poisoning: Treatment Strategies
 01:30
Adrenergic Agonists: Therapeutic Uses
Emergency and Intensive Care Unit (ICU) applications: Pressor agents increase blood pressure, heart rate, and contractility in shock and organ failure situations. Dopamine can induce vasodilation and stimulate adrenoceptors. Endogenous catecholamines are effective in treating cardiogenic shock. α2-agonists like clonidine can reverse anesthesia-induced hypertension.
Allergies and anaphylaxis:...