Related Experiment Video
Updated: May 20, 2026

How to Administer Near-Infrared Spectroscopy in Critically ill Neonates, Infants, and Children
Published on: August 19, 2020
Impaired Cerebral Autoregulation in Pediatric Patients with ECMO: A Retrospective Analysis of ECMO Time Periods and
Ethan L Sanford1,2,3, David R Busch4, Neel Shah5
1Department of Pediatrics, University of Texas Southwestern Medical Center, Dallas, TX, USA. Ethan.Sanford@UTSoutwestern.edu.

Insights
Impaired cerebral autoregulation (CAR) during extracorporeal membrane oxygenation (ECMO) was not linked to neurologic injury. However, pre-ECMO hypotension with impaired CAR significantly increased neurologic injury risk in pediatric ECMO patients.
Area of Science:
- Pediatric critical care medicine
- Neurocritical care
- Cardiovascular physiology
Background:
- Neurologic injury is a frequent complication in pediatric patients undergoing extracorporeal membrane oxygenation (ECMO).
- Cerebral autoregulation (CAR), the maintenance of stable cerebral blood flow despite fluctuations in systemic blood pressure, is crucial for brain health.
- Impaired CAR is hypothesized to increase the risk of neurologic injury in this vulnerable population.
Purpose of the Study:
- To quantify CAR in pediatric ECMO patients across different phases of treatment.
- To investigate the association between impaired CAR and the occurrence of radiographic neurologic injury.
- To identify specific time periods or hemodynamic derangements during ECMO that correlate with neurologic injury.
Main Methods:
- A retrospective observational cohort study included pediatric patients (0-18 years) undergoing ECMO without prior neurologic injury or congenital heart disease, who had brain imaging.
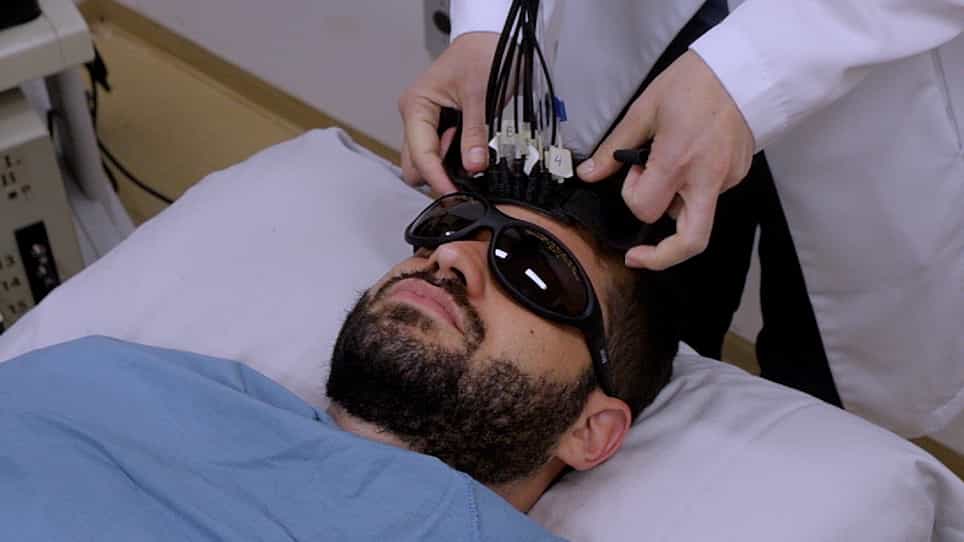
- Cerebral oximetry index (COx), derived from cerebral oximetry and mean arterial blood pressure (MAP), was used to estimate CAR.
- Neurologic Injury Score (NIS) was assessed by blinded neuroradiologists, and its association with impaired CAR and hemodynamic parameters (AUC of MAP deviations) was analyzed using univariate and multivariable regression.
Main Results:
- Data from 72 children were analyzed; 12.5% experienced severe neurologic injury (SNI).
- No significant association was found between the overall percentage of time with impaired CAR and SNI.
- Impaired CAR burden was notably higher before ECMO initiation compared to peri-cannulation and intra-ECMO periods.
- Multivariable analysis revealed a significant association between pre-ECMO hypotension during impaired CAR and higher NIS (P=0.026).
Conclusions:
- Overall time with impaired CAR, as measured by COx, did not correlate with neurologic injury in pediatric ECMO patients.
- CAR impairment was more prevalent in the pre-ECMO phase.
- The magnitude of blood pressure derangement during impaired CAR before ECMO was significantly associated with neurologic injury, highlighting pre-ECMO clinical status as a critical risk factor.
Objective:
Neurologic injury is common in pediatric patients with extracorporeal membrane oxygenation (ECMO). Impaired cerebral autoregulation (CAR) may increase the risk of neurologic injury. We aimed to measure CAR in different phases of ECMO and analyze for association with radiographic neurologic injury.
Methods:
We performed a retrospective, single-center, observational cohort study of pediatric (0-18 years) ECMO patients with no prior neurologic injury, cardiopulmonary bypass, ECMO, or congenital heart disease who underwent brain imaging. Correlation of time-matched cerebral oximetry and mean arterial blood pressure (MAP) data determined the cerebral oximetry index (COx) a noninvasive estimate of CAR. Impaired CAR was tested for association with neurologic injury score (NIS) as measured by blinded neuroradiologists. Secondarily, we calculated the area under the curve (AUC) of MAP above or below age-based 50th percentile MAP in temporal windows with impaired CAR. Univariate analysis and a multivariable linear regression model adjusting for type of ECMO, ECMO indication, and age determined the association between impaired CAR and the AUC metric with NIS.
Results:
Data from 72 children were analyzed. The median age was 11.7 months, 47 children (65.3%) received VA ECMO, and severe neurologic injury (SNI) occurred in 9 (12.5%). There was no association between percent time with impaired CAR and SNI (16.6% versus 12.2%, P = 0.38). Impaired CAR burden was significantly higher pre-ECMO as compared with peri-cannulation and intra-ECMO time periods (26.5% versus 14.8% and 16.6%, P < 0.01). The multivariable linear regression model discerned a significant association between pre-ECMO hypotension during impaired CAR and NIS (coefficient = -0.008; -0.015, -0.001; P = 0.026; R2 = 0.19).
Conclusions:
Total time with impaired CAR measured by the cerebral oximetry index was not associated with neurologic injury in pediatric patients with ECMO. However, impaired CAR was more common pre-ECMO, and pre-ECMO AUC incorporating magnitude of blood pressure derangement was significantly associated with neurologic injury, implicating pre-ECMO clinical derangements as imparting risk.