Related Experiment Video
Updated: May 21, 2026
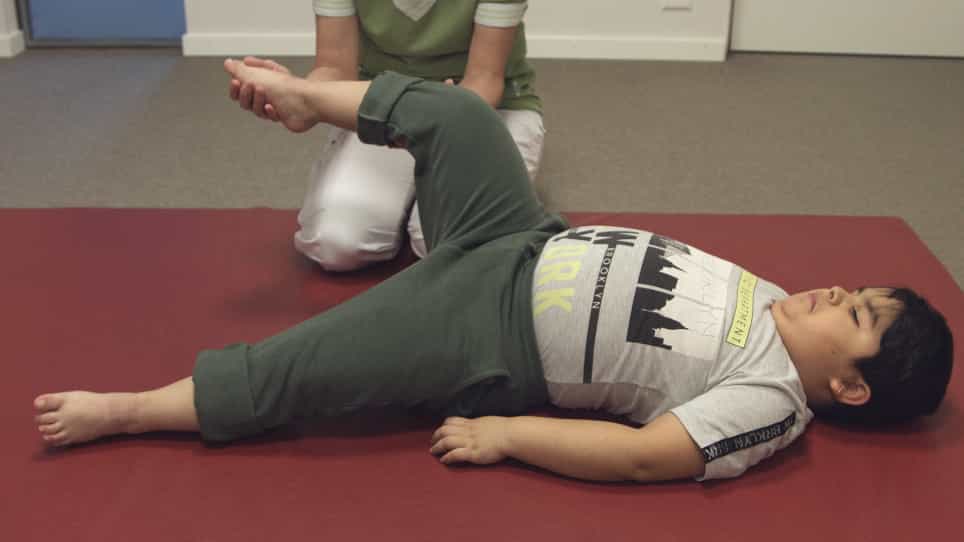

Measurements of Motor Function and Other Clinical Outcome Parameters in Ambulant Children with Duchenne Muscular Dystrophy
Published on: January 12, 2019
Changes in Provision of Recommended Cardiac Care for Duchenne Muscular Dystrophy Using a Longitudinal Cohort
Jennifer G Andrews1, Brittany L Heikke2, Omar Meziab1
1Department of Pediatrics, University of Arizona, Tucson, Arizona, USA.

Insights
Cardiac care for Duchenne muscular dystrophy (DMD) improved after 2010 guidelines. This study shows increased cardiac assessments and frequency of care for DMD patients following guideline updates.
Area of Science:
- Cardiology
- Neurology
- Genetics
Background:
- Cardiac disease is the primary cause of mortality in Duchenne muscular dystrophy (DMD).
- Cardiovascular guidelines for DMD patients have been updated multiple times, including in 2010, 2018, and 2025.
- The impact of these guideline updates on actual cardiac care delivery is not well understood.
Purpose of the Study:
- To compare the provision of recommended cardiac care for individuals with DMD before and after the publication of the 2010 DMD Care Considerations.
- To assess changes in the timing and frequency of cardiac assessments in DMD patients.
Main Methods:
- Utilized data from the MD STARnet registry for individuals with DMD.
- Included patients with at least one visit between March 2010 and March 2016.
- Compared cardiac care received during two periods: February 2005-February 2010 (pre-guidelines) and March 2010-March 2016 (post-guidelines).
- Stratified analysis by age interval, diagnosis age, and left ventricular function (LVF) severity.
Main Results:
- A significant increase in baseline cardiac assessments at diagnosis was observed (39.5% to 52.4%).
- Follow-up cardiac assessments increased significantly: every other year through age 10 (22.1% to 36.0%) and annually for ages 11+ (6.0% to 18.1%).
- Semi-annual assessments for patients with LVF abnormality also increased (0.6% to 1.4%).
- No change in LVF assessment was noted for new-onset sinus tachycardia; however, arrhythmias (excluding sinus tachycardia) prompted Holter monitoring in the post-guidelines period (14.2%).
Conclusions:
- The publication of the 2010 DMD Care Considerations was associated with increased timing and frequency of cardiac care.
- Further research is needed to understand the relationship between adherence to guidelines and cardiac outcomes.
- Identifying barriers to guideline-based care is crucial for ensuring equitable management of DMD patients.
Introduction/Aims:
Cardiac disease remains the leading cause of mortality in Duchenne muscular dystrophy (DMD), spurring release of cardiovascular supervision guidelines in 2005, 2010, 2018 and most recently, 2025. Little is known about changes in cardiac care after the updates to cardiac care recommendations for DMD. This study compares provision of recommended cardiac care before and after publication of the 2010 DMD Care Considerations.
Methods:
Data from MD STARnet for individuals with DMD with at least one visit between March 1, 2010, through March 31, 2016 were used to assess frequency of cardiac visits stratified by age interval, diagnosis age, or left ventricular function (LVF) severity status. Data compared care received from February 2005 through February 2010 and March 2010 through March 2016.
Results:
We assessed data for 922 individuals. Key findings overall demonstrate a significant increase in baseline assessments at diagnosis (39.5%-52.4%, p < 0.05), asymptomatic follow-up cardiac assessments every other year through 10 (22.1%-36.0%, p < 0.001) and annually age 11+ years (6.0%-18.1%, p < 0.001) and semi-annually for individuals with LVF abnormality (0.6%-1.4%, p < 0.01). There was no change in LVF assessment following new onset sinus tachycardia (ST). Arrhythmia, excluding ST, triggered investigation with a Holter in the post-guidelines period only (14.2%).
Discussion:
We show increases in timing and frequency of cardiac care following publication of the 2010 Care Considerations. Areas for future research include understanding the relationship between adherence and cardiac outcomes, and barriers to receiving guideline-based care to ensure equitable DMD management.


Related Concept Videos
 01:30
Cardiomyopathy II: Dilated Cardiomyopathy
 01:29
Cardiomyopathy V: Interprofessional Care
 01:29
Cardiomyopathy III: Hypertrophic Cardiomyopathy
 01:29
Cardiomyopathy VI: Nursing Management
 01:21
Rheumatic Heart Disease III: Medical Management
 01:27
Coronary Artery Disease V: Interprofessional Care