Related Experiment Video
Updated: May 21, 2026
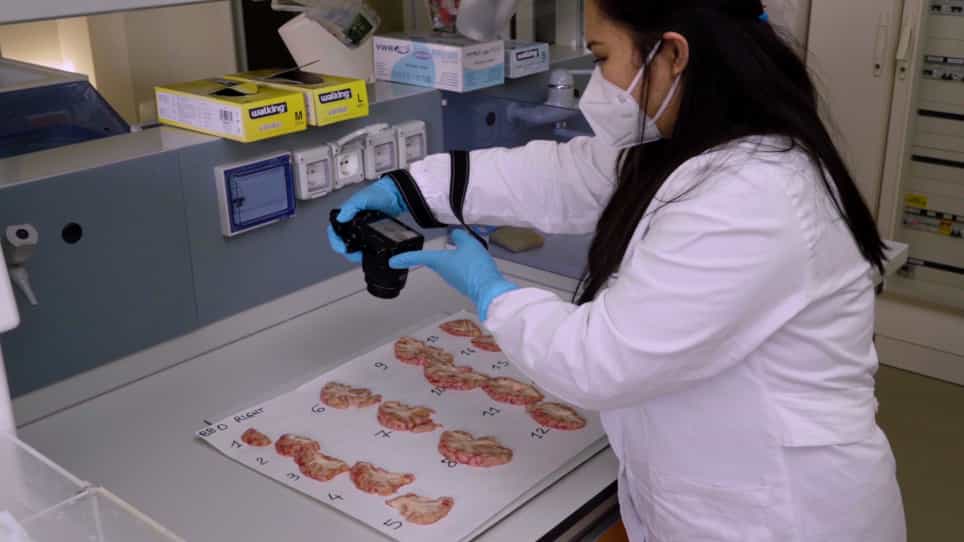

Abbiategrasso Brain Bank Protocol for Collecting, Processing and Characterizing Aging Brains
Published on: June 3, 2020
Late-life difficult-to-treat depression and dementia subtypes: a naturalistic cohort study using electronic health
Beatriz Pozuelo Moyano1, Vasiliki Orgeta2, Armin von Gunten1
1Service of Old Age Psychiatry, Department of Psychiatry, Lausanne University Hospital (CHUV) and University of Lausanne, Prilly, Switzerland.

Introduction:
Late-life difficult-to-treat depression (LL-DTD) and dementia frequently coexist in later life, but it remains unclear whether clinical and sociodemographic characteristics, as well as medication exposure patterns, differ across dementia subtypes among older adults with both conditions.
Methods:
We analysed anonymised electronic health records from a south London catchment area. We included patients aged ≥60 years at first recorded depression diagnosis with a dementia diagnosis. LL-DTD was defined as inadequate response to ≥2 antidepressant trials. Dementia diagnoses were classified as Alzheimer's disease (AD), vascular dementia (VD), mixed AD/VD, dementia with Lewy bodies (DLB), or other/unspecified dementia. Around the index depressive episode, we captured sociodemographics, depressive symptoms, physical comorbidity, and medication indicators. We used multivariate logistic regression to examine cross-sectional correlates distinguishing dementia subtypes (with AD as reference) within the LL-DTD and dementia sample. We conducted stratified analyses comparing non-AD versus AD dementia by the temporal order of dementia and depression diagnoses.
Results:
Among 890 older adults with LL-DTD and dementia, AD was the most common subtype (33.9%), followed by mixed AD/VD (22.5%), VD (22.2%), other/unspecified dementia (15.2%), and DLB (6.2%). Depressive symptom profiles and psychotropic treatment history were broadly similar across subtypes. Compared with AD, VD was associated with greater functional impairment, while greater physical comorbidity burden was more evident in VD and mixed AD/VD.
Discussion:
Somatic multimorbidity and functional impairment provided the clearest clinical separation between subgroups, while depressive symptom patterns and medication exposure appeared largely non-specific across dementia subtypes. This underscores the importance of multimorbidity and physical health burden in understanding heterogeneity of dementia outcomes in LL-DTD.
Related Concept Videos
 01:30
Dementia
The progression of dementia is generally gradual.
 01:22
Dementia l: Introduction
 01:29
Alzheimer Disease l: Introduction
 01:26
Alzheimer's Disease: Overview
The clinical diagnosis of AD hinges on the presence of memory and other cognitive impairments. Biomarkers, such as changes in Aβ and tau...
 01:22
Alzheimer's Disease: Treatment
 01:03
Long-term Depression
Calcium Ion Concentration Mechanism
If over time, all...