Related Experiment Video
Updated: May 22, 2026
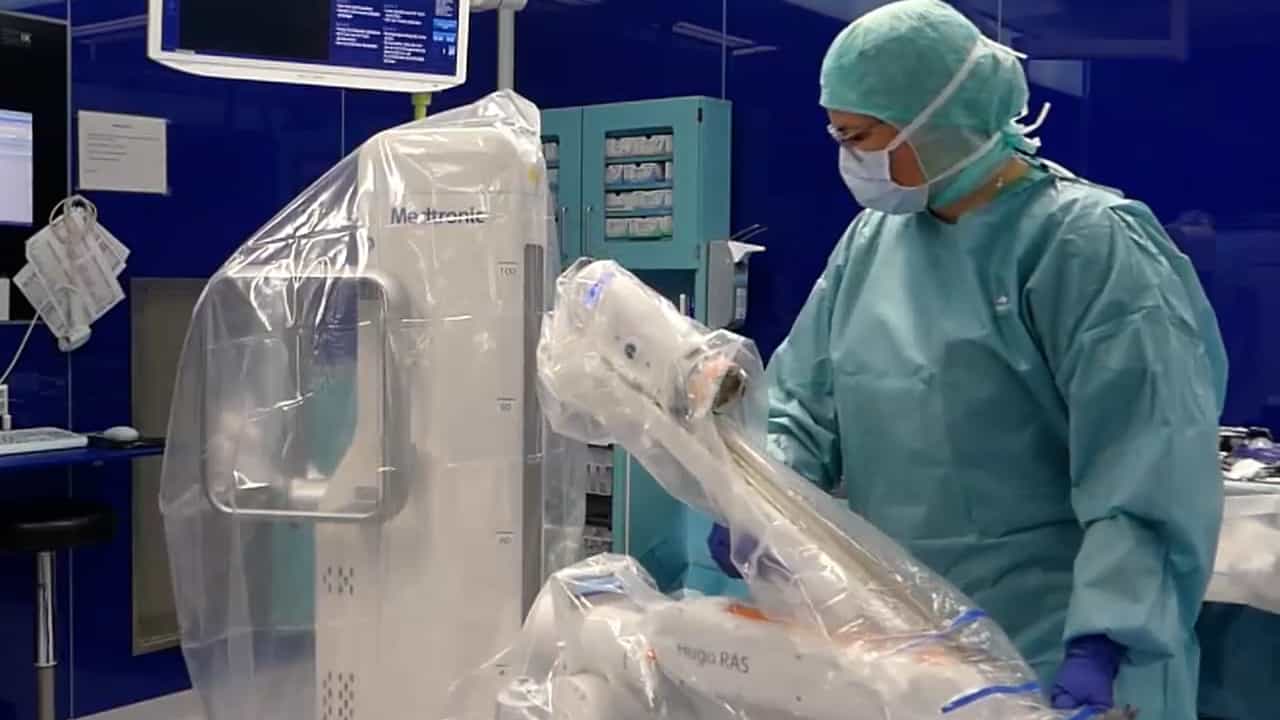

Robotics in Surgery: A Modular Robotic Platform Driven Gastric Wedge Resection
Published on: February 7, 2025
[Robotic gastrectomy after neoadjuvant therapy: application advantages and technical key points]
1Department of General Surgery, Division of Gastric Surgery, the First Affiliated Hospital of Nanjing Medical University (Jiangsu Province Hospital), Nanjing 210029, China.

Abstract:
Neoadjuvant therapy (NAT) has become the important treatment for locally advanced gastric cancer (LAGC). However, NAT-induced histopathological changes, including tumor bed fibrosis, tissue edema, inflammatory response, and lymph node remodeling, significantly increase the technical difficulty of subsequent surgery. In this specific post-NAT population, the selection of minimally invasive surgical platforms, optimization of surgical strategies, and rational application of energy devices are current clinical hotspots. Combining the latest literature and data from our prospective studies, this review systematically elaborates on NAT-induced histopathological changes and their surgical implications, and compares the advantages and disadvantages of laparoscopic and robotic surgery in post-NAT patients. Analysis suggests that robotic surgery, with its three-dimensional high-definition vision, wristed instruments, and tremor filtration, offers unique advantages in managing highly fibrotic areas such as the suprapancreatic and splenic hilar regions, potentially increasing lymph node dissection, attenuating postoperative inflammatory response, and facilitating timely adjuvant therapy. This review focuses on the timing of robotic surgery, resection extent, and lymph node dissection strategies, and provides an in-depth comparison of ultrasonic shears and Maryland forceps in managing post-NAT fibrotic tissues. The Maryland forceps, owing to its precise grasping, wristed articulation, and low thermal spread, outperforms ultrasonic shears in retrovascular dissection, nerve preservation, and plane maintenance, serving as the primary instrument for fine dissection. This article aims to provide references for clinical decision-making regarding minimally invasive surgery in post-NAT LAGC patients, emphasizing that regardless of the platform chosen, the extent of D2 lymphadenectomy should not be compromised by NAT, with oncological safety remaining the paramount principle.
