Related Experiment Video
Updated: May 22, 2026
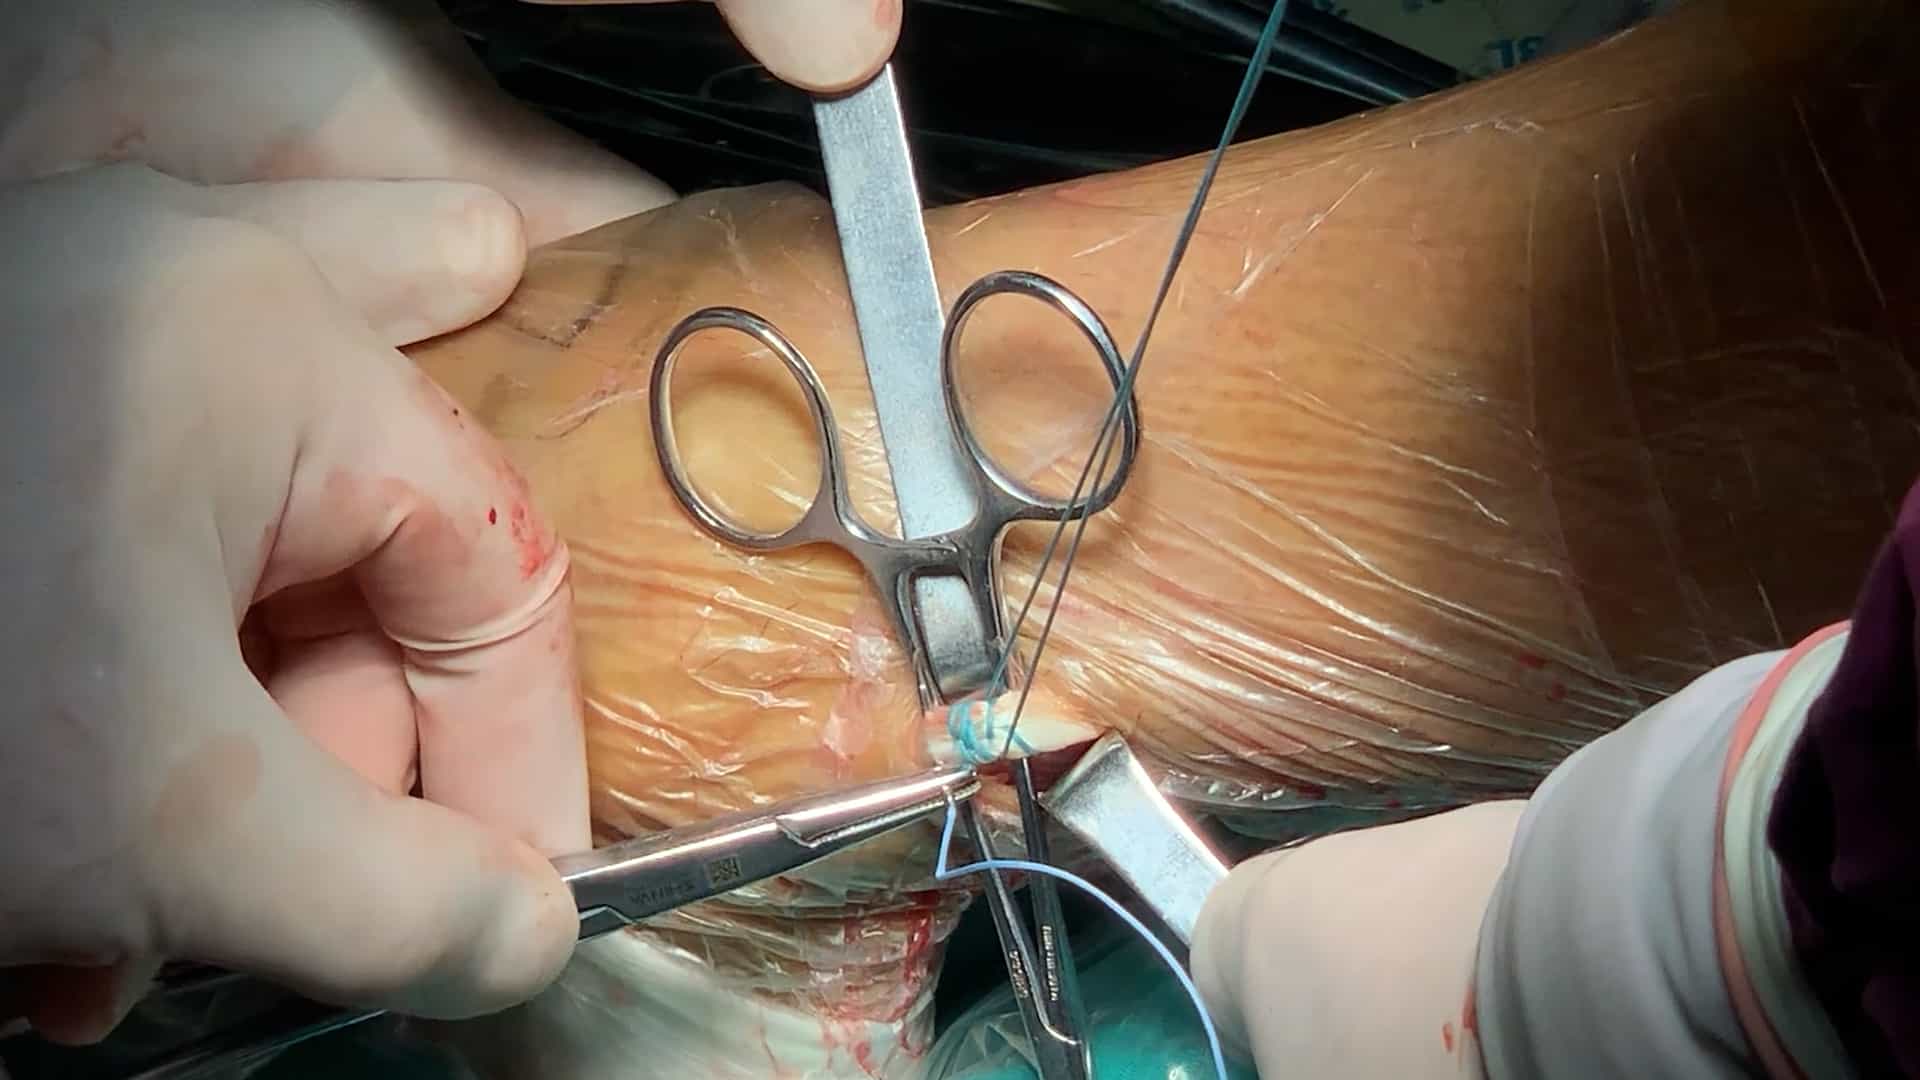
Harvesting of Peroneus Longus Tendon Autograft
Published on: September 2, 2025
Surgical outcomes of insertional Achilles tendinopathy: A comparison of techniques with and without FHL transfer
Güneş Ateş1, Saffet B Korkut2, Abdurrahmal Vural3
1Department of Orthopedics and Traumatology, Bahçelievler State Hospital, Istanbul, Türkiye.

Background:
Insertional Achilles tendinopathy may require surgery when nonoperative treatment fails. Flexor hallucis longus (FHL) tendon transfer is used as an adjunct in advanced insertional degeneration.
Purpose:
To compare 1-year outcomes, minimal clinically important difference (MCID) achievement, and complications between FHL transfer with debridement/retrocalcaneal ostectomy and debridement/ostectomy alone.
Study Design:
Retrospective comparative cohort study (indication-based group allocation).
Methods:
Thirty consecutive patients treated surgically between 2017 and 2023 were reviewed retrospectively. Preoperative magnetic resonance imaging (MRI) planimetry guided selection: patients with >50% degeneration underwent FHL transfer plus debridement and retrocalcaneal ostectomy (n = 15), whereas patients with ≤50% degeneration underwent debridement and ostectomy alone (n = 15). Outcomes were assessed preoperatively and at 1 year using the Victorian Institute of Sport Assessment-Achilles (VISA-A), American Orthopaedic Foot and Ankle Society Ankle-Hindfoot Scale (AOFAS-AH), Foot and Ankle Ability Measure (FAAM), Foot and Ankle Disability Index (FADI), and visual analog scale (VAS) pain. MCID was calculated using a distribution-based method.
Results:
Both groups improved significantly at 1 year (all p < 0.05). No between-group differences were observed for VAS, AOFAS-AH, FAAM, or FADI (all p > 0.05). The FHL group had higher postoperative VISA-A scores (65.9 ± 15.3 vs 49.9 ± 19.7; p = 0.031) and higher VISA-A MCID achievement (93.3% vs 66.6%; p = 0.046). Minor wound complications occurred in 4 patients (2/15 in each group).
Conclusions:
Both surgical approaches improved pain and function at 1 year. In this indication-based cohort, adding FHL transfer for >50% MRI-defined degeneration was associated with higher Achilles-specific function (VISA-A) without increased wound complications.