Related Experiment Video
Updated: May 22, 2026
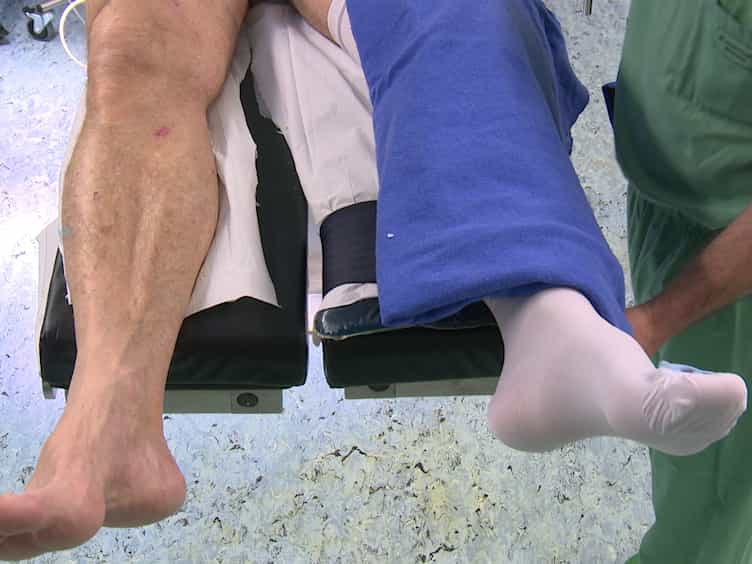

Individualized Stem-positioning in Calcar-guided Short-stem Total Hip Arthroplasty
Published on: February 27, 2018
Comparative Outcomes of Modular Versus Monoblock Fluted Tapered Stems in Revision Total Hip Arthroplasty: An American
David G Deckey1, Mackenzie Kelly2, Isabella Zaniletti3
1Department of Orthopedics, Mayo Clinic, Phoenix, Arizona.

Background:
Modular and monoblock fluted tapered femoral stems have become the workhorse in revision total hip arthroplasty (rTHA). This study compared the associated risk of all-cause revision, infection, dislocation, periprosthetic fracture (PPFx), or aseptic loosening between modular and monoblock fluted tapered stem designs.
Methods:
An analysis of rTHA in patients aged ≥ 65 years from 2012 to 2021 in the American Joint Replacement Registry was performed. A total of 9,121 patients who had fluted tapered stems were identified: 7,565 (82.9%) modular and 1,556 (17.1%) monoblock designs. Outcomes including all-cause rerevision, rerevision for infection, dislocation, PPFx, and aseptic loosening were captured through December 2023 for a minimum 2-year follow-up. Adjusted cause-specific Cox proportional hazard models (adjusted hazard ratios, aHRs) were used to assess the association of stem design with outcomes.
Results:
The overall all-cause re-revision rate was 8.5%. Index revision for dislocation (aHR 1.5, P = 0.03) and PPFx (aHR 1.3, P = 0.01) were associated with increased rerevision risk. There was no risk of infection (aHR 0.9, 95% confidence interval [CI]: 0.6 to 1.4, P = 0.57), PPFx (aHR 0.7, 95% CI: 0.5 to 1.1, P = 0.12), or aseptic loosening (aHR 0.9, 95% CI: 0.6 to 1.6, P = 0.83) that were found to be associated with type of fluted tapered stem. Compared to those who had modular stems, those who had monoblock stems were not associated with an increased risk of all-cause rerevision (aHR 0.7, 95% CI: 0.6 to 1.0, P = 0.052). However, compared to those who had modular stems, those who had monoblock stems were associated with a lower associated risk of rerevision for dislocation (aHR 0.6, 95% CI: 0.4 to 1.0, P = 0.045).
Conclusions:
There was no significant difference in the risk of all-cause rerevision between modular and monoblock fluted tapered femoral stems in rTHA. Notably, monoblock stems were associated with a lower risk of subsequent rerevision for dislocation.
