Related Experiment Video
Updated: May 22, 2026
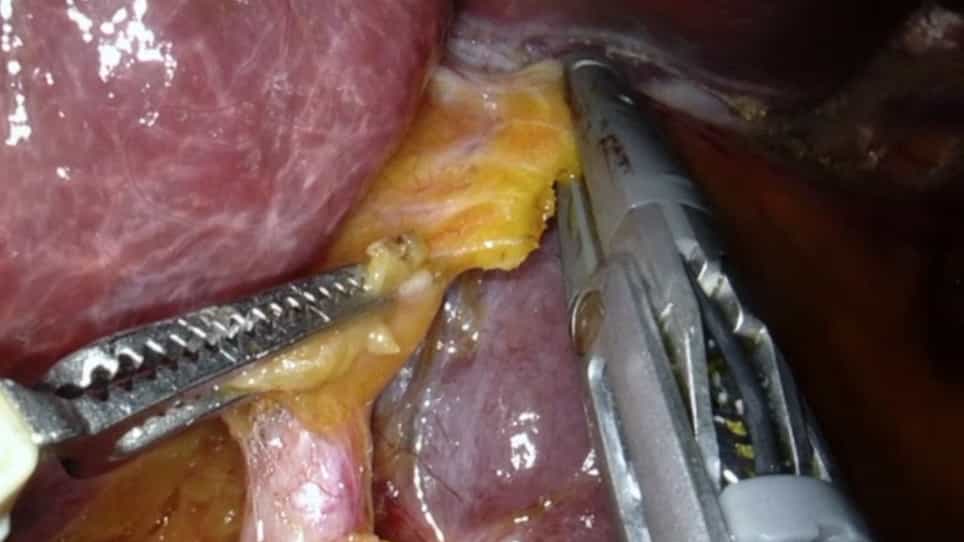

Robotic Left Hepatectomy using Indocyanine Green Fluorescence Imaging for an Intrahepatic Complex Biliary Cyst
Published on: June 24, 2022
Single-port robotic surgery for kidney and upper tract cancer: a narrative review
Karim Daher1, Nicolas A Soputro1, Salim K Younis1
1Glickman Urological & Kidney Institute, Cleveland Clinic, Cleveland, OH, USA.

Background And Objective:
Single-port (SP) robotic platforms have expanded the landscape of minimally invasive urologic surgery by enabling complex renal and upper-tract procedures through a single access point. Their design and ergonomics offer potential advantages in confined anatomical spaces and have driven growing clinical adoption in oncologic kidney surgery. This review aims to summarize current evidence supporting SP approaches for radical nephrectomy (RN), partial nephrectomy (PN), and radical nephroureterectomy (RNU), with emphasis on perioperative performance, access strategies, and emerging patient-selection frameworks.
Methods:
A focused PubMed search was performed to identify studies evaluating SP approaches for RN, PN, and RNU. Eligible publications included clinical studies of any design, Idea, Development, Exploration, Assessment, Long-term follow-up (IDEAL)-phase evaluations, multi-institutional cohorts, case series, learning-curve analyses, and technical reports.
Key Content And Findings:
SP-PN represents the most mature application of the platform, with multicenter cohorts and IDEAL-phase studies demonstrating perioperative and early oncologic outcomes comparable to multiport (MP)-PN. Retroperitoneal SP-PN, particularly using the low anterior access (LAA) technique, is associated with reduced postoperative pain, lower opioid requirements, and shorter hospitalization, which supports outpatient pathways in appropriately selected patients. SP-RN likewise shows perioperative safety comparable to MP approaches, with increasing preference for retroperitoneal access because this reduces external arm interference and improves exposure of the renal hilum. Single-port robotic-assisted radical nephroureterectomy (SP-RANU) remains in earlier stages of clinical adoption but demonstrates a consistent perioperative profile across institutions, and intracorporeal bladder cuff excision is feasible in most published series. Across all procedures, the current evidence is largely derived from early institutional experience with variability in cohort size, surgeon volume, and duration of follow-up. Comparative studies evaluating long-term oncologic outcomes remain limited.
Conclusions:
SP robotic surgery has become a validated and increasingly refined platform in renal and upper-tract oncology. SP-PN demonstrates perioperative and early oncologic equivalence to MP-PN, with distinct advantages in postoperative recovery. SP-RN and SP-RANU show promising early outcomes; however, larger comparative studies are required to determine long-term oncologic performance and optimal patient selection.

