Related Experiment Video
Updated: May 22, 2026
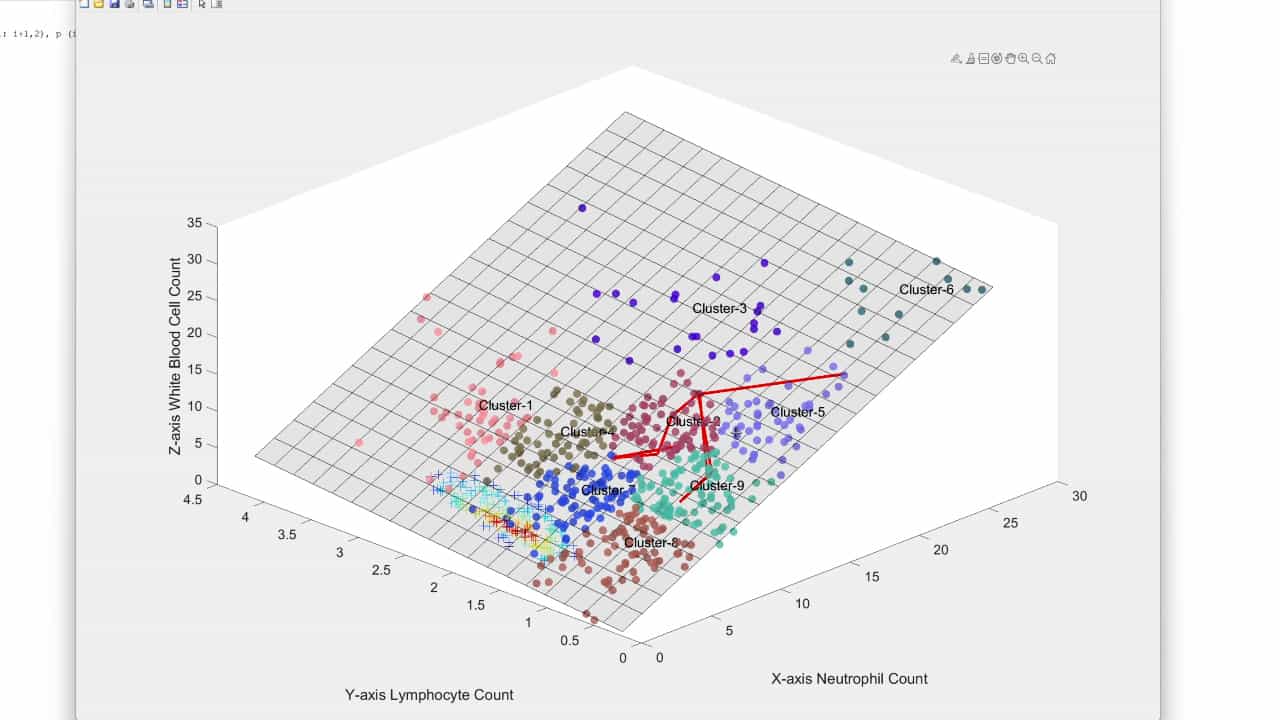
A Data-Driven Approach to Quantifying Immune States in Sepsis
Published on: February 7, 2025
Validation of SOFA-2 score in sepsis and exploration of its extension with additional immune markers
Fei Pei1,2, Bin Gu1,2, Zimeng Liu1,2
1Department of Critical Care Medicine, The First Affiliated Hospital, Sun Yat-sen University, Guangzhou, Guangdong, China.

Background:
The Sequential Organ Failure Assessment (SOFA) score is central to the diagnosis and management of sepsis, but its recent update has not been specifically evaluated in sepsis. Moreover, it is unknown whether adding immune markers beyond white blood cell (WBC) and lymphocyte counts-excluded in the recent update-could further improve its performance. The present study aimed to validate SOFA-2 in patients with sepsis and to examine its performance following integration of supplementary immune markers.
Methods:
This study is a secondary analysis of a multi-center randomized controlled trial in adult patients with sepsis conducted in China from September 2016 to December 2020. Both versions of SOFA were re-calculated at randomization, with an XGBoost-derived extension that incorporated additional immune markers, including WBC, lymphocyte counts, monocyte human leucocyte antigen-DR, neutrophil-to-lymphocyte ratio, and percentage of regulatory T cells. The discriminatory performance for predicting intensive care unit (ICU) mortality, evaluated by the area under the receiver operating characteristic curve (AUC), was examined.
Results:
Among the 1089 patients with sepsis (median age 64.5 years; 31.1% female), 9.2% died during ICU stay. The SOFA-2 was lower than the SOFA-1 (median [interquartile range] 6 [4-9] vs. 7 [5-10], P=0.001), primarily due to lower scores in the respiratory, cardiovascular, and liver domains, although higher values were observed in the kidney domain. Using a cut-off of 2, the two scores demonstrated highly concordant distributions; only 2.2% of patients had a SOFA-1 ≥2 but a SOFA-2 <2. The two scores demonstrated comparable discriminatory ability for predicting ICU mortality, with AUCs of 0.646 (95% confidence interval 0.595-0.698) for SOFA-2 and 0.641 (0.587-0.696) for SOFA-1. Incorporating any combination of the five immune markers into SOFA-2 did not result in significant changes in AUC.
Conclusions:
Updating from SOFA-1 to SOFA-2 results in comparable score distributions and sustains the discriminatory capacity for predicting ICU mortality in patients with sepsis. Immune dysregulation in sepsis may be too complex to capture with simple baseline markers.
Trial Registration:
clinicaltrials.gov NCT02867267.

