Related Experiment Video
Updated: May 23, 2026

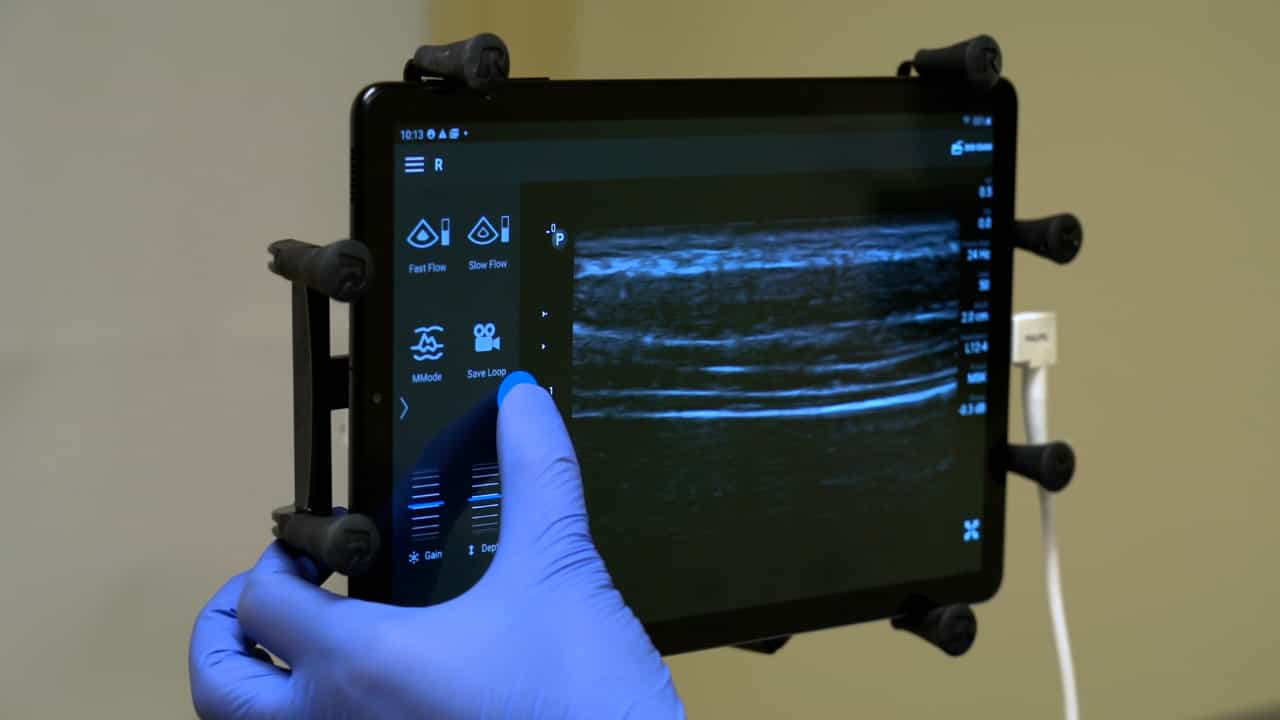
Diaphragmatic Ultrasound in Adults: Image Acquisition and Interpretation
Published on: January 31, 2025
Adaptive and degenerative remodeling of the diaphragm in patients with interstitial lung disease: A cross-sectional
Ozires Pereira Santos Ramos1, Mariana Matera Veras2, André Macedo Serafim Silva3
1Divisao de Pneumologia, Instituto do Coracao (InCor), Hospital das Clinicas HCFMUSP, Faculdade de Medicina, Universidade de Sao Paulo, Sao Paulo, SP, Brazil.

Abstract:
Interstitial lung diseases may affect the diaphragm due to continuous muscle overload caused by increased lung elastance, and functional alterations have already been described in patients with interstitial lung disease. However, the histological remodeling of the diaphragm is unknown. Our objective was to compare the histological and ultrastructural findings of the diaphragm in patients with and without interstitial lung disease. In this cross-sectional study with internal and external controls, we evaluated diaphragmatic and peripheral muscle (internal controls) biopsies from patients with and without chronic interstitial lung disease (external controls). Patients without interstitial lung disease underwent open lung biopsy for pulmonary nodules. Muscle samples were analyzed using histology, histochemistry, stereology, and electron microscopy. We quantified fiber type distribution, cross-sectional area, tissue volumes, and markers of adaptive and degenerative remodeling. We showed that diaphragms from patients with interstitial lung disease exhibited greater muscle, connective tissue, and nuclear volumes. Adaptive features included sarcomere elongation, and mitochondrial proliferation. Degenerative alterations comprised sarcomere misalignment, abnormal mitochondrial cristae, and collagen deposition. No significant differences were observed in peripheral muscles between patients with or without chronic interstitial lung disease. In conclusion, interstitial lung disease is associated with adaptive and degenerative diaphragmatic remodeling. These changes, absent in peripheral muscles, suggest a selective disease-specific effect. Identifying such alterations may guide interventions to preserve diaphragmatic function, inform rehabilitation programs design, and improve patient-centered outcomes, such as dyspnea.

Related Concept Videos
 01:24
Chronic Obstructive Pulmonary Disease III: Chronic Bronchitis Features
 01:23
Chronic Obstructive Pulmonary Disease II: Emphysema
 01:24
Cellular Adaptation IV: Dysplasia and Metaplasia
 01:20
Chronic Obstructive Pulmonary Disease-II: Pathophysiology
Chronic Inflammation
 01:10
Atelectasis II: Pathophysiology
 01:25
Chronic Obstructive Pulmonary Disease-III: Symptoms and Complications.
Symptoms of COPD can be classified as primary or systemic. Primary symptoms relate to reduced airflow, while systemic or extrapulmonary symptoms relate to COPD's broader impact on the body.
Primary Symptoms of COPD: