Related Experiment Video
Updated: May 23, 2026
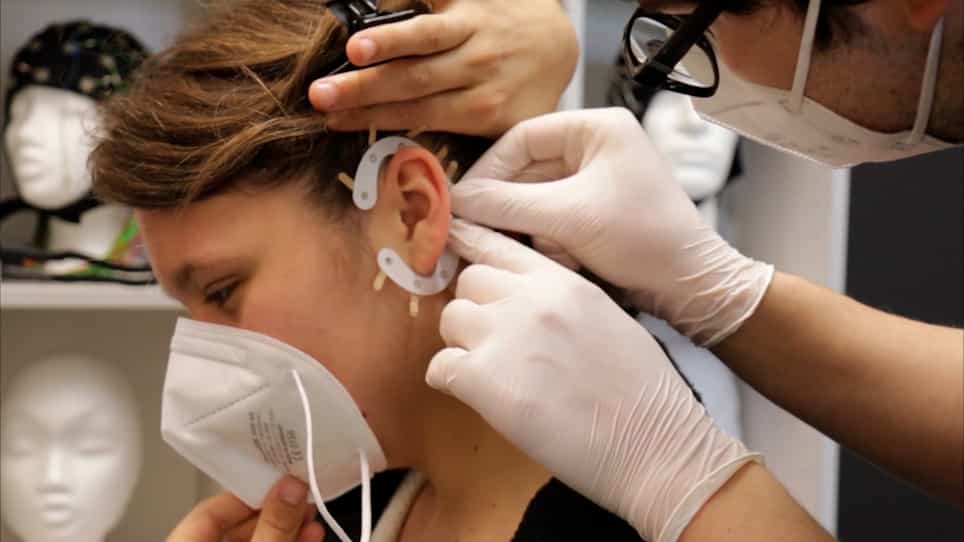

Recording Brain Activity with Ear-Electroencephalography
Published on: March 31, 2023
A novel, wearable, in-ear EEG technology to assess sleep and daytime sleepiness
Jonathan Berent1, Prabhjyot Saini2, Andrew X Stewart3
1NextSense Inc., Mountain View, California, USA. jb@nextsense.io.

Abstract:
In-ear electroencephalography (EEG) has emerged as a promising alternative to traditional in-laboratory sleep studies, offering greater comfort and practicality. Here we present a novel in-ear EEG system, comparing in-ear recordings against scalp EEG channels acquired concurrently as part of polysomnography (PSG). The study enrolled 16 healthy control participants in a single-visit overnight-plus-daytime design, and 8 participants with central disorders of hypersomnolence (CDH) in a randomized crossover daytime design (medication vs. medication-holiday). For overnight sleep recordings, ear-EEG and scalp EEG sleep staging showed substantial agreement (Cohen's [Formula: see text]). For daytime MWT trials, agreement was moderate (Cohen's [Formula: see text]), reflecting the predominance of wake epochs in this paradigm. For the primary Maintenance of Wakefulness Test (MWT) endpoint of sleep onset latency (SOL), at the per-subject level ([Formula: see text])-averaging across trials as in standard clinical practice-agreement was good (ICC = 0.71, [Formula: see text], MAD = 5.1 min). Among the 37 of 126 trials where both devices detected sleep (approximately 30% of trials), agreement was strong (ICC = 0.82, MAD = 1.9 min), with excellent agreement in healthy controls (ICC = 0.95, MAD = 1.2 min). Overall trial-level agreement across all 126 trials was moderate (ICC = 0.55), reflecting 22 discordant trials in which scalp EEG detected sleep but in-ear EEG did not-predominantly brief, subtle N1 transitions, concentrated in a subset of CDH participants. For overnight sleep architecture ([Formula: see text] healthy controls), total sleep time ([Formula: see text], ICC = 0.85), sleep efficiency ([Formula: see text]), and wake after sleep onset ([Formula: see text]) showed strong agreement, with small systematic biases consistent with reduced N1 detection sensitivity. These findings support the feasibility of in-ear EEG for sleep staging and daytime sleepiness assessment in laboratory settings, and motivate larger confirmatory studies-including home-based longitudinal monitoring-to establish clinical utility, particularly in populations with altered sleep architecture.

