Related Experiment Video
Updated: May 23, 2026


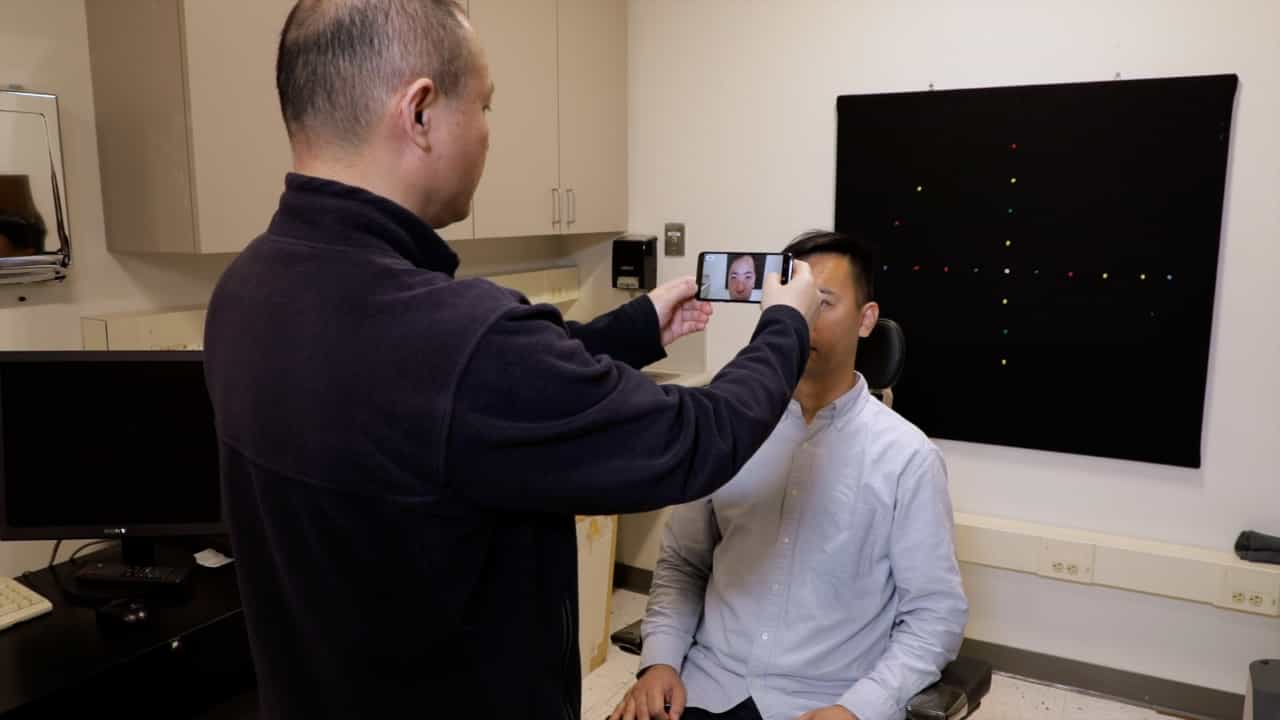
Using an Automated Hirschberg Test App to Evaluate Ocular Alignment
Published on: March 24, 2020
Using the Refugee Health Screener with Children and Young People Seeking Asylum and Refugees who are unaccompanied
Alexandra Cardoso Pinto1,2, Zoe Given-Wilson3,4, Nikola Mongey3
1School of Public Health, Imperial College London, United Kingdom.

Introduction:
Children and Young People seeking asylum and refugees who are unaccompanied (CYPSAR-U) have a high risk of developing depression, anxiety, and post-traumatic stress disorder (PTSD), yet culturally sensitive screening approaches remain limited. This evaluation explored the use of the Refugee Health Screener (RHS), focusing on patient outcomes and healthcare professionals' experiences of administration.
Methods:
A mixed-methods service evaluation was conducted in two London-based clinics. The demographics, language, interpreter use, and RHS scores were extracted from electronic health records of 115 CYPSAR-U screened using either the RHS-13 (West London Clinic, WLC) or RHS-15 (North London Clinic, NLC) and analysed descriptively. Semi-structured discussions with 10 healthcare professionals who administered the RHS across both clinics were examined using content analysis.
Results:
In WLC, 48 CYPSAR-U (median age 16 years, 87.5% male) mainly originated from Eritrea (21.3%), Sudan (17.0%), and Ethiopia (12.8%), while in NLC, 67 CYPSAR-U (median age 17 years, all male) were primarily from Iran (20.9%), Sudan (20.9%), Eritrea (13.4%), and Iraq (13.4%). In the WLC RHS assessments were mostly conducted in English (52.1%) or Arabic (33.3%), with interpreters in 85.4% of consultations. At the NLC all were in English with an interpreter. At the WLC, 56% of young people scored above the clinically significant threshold of the RHS, requiring further assessment and support. At the NLC, 67% scored above the RHS clinically significant threshold. Most frequently endorsed symptoms were low mood and excessive thoughts. Clinicians reported that the RHS supported early identification, facilitated multidisciplinary communication, and helped build rapport with young people. However, challenges included linguistic and cultural barriers, interpreter variability, time pressures, and difficulties in comprehension for some CYPSAR-U.
Conclusion:
Within the two evaluated services, the RHS provided a structured approach to support early identification of emotional distress among CYPSAR-U and facilitated communication between healthcare professionals across services. However, challenges related to cross-cultural communication and interpretation were identified. These findings highlight the importance of using the RHS alongside clinical judgement and embedding it within trauma-informed care pathways in similar service contexts.