Related Experiment Video
Updated: May 24, 2026
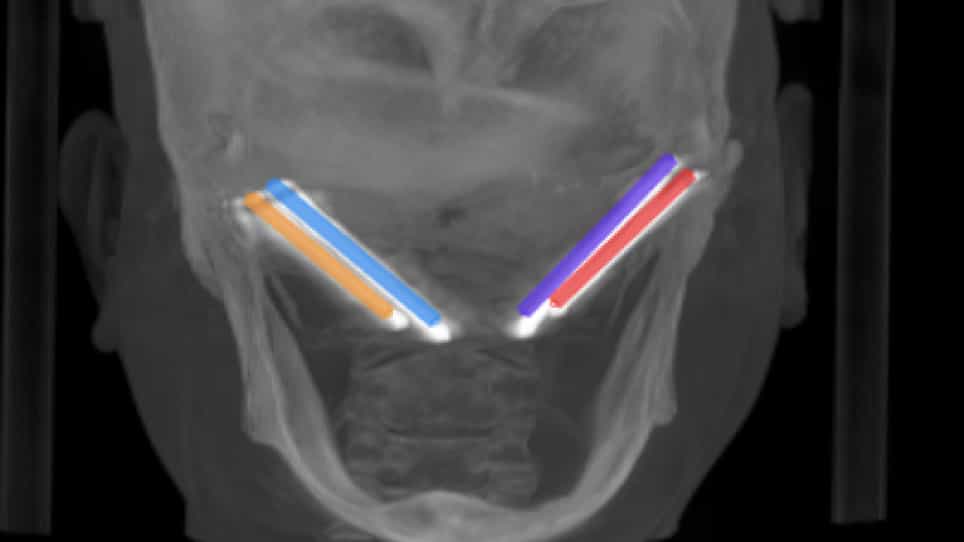
Real-Time Dynamic Navigation System for the Precise Quad-Zygomatic Implant Placement in a Patient with a Severely Atrophic Maxilla
Published on: October 18, 2021
Posterior superior alveolar artery in severely atrophic maxillae prior to lateral sinus augmentation: a retrospective
Halil Ibrahim Aygun1,2, Duygu Taskin3, Emin Murat Canger4
1Department of Periodontology, Faculty of Dentistry, Nigde Omer Halisdemir University, Nigde, Turkey. iaygun@ohu.edu.tr.

Background:
Vascular injury to the posterior superior alveolar artery (PSAA) during lateral sinus floor augmentation is a recognized surgical complication, yet data on PSAA anatomy in severely atrophic edentulous maxillae remain scarce. This study aimed to evaluate the prevalence, location patterns, and morphometric characteristics of the PSAA in this specific population using cone-beam computed tomography (CBCT).
Methods:
Preoperative CBCT scans of 121 patients (242 sinuses) with severely atrophic posterior maxillae (residual ridge height ≤ 5 mm) were retrospectively analyzed. PSAA location was classified as intraosseous (Type I), submembranous (Type II), extraosseous (Type III), or transosseous (Type IV). PSAA diameter and vertical distances to the sinus floor (PSAA-SF) and alveolar crest (PSAA-ALV) were measured. Generalized estimating equations accounted for within-patient correlation from bilateral evaluations.
Results:
The PSAA was identified in 99.17% of sinuses, predominantly Type II (56.67%), followed by Type I (37.50%), Type IV (3.33%), and Type III (2.50%). Mean PSAA diameter was 1.02 ± 0.56 mm, mean PSAA-SF distance 8.89 ± 4.61 mm, and mean residual ridge height 3.55 ± 1.37 mm. Type II location was significantly associated with Schneiderian membrane thickening (p = 0.018).
Conclusions:
In severely atrophic edentulous maxillae planned for lateral sinus floor augmentation, the PSAA predominantly follows a submembranous course alongside a clinically critical transosseous variant. Preoperative CBCT assessment of the PSAA is essential to inform individualized surgical planning and minimize hemorrhagic risks.
