Related Experiment Video
Updated: May 25, 2026


Ultrasound-Guided Needle Release Combined with Corticosteroid Injection for the Treatment of Supinator Syndrome
Published on: May 26, 2023
Resolution of Pediatric Trigger Finger After Combined A1 Pulley Release, A2 Pulley Partial Release, and Flexor
Timothy W Kouo1, Dan Gordon2, Aaron Perkins3
1The Anne Burnett Marion School of Medicine at Texas Christian University, Fort Worth, TX.

Insights
Pediatric trigger fingers (PTFs) often recur after A1 pulley release. Combining A1 pulley release with A2 pulley partial release and flexor digitorum superficialis (FDS) splitting effectively treated PTFs, showing no recurrence in a 6-year follow-up.
Area of Science:
- Orthopedic Surgery
- Pediatric Hand Surgery
- Reconstructive Surgery
Background:
- Pediatric trigger finger (PTF) presents a high recurrence rate following isolated A1 pulley release.
- The flexor digitorum superficialis (FDS) splitting technique offers a potential solution to mitigate PTF recurrence.
- This approach aims to avoid the need for more extensive surgical dissection.
Purpose of the Study:
- To investigate the clinical outcomes of treating pediatric trigger fingers (PTFs).
- The study specifically evaluates A1 pulley release combined with A2 pulley partial release and FDS splitting.
- To assess the efficacy of this combined surgical technique in preventing PTF recurrence.
Main Methods:
- Retrospective review of patients diagnosed with PTF from January 2010 to July 2025.
- Inclusion criteria: patients over 18 years old undergoing surgical treatment for PTF.
- Descriptive statistics were used to analyze recurrence rates and follow-up duration.
Main Results:
- A total of 25 patients (38 digits) were included in the study.
- No cases of recurrent PTF were observed at the initial postoperative visit (median 14 days).
- At a median 6-year follow-up, no patients reported pain or recurrence of PTF.
Conclusions:
- A1 pulley release with concomitant A2 pulley partial release and FDS splitting shows favorable outcomes for PTF.
- This combined technique resulted in zero recurrence and no reported pain at final follow-up.
- Incorporating FDS splitting may reduce early PTF recurrence without extensive dissection.
Purpose:
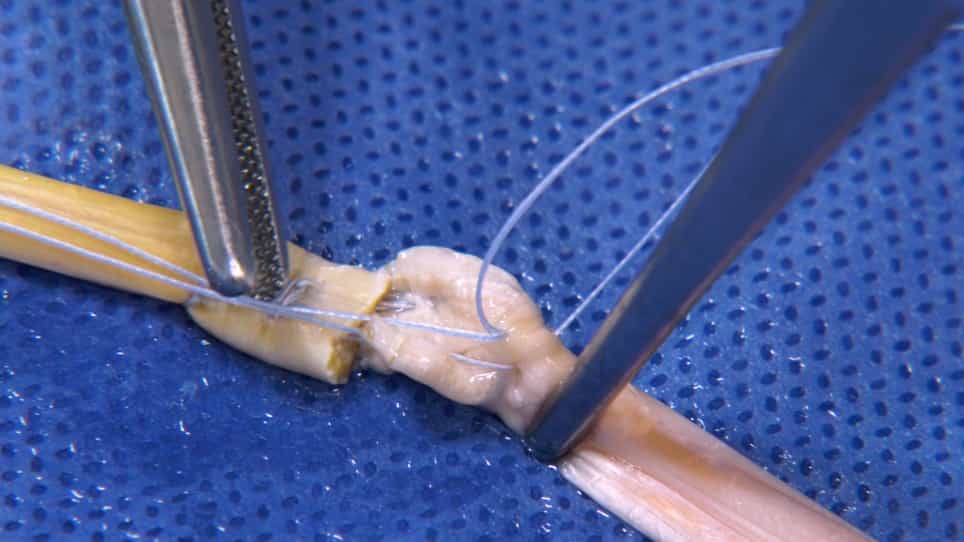
Unlike pediatric trigger thumb, which is cured by A1 pulley release, pediatric trigger fingers (PTFs) have a high rate of recurrence with A1 pulley release alone. The flexor digitorum superficialis (FDS) splitting technique has the potential to mitigate recurrence without the need for more extensive dissection. This study investigates the clinical outcomes of A1 pulley release with concomitant A2 pulley partial release and FDS splitting in the treatment of PTF.
Methods:
A retrospective review was conducted at our institution, examining patients with PTF from January 2010 to July 2025. Inclusion criteria consisted of patients aged >18 years who underwent surgical treatment for PTF. Descriptive statistics were used to determine the rate of retrigger and the average length of follow-up after surgery.
Results:
A total of 25 patients and 38 fingers met the inclusion criteria. Average age at surgery was 7 years (range, 1-16 years) with most patients being woman (60%), not Hispanic or Latino (63%), and White (90%). Of the treated digits, 8% were index fingers, 18% were ring fingers, 26% were little fingers, and 47% were middle fingers. No cases of recurrent PTF were observed at the first postoperative visit, occurring at a median of 14 days (range, 4-79 days) after surgery. Three patients did report stiffness and pain, but these symptoms resolved with continued mobilization. At final follow-up, which occurred at a median of 6 years (range, 2-13 years) after the initial postoperative visit, no patients reported pain or recurrence of PTF.
Conclusions:
The A1 pulley release with concomitant A2 pulley partial release and FDS splitting demonstrated favorable outcomes in the treatment of PTF. Of the 38 treated digits, no cases of recurrence or pain were observed at the final postoperative follow-up. This suggests that incorporating FDS splitting may help reduce early recurrence without requiring extensive dissection beyond the A2 pulley.
Type Of Study/Level Of Evidence:
Therapeutic IV.