Related Experiment Video
Updated: May 25, 2026

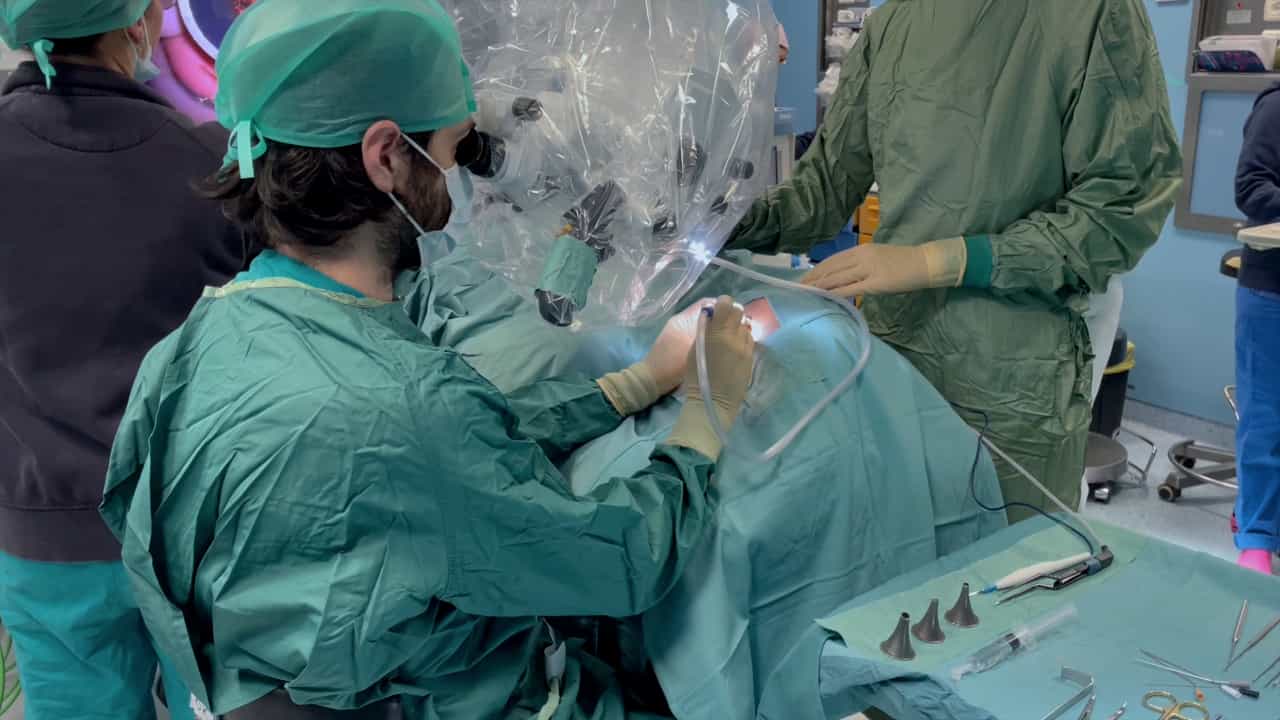
Endoscopic Endonasal Trans-sphenoidal Approach: Minimally Invasive Surgery for Pituitary Adenomas
Published on: January 17, 2018
Determinants of remission and recurrence following transsphenoidal surgery for prolactinoma: a single-center
William M Burns1, Gurkirat Kohli1, Lu Wang2
1Department of Neurosurgery, University of Rochester Medical Center, Rochester, NY, USA.

Purpose:
To identify clinical, radiographic, and biochemical predictors of acute surgical remission (ASR), long-term remission (LTR), and recurrence in patients undergoing endoscopic transsphenoidal surgery (ETSS) for prolactinoma.
Methods:
A retrospective cohort study was conducted on 52 patients who underwent ETSS for histologically confirmed prolactinoma at a single center between 2010 and 2022.
Results:
Remission was more likely in patients with microadenomas (ASR 72.2% vs. 41.2% macroadenomas, p = 0.03; LTR 44.4% vs. 17.6%, p = 0.052), Knosp 0-1 tumors (ASR 66.7% vs. 18.8% Knosp 2-4, p = 0.001; LTR 38.9% vs. 0%, p = 0.004), absence of cavernous sinus invasion (ASR 62.2% vs. 26.7%, p = 0.02; LTR 37.8% vs. 0%, p = 0.005), completely resected tumors (ASR 75.0% vs. 25.0%, p < 0.001; LTR 50.0% vs. 0%, p < 0.001). Patients achieving LTR had lower postoperative prolactin (4.5 vs. 28.0 ng/mL, p = 0.01). Median follow-up duration was 5.6 years, and median time to recurrence was 2.6 years. Recurrence was associated with higher peak prolactin (HR 1.003 per ng/mL, 95% CI: 1.001-1.01, p = 0.01), Knosp 2-4 tumors (HR 5.64, 95% CI: 1.40-22.80, p = 0.02), cavernous sinus invasion (HR 3.97, 95% CI: 1.15-13.64, p = 0.03), subtotal resection (HR 0.19 for GTR, 95% CI: 0.06-0.60, p = 0.01), and higher postoperative prolactin (HR 1.13 per ng/mL, 95% CI: 1.04-1.23, p = 0.01).
Conclusion:
Tumor size, invasiveness, extent of resection, and prolactin levels are key predictors of remission and recurrence. These findings underscore risk-stratified decision-making and long-term surveillance.