Related Experiment Video
Updated: May 26, 2026
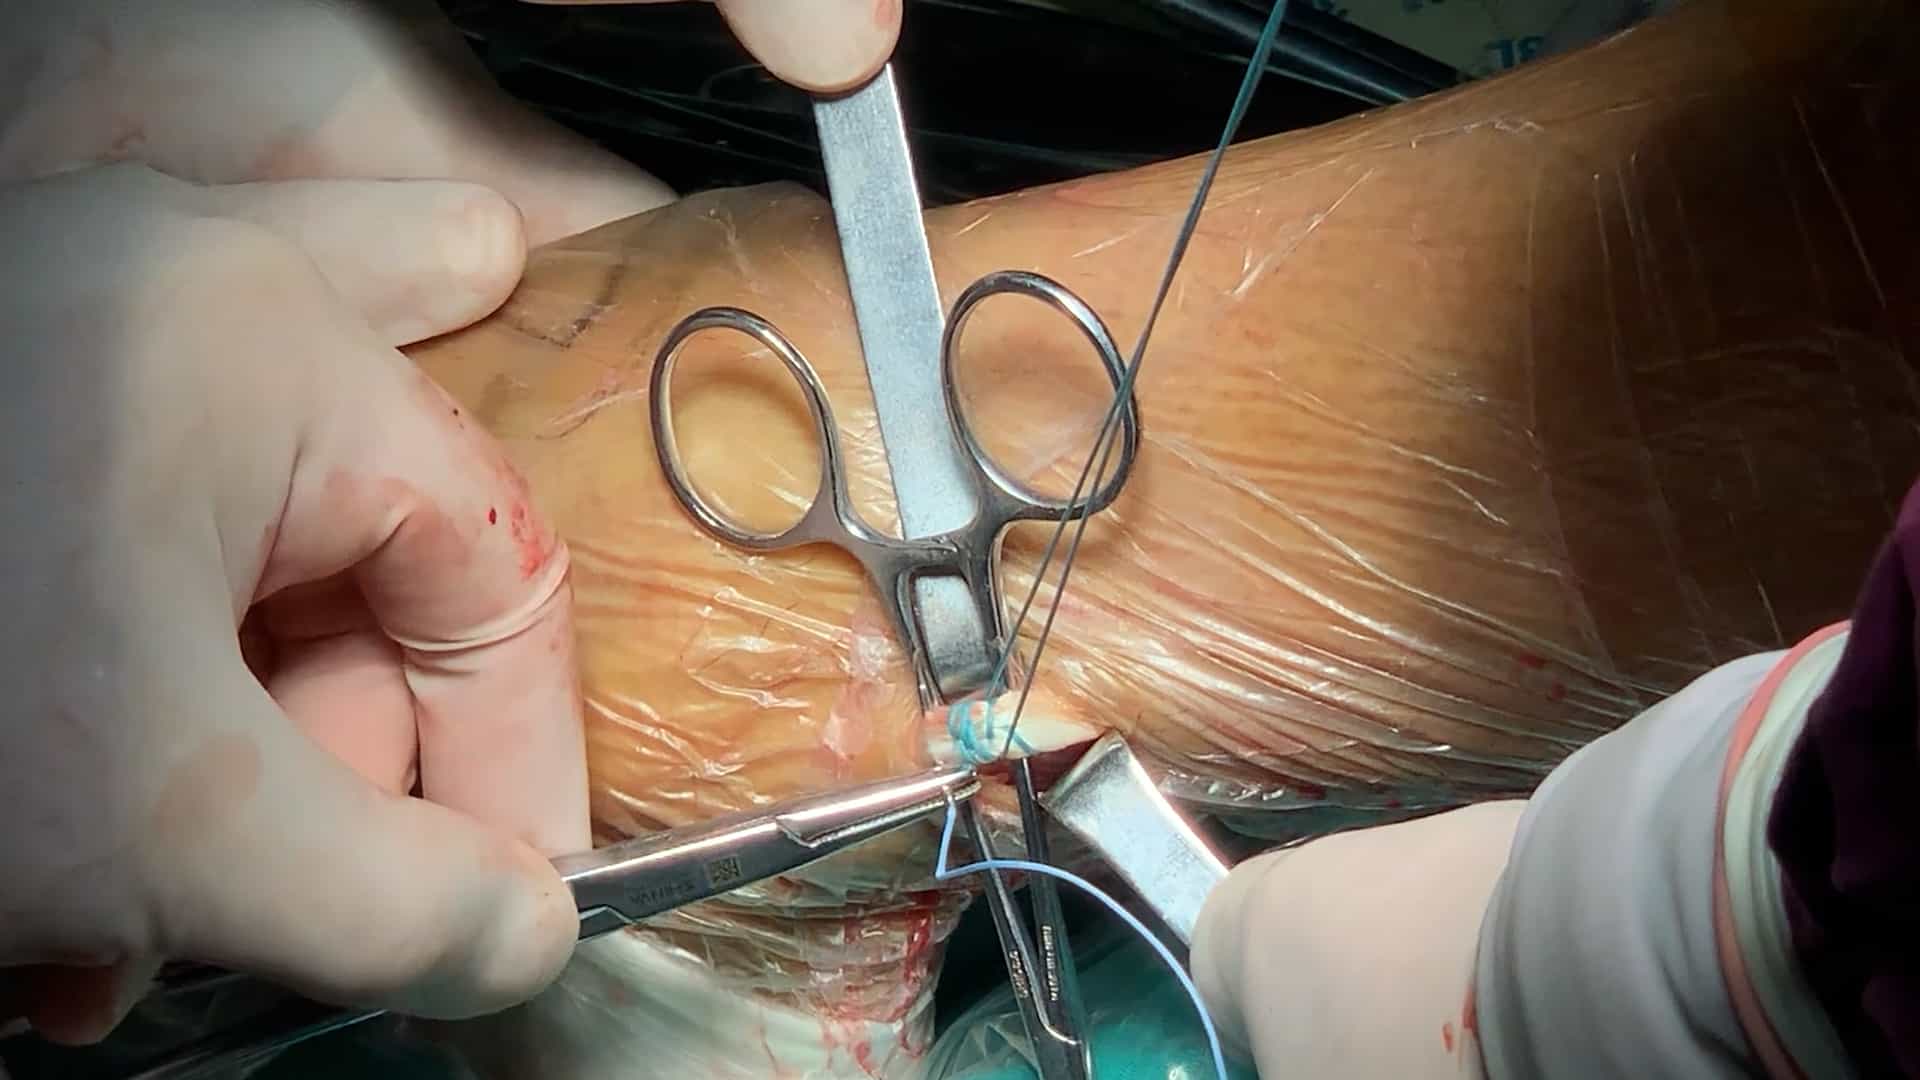
Harvesting of Peroneus Longus Tendon Autograft
Published on: September 2, 2025
Higher body mass index is associated with smaller hamstring autograft diameter in primary anterior cruciate ligament
Horacio Rivarola1, Cristian Collazo1, Marcos Palanconi1
1Hospital Universitario Austral, Buenos Aires, Argentina.

Background:
Hamstring autograft diameter is an important determinant of mechanical strength and clinical outcomes after anterior cruciate ligament (ACL) reconstruction. Smaller graft diameters, particularly those below 8 mm, have been associated with increased risk of graft failure. While several anatomical and demographic factors influencing graft size have been investigated, the potential influence of systemic metabolic factors such as obesity and comorbidity burden on autograft morphology remains poorly understood.
Methods:
A retrospective consecutive cohort study was conducted including 120 patients who underwent primary ACL reconstruction using hamstring autograft. Body mass index (BMI) was analyzed both as a continuous variable and according to predefined categories (<30, 30-34.9, and ≥35 kg/m2). Systemic comorbidity burden was quantified using the Charlson Comorbidity Index. The primary outcome was intraoperative hamstring graft diameter measured using a calibrated sizing block. The secondary outcome was a graft diameter <8 mm. Multivariable linear regression was used to assess independent predictors of graft diameter, while logistic regression evaluated factors associated with grafts <8 mm. Models were adjusted for age, sex, and comorbidity burden.
Results:
The mean graft diameter was 8.5 ± 0.9 mm, and 24.2% of patients had grafts <8 mm. In a multivariable analysis, higher BMI was independently associated with smaller graft diameter (β = -0.24 mm per 5 kg/m2 increase; 95% confidence interval [CI]: -0.41 to -0.07; p = 0.006). Patients with a BMI ≥35 kg/m2 demonstrated significantly smaller adjusted mean graft diameter than those with a BMI <30 kg/m2 (difference: -0.62 mm; p = 0.001). A higher BMI was statistically significant for increased odds of a graft diameter <8 mm (adjusted odds ratio [OR]: 1.68; 95% CI: 1.18 to 2.39; p = 0.004). Comorbidity burden was not independently associated with graft diameter or with the probability of grafts <8 mm.
Conclusion:
higher BMI is independently associated with a smaller hamstring autograft diameter and with an increased likelihood of obtaining a graft measuring less than 8 mm during primary ACL reconstruction. These findings suggest that systemic anthropometric factors may influence intraoperative graft characteristics and should be considered during preoperative planning and graft selection strategies.
Level Of Evidence:
III, retrospective cohort study.
