Related Experiment Video
Updated: May 26, 2026
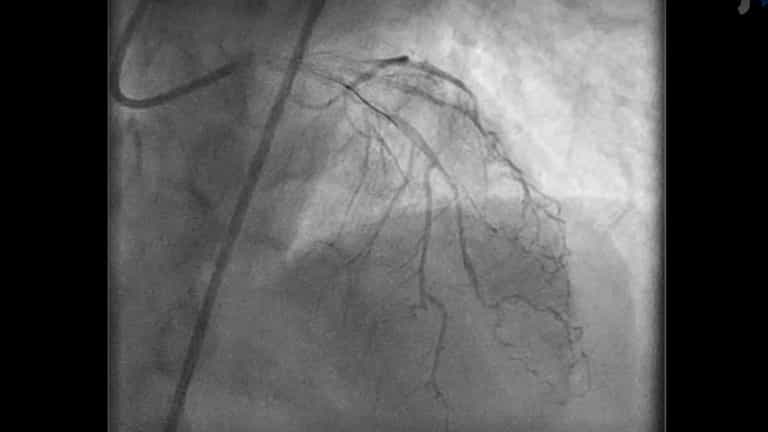

Acetylcholine Re-Challenge After Intracoronary Nitroglycerine Administration
Published on: April 4, 2022
Historical Evolution of the Guideline Statements on Vasospastic Angina (Coronary Spastic Angina) and Coronary
Seiji Hokimoto1, Kenichi Tsujita2
1Division of Cardiovascular Medicine, Social Insurance Omuta Tenryo Hospital, Japan.

Insights
Ischemic heart disease management now includes vasospastic angina (VSA) and coronary microvascular dysfunction (CMD) for patients with non-obstructive coronary arteries. Guidelines increasingly recognize these conditions, improving diagnosis and treatment for angina/ischemia with non-obstructive coronary arteries (ANOCA/INOCA).
Area of Science:
- Cardiology
- Internal Medicine
- Clinical Practice Guidelines
Background:
- Traditional ischemic heart disease management targets obstructive epicardial coronary artery disease.
- A significant number of patients with angina and ischemia lack significant coronary stenosis.
- Vasospastic angina (VSA) and coronary microvascular dysfunction (CMD) are key causes of angina/ischemia with non-obstructive coronary arteries (ANOCA/INOCA).
Purpose of the Study:
- To review the historical development of guideline-based understanding of VSA and CMD.
- To discuss the clinical implications of evolving perspectives on VSA and CMD for contemporary practice.
Main Methods:
- Literature review focusing on guideline evolution and diagnostic criteria.
- Analysis of historical and recent clinical practice guidelines.
- Synthesis of information on VSA and CMD diagnosis and management.
Main Results:
- Japanese guidelines pioneered VSA diagnosis via spasm provocation testing.
- International guidelines now emphasize CMD as a distinct entity.
- Coronary functional assessment (invasive and non-invasive) is increasingly recommended for CMD.
Conclusions:
- Guideline-based perspectives on VSA and CMD have evolved significantly.
- Contemporary management of ANOCA/INOCA requires consideration of VSA and CMD.
- Further integration of VSA and CMD assessment into clinical practice is essential.
Abstract:
The management of ischemic heart disease has traditionally focused on obstructive epicardial coronary artery disease. However, a substantial proportion of patients with angina and objective myocardial ischemia have no significant coronary stenosis. Vasospastic angina (VSA; also termed coronary spastic angina [CSA] ) and coronary microvascular dysfunction (CMD) are now recognized as major mechanisms underlying angina/ischemia with non-obstructive coronary arteries (ANOCA/INOCA). These evolving concepts have been progressively incorporated into the clinical practice guidelines. Japanese guidelines have played a pioneering role in establishing diagnostic criteria for VSA through coronary spasm provocation testing. More recently, international guidelines have emphasized CMD as a distinct clinical entity and recommended coronary functional assessment using both invasive and non-invasive modalities. This review summarizes the historical evolution of the guideline-based perspectives on VSA and CMD and discusses their implications for contemporary clinical practice.


Related Concept Videos
 01:29
Angina III: Clinical Manifestations and Assessment
 01:30
Coronary Artery Disease III: Clinical Manifestations
 01:21
Peripheral Arterial Disease II: Clinical Manifestations and Diagnostic Evaluation
 01:19
Acute Coronary Syndrome II: Pathophysiology and Clinical Manifestations
 01:30
Angina I: Introduction
 01:26
Coronary Artery Disease II: Pathophysiology