Related Experiment Video
Updated: May 26, 2026
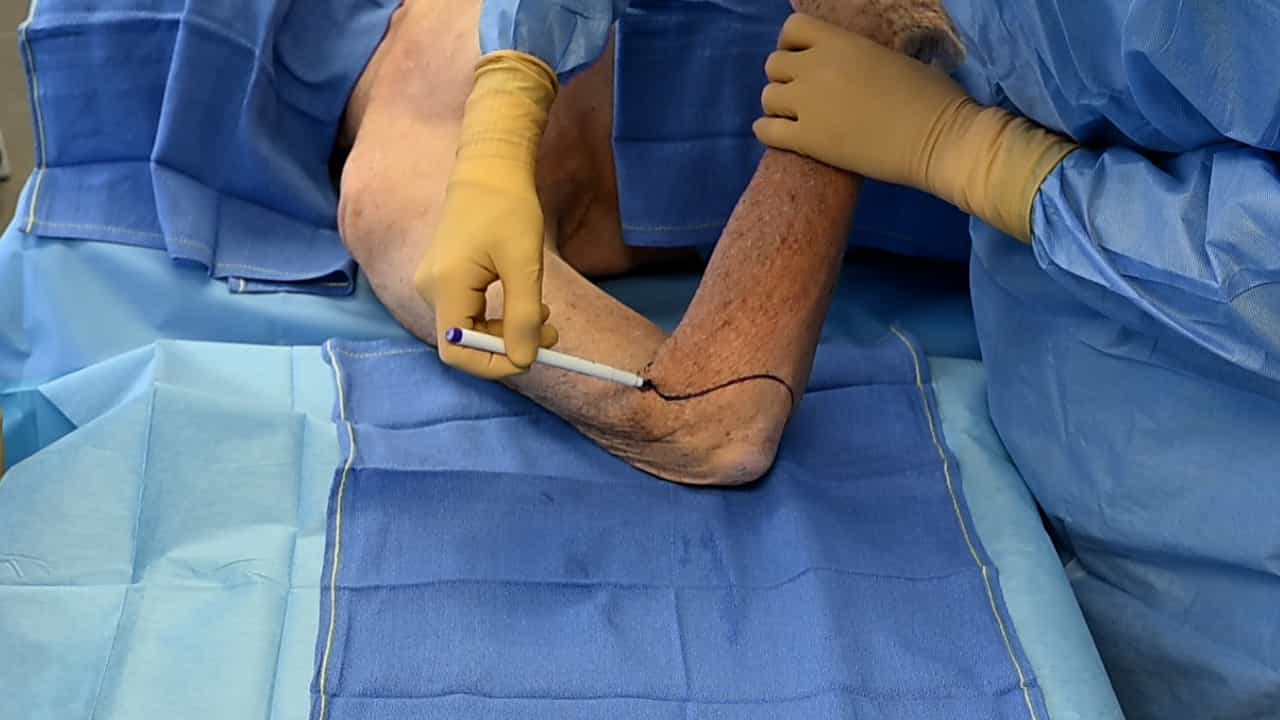

Vascularized Composite Hand Allograft Procurement and Preparation for Distal and Proximal Forearm Allotransplantation: A Stepwise Approach
Published on: May 23, 2025
Anatomical reconstruction of chronic mallet finger using a split palmaris longus graft with distal reinforcement
J Terrence Jose Jerome1,2, G Surendran1,3, K Thirumagal1
1Olympia Hospital & Research Centre, 47, 47A Puthur High Road, Puthur, Trichy, Tamilnadu, 620017, India.

Background:
Chronic tendon mallet finger with severe distal interphalangeal (DIP) joint extension lag remains a challenging condition, particularly when primary repair is not feasible. This study describes a modified anatomic reconstruction technique using a split palmaris longus (PL) tendon graft with distal reinforcement and evaluates clinical and functional outcomes using the Extensor Tendon Reconstruction Outcome Score (EXTROS).
Methods:
Fourteen patients (mean age, 37 years; range, 21-56 years) with chronic tendon mallet deformity and extension lag >40° underwent reconstruction using a Y-configured PL tendon graft to restore the terminal extensor mechanism and lateral bands. The graft was anchored to the distal phalanx, passed beneath the transverse retinacular ligament, secured to the lateral bands, and reinforced distally over the terminal tendon insertion. Active DIP joint motion was assessed preoperatively and at final follow-up. Outcomes were graded using Miller's criteria and EXTROS. Complications were recorded.
Results:
The mean preoperative DIP extension lag was -60° (range, -40° to -90°), improving to -10° (range, -20° to 0°) at final follow-up (mean improvement, 53.9°; P < .001). According to Miller's classification, outcomes were excellent in 4 patients (29%), good in 8 (57%), and fair in 2 (14%). EXTROS grading demonstrated good outcomes in 12 patients (86%) and fair outcomes in 2 (14%), with no poor results. Two patients developed superficial dorsal skin infection, which resolved with oral antibiotics. One patient developed a nailbed deformity. No tendon rupture or graft failure was observed.
Conclusions:
Anatomic reconstruction of chronic tendon mallet finger using a split PL tendon graft with distal reinforcement provides reliable correction of severe extension lag. Functional evaluation using EXTROS demonstrated high rates of good recovery, supporting the reproducibility and durability of this reconstructive approach. This technique represents a safe and effective option for selected patients with severe chronic mallet deformity.
Type Of Study / Level Of Evidence:
Therapeutic, Level IV.