Related Experiment Videos
Applying gastric residual volume as one of the indicators for enteral feeding intolerance: A scoping review
Duc T Nguyen1, An T Bui2, Anh K Dang3
1Department of Emergency & Intensive Care, Vietnam National Cancer Hospital, Hanoi, Vietnam.

Rationale:
Measuring gastric residual volume (GRV) remains common in intensive care units (ICUs), despite weak evidence linking it to enteral feeding intolerance (EFI), gastric emptying, aspiration, or ventilator-associated pneumonia. Thresholds defining high GRV vary widely (75-1200 ml). This scoping review aimed to: (1) identify GRV thresholds indicating feeding intolerance in adult ICU patients; and (2) describe GRV-related management practices.
Methods:
This review was conducted following the Population-Concept-Context (PCC) framework. A comprehensive search was performed in PubMed and Web of Science, extracting studies published in English and Vietnamese from 2010 to 2024. Studies were eligible if they were original research, trials, pre-and-post intervention study, and case reports/case series, and reported both GRV threshold and specific management strategies, while reviews or other studies that only had either GRV cutoff or its interventions were excluded.
Results:
Among 73 records for screening, 25 studies were eligible. Most involved hemodynamically stable, mechanically ventilated ICU patients receiving enteral nutrition (EN). GRV monitoring was typically performed every 4-6 h, with the cutoff ranging from 150 to 500 mL. Most studies used 200-250 mL as the most frequently used reference point. Some other studies combined GRV and clinical symptoms-such as nausea, vomiting, or distension-to determine intolerance. When GRV was below the lower threshold, feeding was typically continued or increased by 10-30 mL/h. Elevated GRV prompted various interventions, including temporary suspension of EN, prokinetic administration, or transition to post-pyloric nutrition.
Conclusion:
Most studies used 200-250 mL as a cautious GRV threshold for an early recognition of feeding intolerance, and the time to check GRV was normally every 4-6 h. Management of high GRV for lower thresholds tended to be less absolute, by reducing feeding rate and prescribing prokinetics, while stricter management was performed if GRV exceeded the higher GRV threshold.
Related Concept Videos
 01:15
Enteral Nutrition II: Nasointestinal and Gastrostomy Feeding
Nasointestinal Feeding
Nasointestinal feeding involves placing a tube through...
 01:26
Enteral Nutrition I: Orogastric and Nasogastric Feeding
Orogastric (OG) and nasogastric (NG) feeding are two standard methods used for enteral nutrition. Enteral nutrition is often preferred over...
 01:16
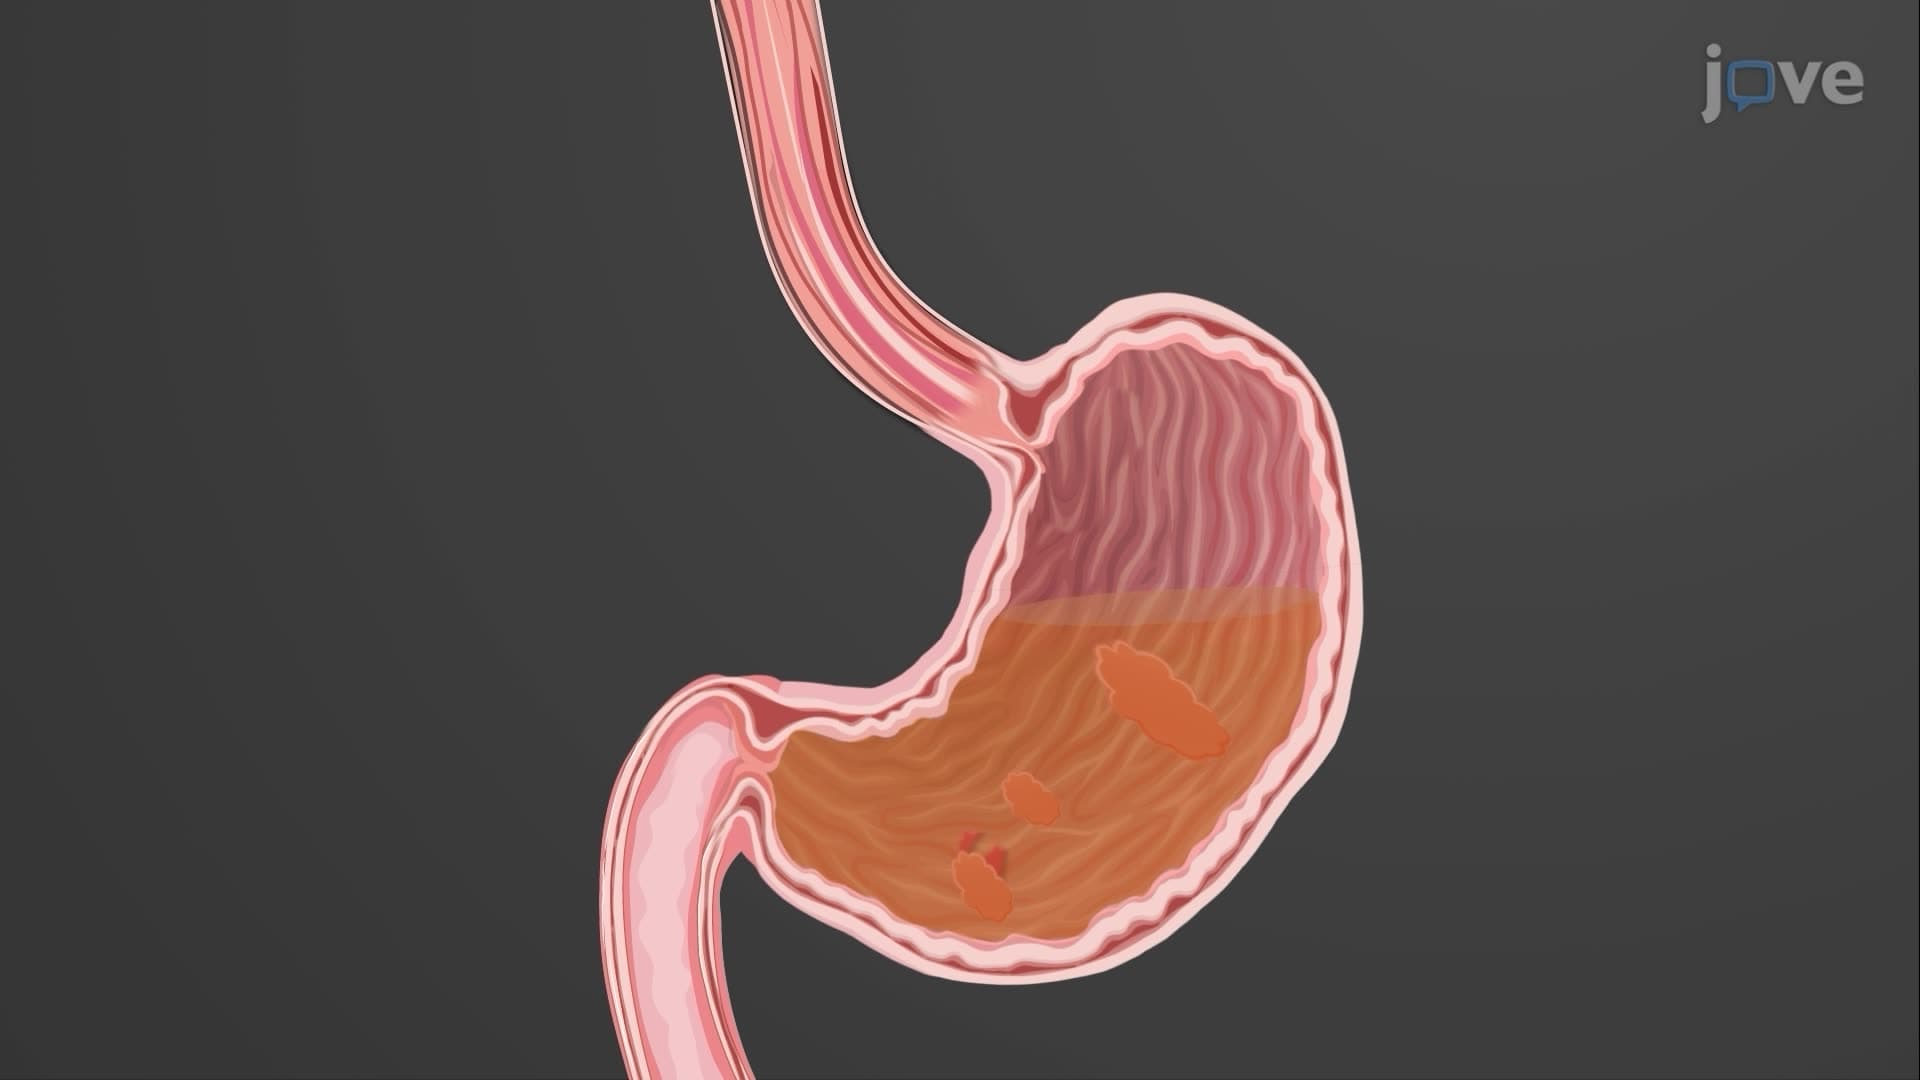
Gastric Emptying
 01:17
Assessment of the Gastrointestinal System I: Subjective Data
Health History
The initial step in assessing the GI system is obtaining a comprehensive health history. This includes inquiring about the patient's history or presence of problems related to...
 01:29
Assessment of the Gastrointestinal System II: Health Perception Pattern
Health Perception Patterns
Health perception patterns offer valuable insights into a patient's lifestyle habits and how they may impact their GI health. These patterns include:
 01:29
Gastroesophageal Reflux Disease II: Clinical Features and Management
Clinical Manifestations
GERD presents itself in a multitude of ways, with symptoms varying from person to person. The hallmark symptoms are...