Related Experiment Video
Updated: May 27, 2026

Improved Renal Denervation Mitigated Hypertension Induced by Angiotensin II Infusion
Published on: May 26, 2022
Beta-blockers in patients with uncomplicated arterial hypertension: data from the Campania Salute Network Registry
Christian Basile1,2, Costantino Mancusi3, Ilaria Fucile3
1ANMCO Research Center, Heart Care Foundation, 50121 Florence, Italy.

Insights
Beta-blocker use in uncomplicated hypertension did not lower major adverse cardiovascular events (MACE). Adherence to other medications like statins showed benefit, suggesting alternative treatments are preferred.
Area of Science:
- Cardiology
- Pharmacology
- Hypertension Management
Background:
- Beta-blockers are standard for heart failure and post-MI care.
- Their role in uncomplicated hypertension for reducing major adverse cardiovascular events (MACE) is debated.
- This study investigates beta-blocker efficacy in a real-world hypertensive population without prior cardiovascular disease.
Purpose of the Study:
- To evaluate the association between beta-blocker use and MACE in hypertensive patients without cardiovascular disease.
- To assess if beta-blocker therapy reduces cardiovascular events in this specific population.
- To compare beta-blocker efficacy against other antihypertensive and lipid-lowering medications.
Main Methods:
- Analysis of 6,702 hypertensive patients from the Campania Salute Network (CSN) registry.
- Utilized multivariable Cox regression, propensity score matching (PSM), and overlap weighting (OW) for association analysis.
- Included intention-to-treat (ITT) and per-protocol (PP) sensitivity analyses for adherence.
Main Results:
- Beta-blocker use (18.1% of patients) was not associated with a reduced risk of MACE in ITT or PP analyses (HRs ranging from 1.10 to 1.18).
- Adherence to renin-angiotensin system inhibitors and statins was linked to a lower MACE risk.
- Beta-blocker users had a higher prevalence of metabolic risk factors.
Conclusions:
- Beta-blocker therapy is not associated with reduced MACE in uncomplicated hypertension, irrespective of adherence.
- Findings support current guidelines prioritizing non-beta-blocker regimens for this patient group.
- Alternative medications like statins and RAS inhibitors demonstrate greater cardiovascular benefit.
Aims:
The role of beta-blockers in the management of uncomplicated arterial hypertension remains a subject of clinical debate. While beta-blockers are established cornerstones for heart failure and post-myocardial infarction care, their independent efficacy in reducing major adverse cardiovascular events (MACE) in patients without these compelling indications is less clear. This study aimed to evaluate the association between beta-blocker use and MACE in a real-world hypertensive population without prevalent cardiovascular diseases.
Methods And Results:
We analysed 6702 hypertensive patients from the Campania Salute Network (CSN) registry without prevalent coronary or cerebrovascular disease, valvular heart disease, or heart failure. The association between beta-blocker use and MACE was assessed using three statistical approaches: multivariable-adjusted Cox proportional hazards regression, propensity score matching (PSM), and overlap weighting (OW). An intention-to-treat (ITT) analysis was performed based on baseline prescription, and an exploratory per-protocol (PP) sensitivity analysis was conducted to evaluate the role of sustained treatment adherence. At baseline, 18.1% (n = 1247) of patients were receiving a beta-blocker. Over a median follow-up of 52 months, 308 MACE (4.5%) occurred. After multivariable adjustment and weighting, beta-blocker use was not associated with a lower risk of MACE in the ITT population (Adjusted hazard ratio [HR] 1.15, 95% confidence interval [CI] 0.86-1.52; PSM HR 1.18, 95% CI 0.82-1.70; OW HR 1.10, 95% CI 0.82-1.46). In the exploratory PP sensitivity analysis, even among adherent patients, beta-blocker therapy was not associated with a lower risk of MACE. Conversely, adherence to renin-angiotensin system inhibitors and statins was associated with a lower risk of MACE. Beta-blocker users also exhibited a higher prevalence of metabolic risk factors, including elevated triglycerides, glycaemia, and uric acid levels.
Conclusion:
In patients with uncomplicated hypertension, beta-blocker use was not associated with a lower risk of MACE, regardless of treatment adherence. These findings are consistent with clinical guidelines that prioritize non-beta-blocker regimens and recommend using beta-blockers in the presence of compelling indications.
Related Concept Videos
 01:27
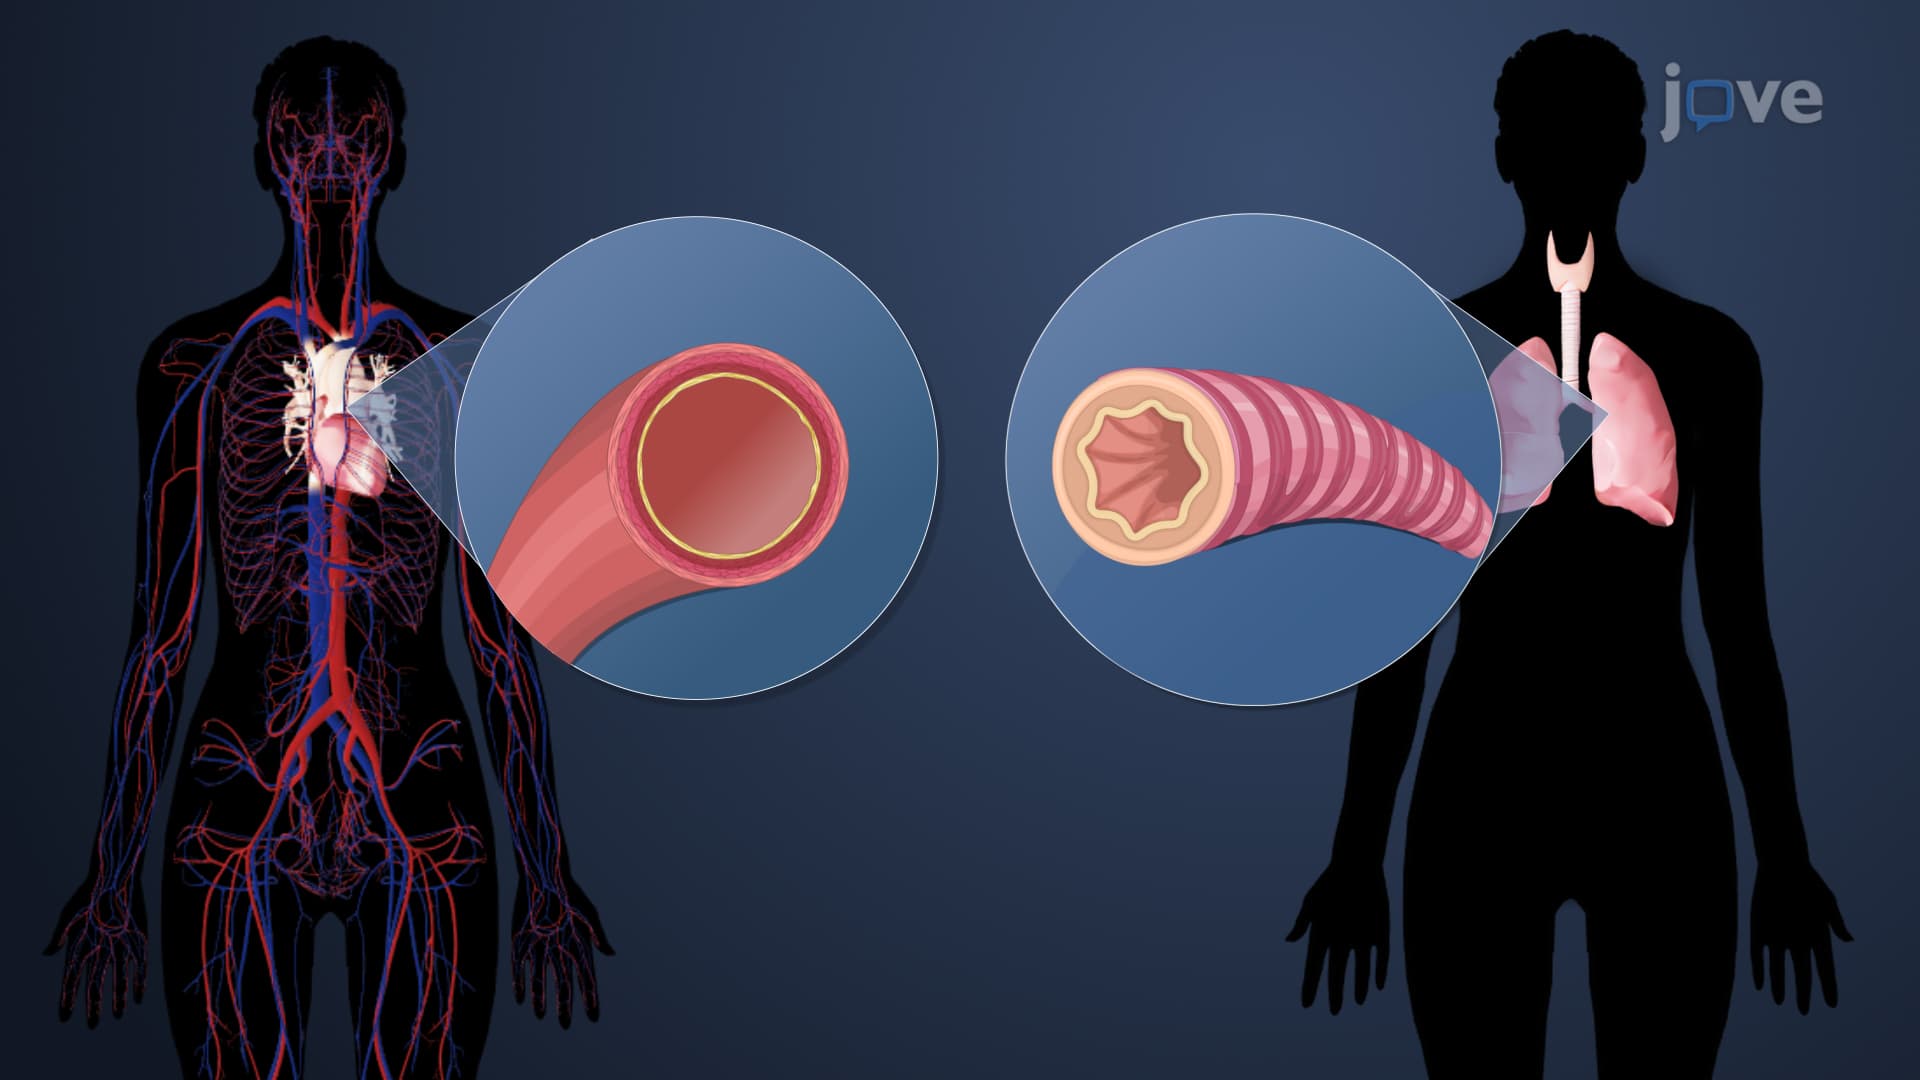
Adrenergic Antagonists: Pharmacological Actions of β-Receptor Blockers
 01:28
Antihypertensive Drugs: Types of β-Blockers
 01:31
Adrenergic Antagonists: ɑ and β-Receptor Blockers
 01:22
Heart Failure Drugs: β-Blockers
 01:17
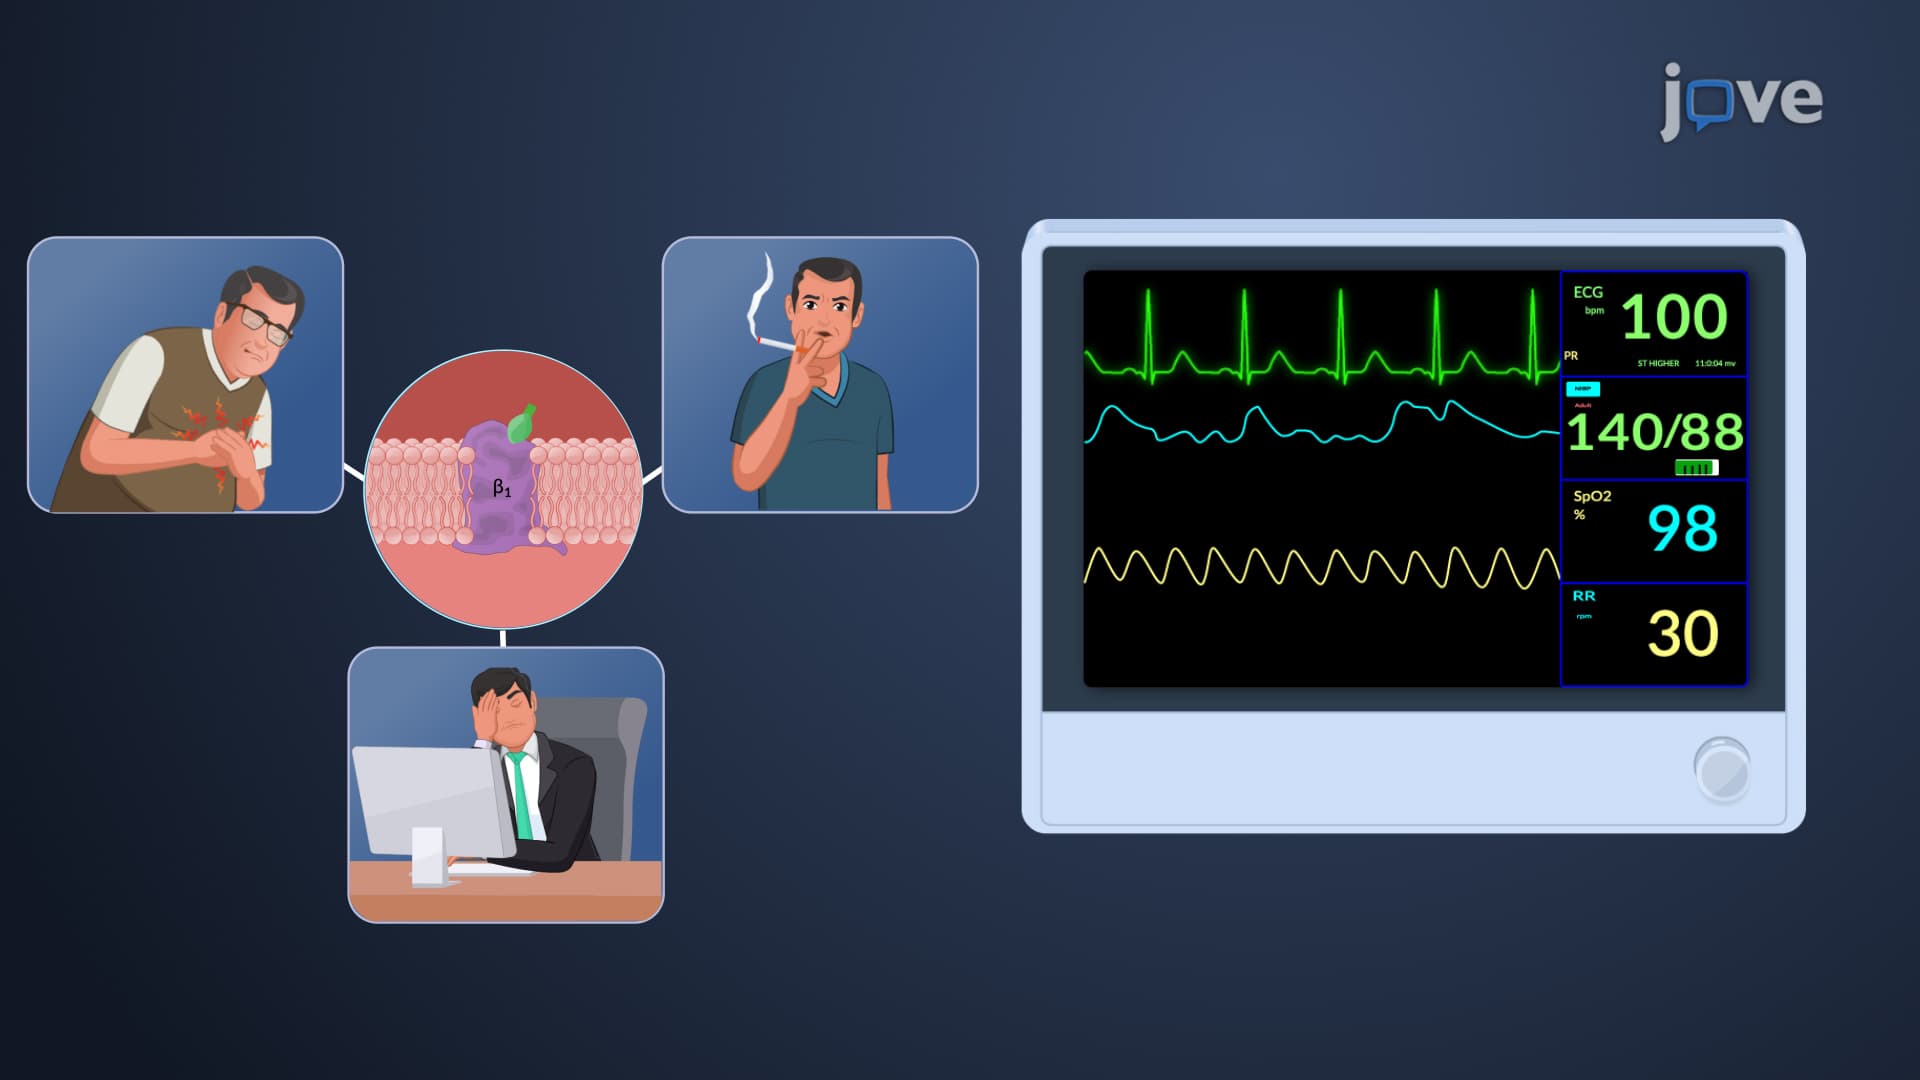
Antihypertensive Drugs: Action of β1 Blockers
 01:25
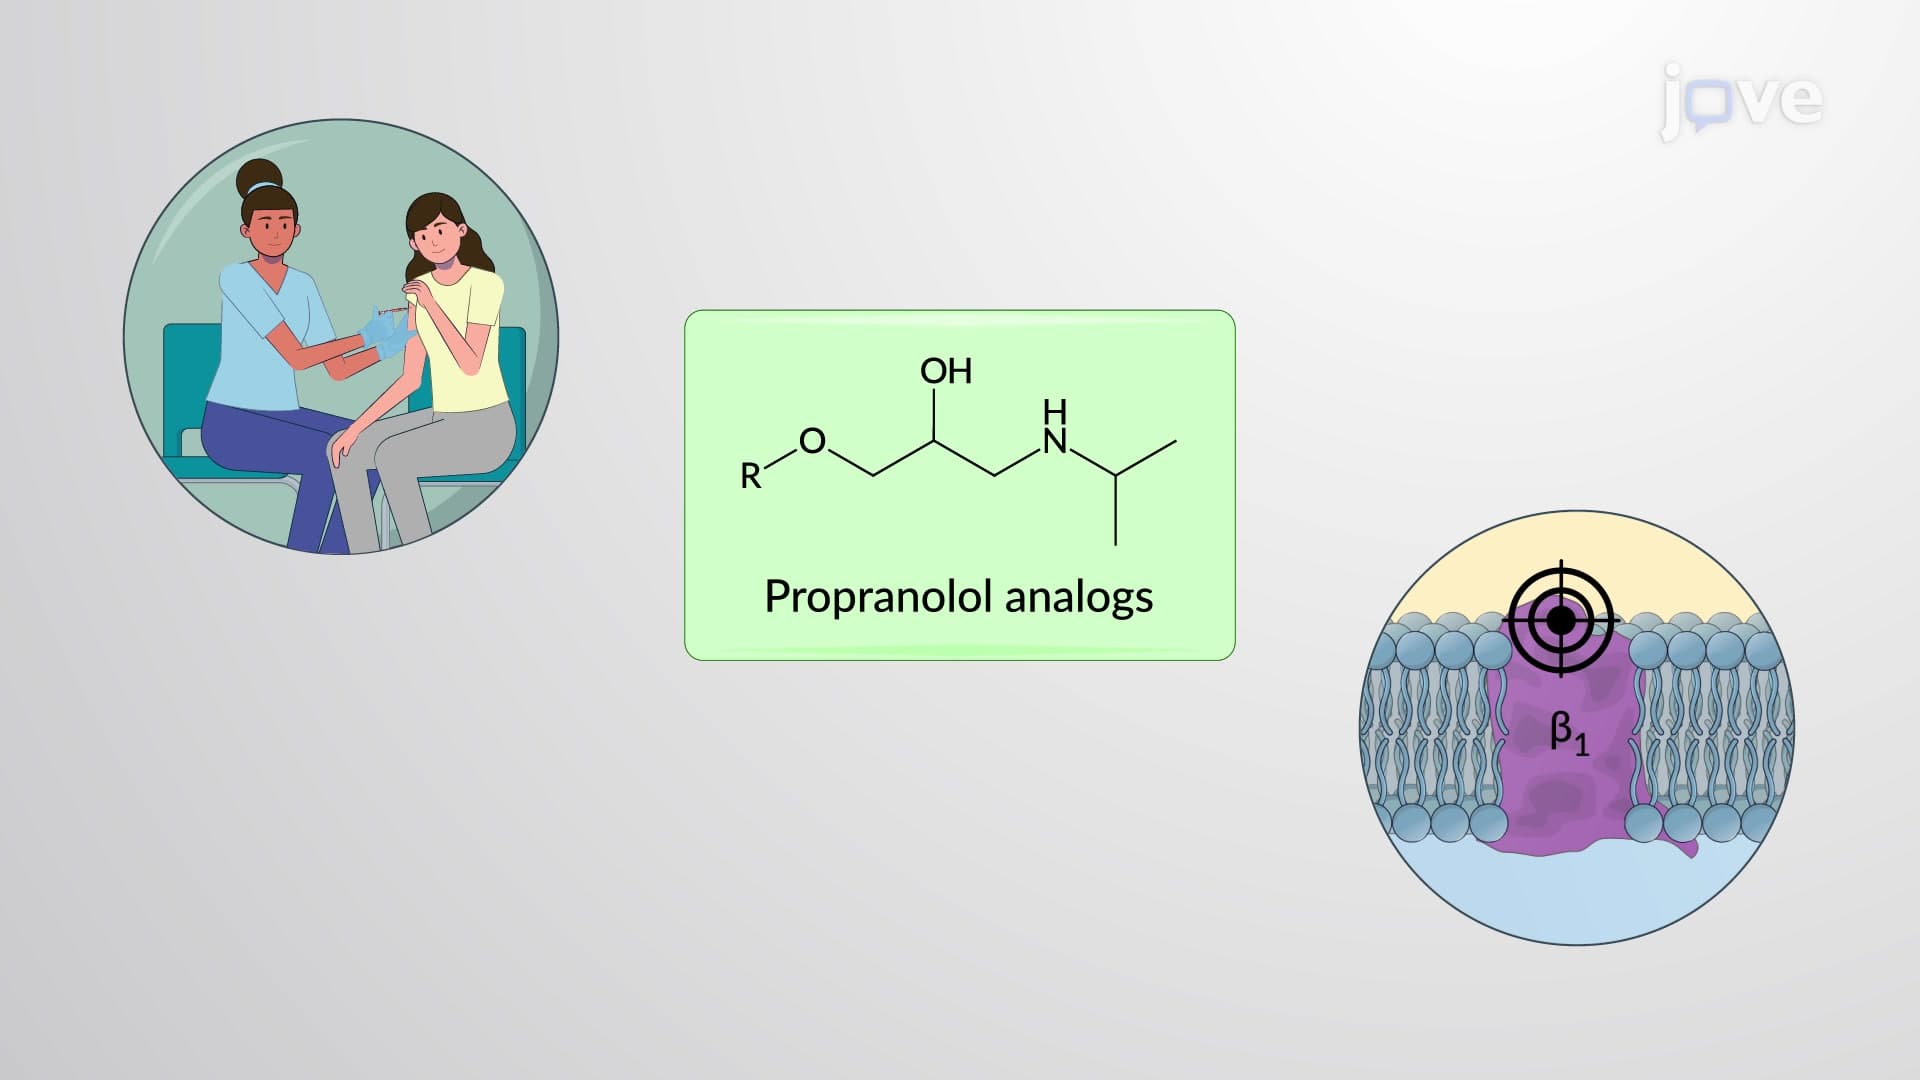
Adrenergic Antagonists: Chemistry and Classification of β-Receptor Blockers