Related Experiment Video
Updated: May 28, 2026
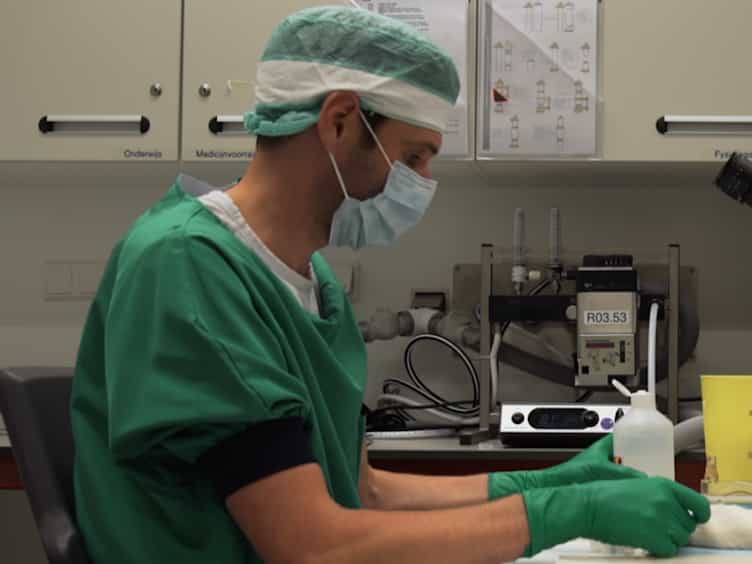

Shunt Surgery, Right Heart Catheterization, and Vascular Morphometry in a Rat Model for Flow-induced Pulmonary Arterial Hypertension
Published on: February 11, 2017
Contemporary Outcomes of Systemic-to-Pulmonary Shunt in Patients With Congenital Heart Disease: A Single-Center
Youngkwan Song1, Dong-Hee Kim1, Eun Seok Choi1
1Division of Pediatric Cardiac Surgery, Asan Medical Center, University of Ulsan College of Medicine, Seoul, Republic of Korea.

Background:
Systemic-to-pulmonary shunt (SPS) remains an essential palliative procedure for congenital heart disease. We assessed contemporary outcomes after SPS.
Methods:
We retrospectively reviewed 565 patients who underwent SPS with expanded polytetrafluoroethylene grafts between 2008 and 2023. Patients were stratified into 3 surgical eras to evaluate temporal trends: era 1, 2008-2013; era 2, 2014-2018; and era 3, 2019-2023.
Results:
Median age and body weight at SPS were 25 days and 3.44 kg, respectively. Target operations (TOs) were achieved in 478 patients (84.6%): biventricular repair (n = 272), bidirectional Glenn shunt (n = 178), one-and-a-half ventricle repair (n = 24), and transition to other types of palliation (n = 4). Loss to follow-up occurred in 15 patients; SPS remained in situ without further treatment in 3 patients. Mortality before TO occurred in 69 patients (12.4%), including 24 early deaths (4.6%). Pre-TO survival at 6 months improved significantly across eras, from 83% in era 1 to 94% in era 3 (P = .007). On logistic regression, early mortality was associated with a functionally single ventricle (odds ratio [OR], 3.13; P = .02), lower body weight at SPS (OR, 4.17; P = .002), and a sternotomy approach (OR, 21.75; P = .003). On Cox regression, pre-TO overall mortality was associated with a functionally single ventricle (hazard ratio [HR], 3.19; P < .001), pulmonary atresia (HR, 1.79; P = .04), pre-SPS cardiac surgery (HR, 2.40; P = .04), concomitant cardiovascular procedures at SPS (HR, 2.08; P = .004), and larger graft diameter to body weight ratio (HR, 1.13; P = .05). A higher dose aspirin protocol was protective (HR, 0.54; P = .02).
Conclusions:
Outcomes after SPS have improved in the contemporary era, likely reflecting advances in perioperative management.


Related Concept Videos
 01:22
Mitral Stenosis I: Introduction
 01:30
Pulmonary Hypertension: Classification and Pathogenesis
There are various classifications for PH, each relating to different underlying causes and also...