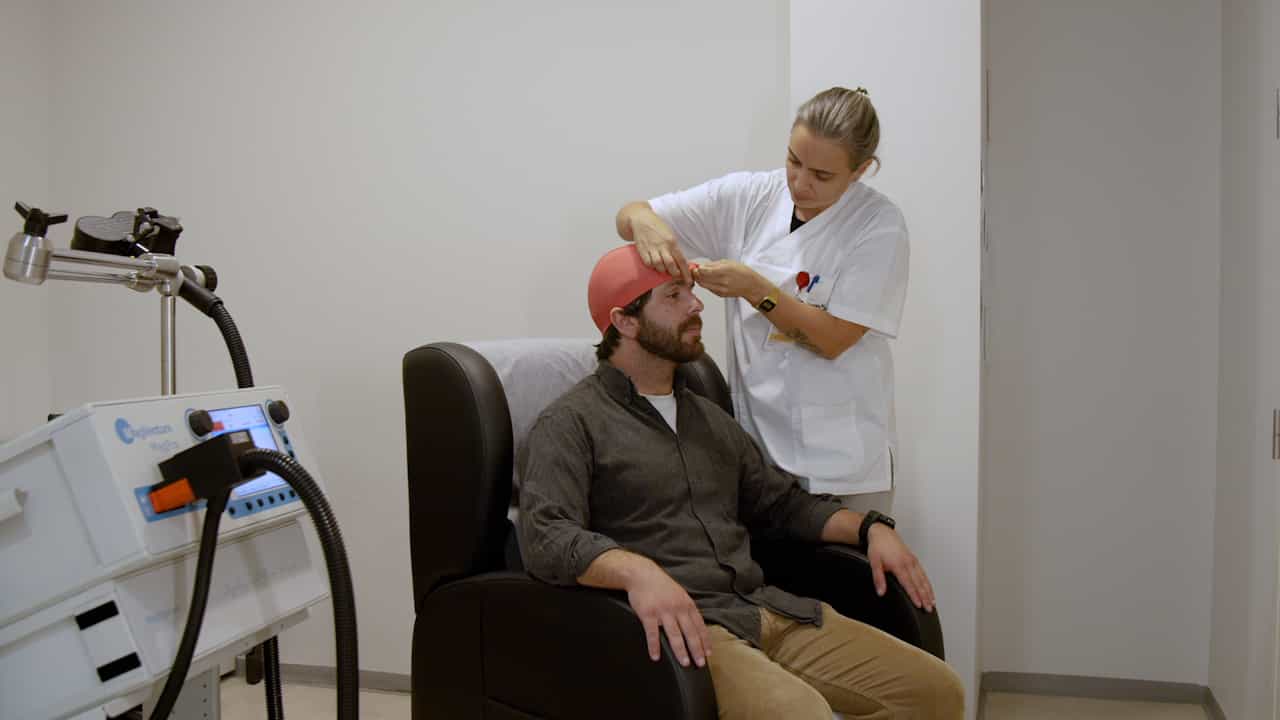
Related Experiment Video
Updated: May 28, 2026


MRI-guided dmPFC-rTMS as a Treatment for Treatment-resistant Major Depressive Disorder
Published on: August 11, 2015
Digital and repetitive transcranial magnetic stimulation interventions for perinatal depression and anxiety: a
Zahra Bostani Khalesi1, Mahmood Abedinzade2, Afshin Dalili3
1Biomedicine Research Center, Trauma Institute, Guilan University of Medical Sciences, Rasht, Iran.

Background:
Perinatal mood and anxiety disorders (PMADs) remain undertreated despite their prevalence and consequences. Digital psychological interventions and repetitive transcranial magnetic stimulation (rTMS) have been proposed as scalable or medication-sparing options. This systematic review evaluates the effectiveness of therapist-guided digital cognitive behavioral therapy (CBT) and rTMS for perinatal depression and anxiety, with separate synthesis of efficacy and safety evidence.
Methods:
We conducted a PRISMA 2020-guided systematic review of six databases (PubMed/Medline, Scopus, Web of Science, PsycINFO, Cochrane Central, Embase) from inception to 01 October 2025. Randomized controlled trials (RCTs), non-randomized trials, pilot studies, and case series were included. Case reports (n < 5) were excluded from efficacy analyses but retained for safety data extraction. Risk of bias was assessed using Cochrane RoB 2 and ROBINS-I. Narrative synthesis was necessitated by significant clinical and methodological heterogeneity; effect sizes are contextualized by baseline severity, comparator, and study quality.
Results:
Twenty-nine studies (23 RCTs, 6 non-randomized) were included. Therapist-guided digital CBT demonstrated moderate-to-large effects on depressive symptoms (between-group Hedges' g 0.5-1.4) in most, but not all, trials; certainty of evidence was moderate. Self-guided digital CBT yielded smaller, inconsistent effects (g = 0.2-0.6; low certainty). Digital mindfulness interventions showed pronounced heterogeneity: five guided, culturally adapted Eastern trials reported positive effects, while six unguided Western trials found no benefit (very low certainty). For rTMS, one small sham-controlled RCT (n = 26) provided very-low-certainty efficacy evidence. Uncontrolled studies (≈ 230 pregnancies) reported large pre-post improvements but are critically confounded and cannot establish efficacy. Safety data, while reassuring in the short term, derive from limited cumulative exposure (≈ 230 pregnancies); absence of observed harm is not equivalent to evidence of safety (low certainty).
Conclusions:
Therapist-guided digital CBT is a well-supported intervention and should be integrated into perinatal care. Self-guided digital CBT and mindfulness apps have limited or uncertain evidence. rTMS remains experimental; large, definitive RCTs are urgently needed. Safety evidence for rTMS is insufficient to draw firm conclusions.
Clinical Trial Number:
Not applicable.