Related Experiment Video
Updated: May 28, 2026
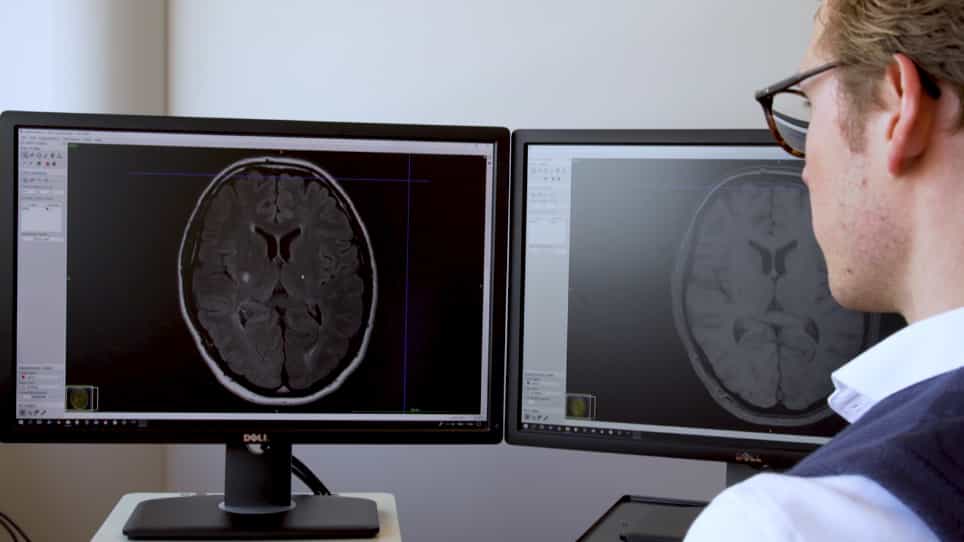

Brain Infarct Segmentation and Registration on MRI or CT for Lesion-symptom Mapping
Published on: September 25, 2019
Infarct Laterality Patterns in Relation to A1 Segment Hypoplasia/Aplasia According to Etiological Subtype
Junpei Nagasawa1, Tatsuhiro Yokoyama1, Ryuichi Okamoto1
1Department of Neurology, Toho University Faculty of Medicine, Tokyo 143-8541, Japan.

Insights
Anatomical variations in the Circle of Willis A1 segment, like hypoplasia or aplasia, did not show a significant link to stroke laterality in this study. Further research with larger sample sizes is needed to confirm these exploratory findings.
Area of Science:
- Neurology
- Vascular Neurology
- Neuroimaging
Background:
- The Circle of Willis (CoW) is crucial for collateral cerebral circulation.
- Anatomical variations, specifically A1 segment hypoplasia or aplasia, can impact cerebral hemodynamics.
- The role of these variations in cerebral infarction distribution is debated.
Purpose of the Study:
- To investigate the association between A1 segment hypoplasia/aplasia and infarct laterality.
- To analyze this association across different etiological stroke subtypes: lacunar, cardioembolic stroke (CES), and embolic stroke of undetermined source (ESUS).
Main Methods:
- Retrospective analysis of 198 patients with unilateral anterior circulation infarction.
- Assessment of the Circle of Willis using magnetic resonance angiography (MRA).
- Definition of A1 hypoplasia (<1 mm diameter) and aplasia (non-visualization); identification of minor (affected) and dominant (contralateral) sides.
Main Results:
- 30% of patients exhibited A1 hypoplasia or aplasia, with similar prevalence across lacunar, ESUS, and CES subtypes.
- Infarcts occurred on the A1 dominant side in 53% (lacunar), 55% (ESUS), and 75% (CES) of cases.
- The observed differences in infarct laterality did not reach statistical significance (p=0.43), likely due to limited sample size.
Conclusions:
- Prevalence of A1 segment hypoplasia/aplasia was consistent across studied stroke types.
- No statistically significant association was found between A1 variations and infarct laterality.
- Findings are inconclusive due to sample size limitations, suggesting the need for further hypothesis-generating research.
Abstract:
Background: The Circle of Willis (CoW) is a key collateral pathway that enables communication between the anterior and posterior cerebral circulations. However, anatomical variations in the A1 segment of the anterior cerebral artery, such as hypoplasia or aplasia, can alter hemodynamics and may compromise this collateral function. While incomplete CoW configurations have been linked to aneurysm formation and altered patterns of hemorrhage, their role in the distribution of cerebral infarctions remains controversial. We aimed to explore the association between A1 segment hypoplasia/aplasia and infarct laterality across different etiological subtypes. Methods: We retrospectively analyzed patients with unilateral anterior circulation infarction admitted between April 2017 and March 2023. The CoW was assessed by magnetic resonance angiography (MRA). A1 segment hypoplasia was defined as a segment diameter <1 mm, and A1 aplasia was defined as non-visualization on MRA. The side with hypoplasia or aplasia was defined as the minor side, and the contralateral side as dominant. We assessed whether infarction occurred on the minor or dominant side. Results: Among 198 patients with unilateral anterior circulation infarction classified as lacunar, cardioembolic stroke (CES), or embolic stroke of undetermined source (ESUS), 30% had A1 hypoplasia or aplasia, with similar prevalence across subtypes. Infarcts occurred on the A1 dominant side in 53% of lacunar, 55% of ESUS, and 75% of CES cases. Although this difference did not reach statistical significance (p = 0.43), it should be interpreted with caution given the limited sample size. Conclusions: The rates of A1 hypoplasia and aplasia were similar across stroke types. No statistically significant association was identified. The findings remain inconclusive given the limited sample size. These results should be considered exploratory and hypothesis-generating.

Related Concept Videos
 01:15
Ischemic Stroke ll: Pathophysiology
 01:29
Hemorrhagic Stroke ll: Pathophysiology
 01:15
Ischemic Stroke l: Introduction
 01:19
Acute Coronary Syndrome II: Pathophysiology and Clinical Manifestations
 01:28
Lateralization