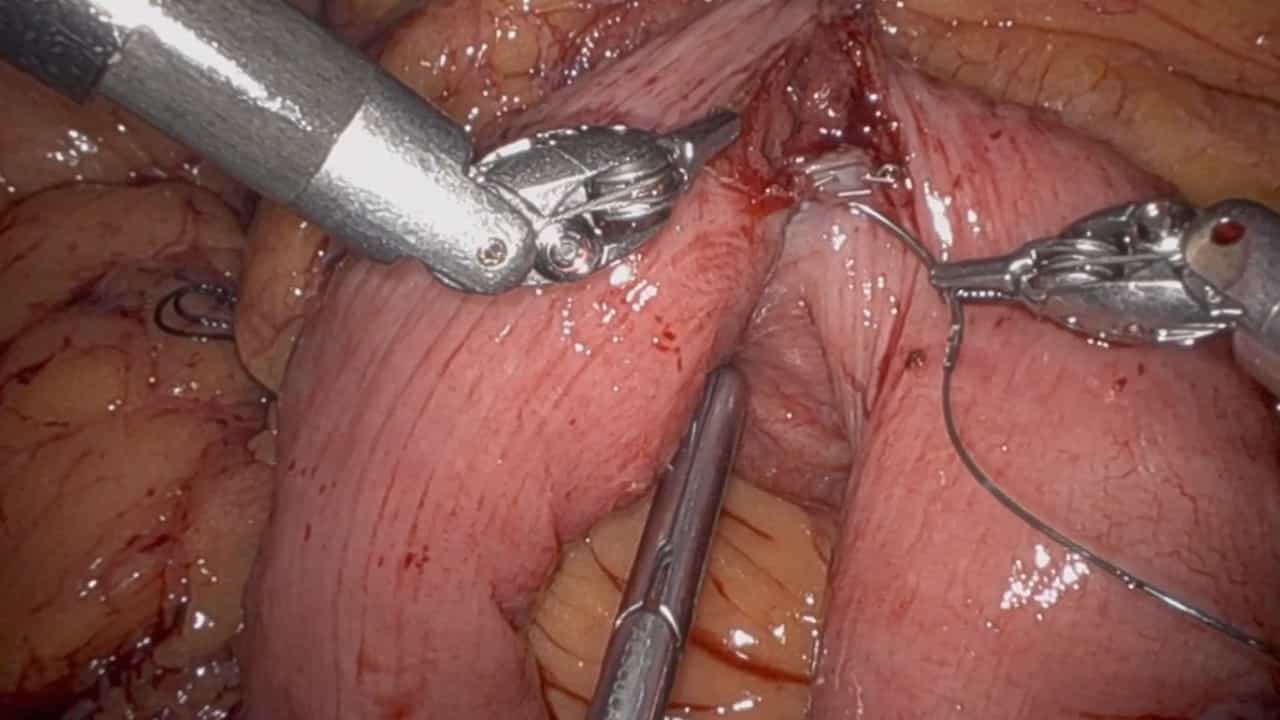
Perioperative Outcomes of No-Drain Strategy in Primary Repair of Perforated Peptic Ulcer: A Systematic Review and
Lorenzo Dell'Atti1, Maurizio Zizzo1, Andrea Morini1
1Surgical Oncology Unit, Azienda Unità Sanitaria Locale-IRCCS di Reggio Emilia, 42123 Reggio Emilia, Italy.

Insights
Omitting drains after perforated peptic ulcer (PPU) surgery may shorten hospital stays and reduce superficial infections. However, the evidence is low certainty, and potential increased mortality needs careful interpretation due to study biases.
Area of Science:
- Gastroenterology
- Surgical Innovation
- Evidence-Based Medicine
Background:
- Perforated peptic ulcer (PPU) is a surgical emergency.
- The necessity of drain placement after PPU primary repair remains debated.
- Existing evidence lacks conclusive guidance on drain use versus omission.
Purpose of the Study:
- To compare short-term outcomes of drain omission versus intra-operative drain placement after PPU primary repair.
- To provide meta-analytic insights into surgical strategies for PPU management.
- To evaluate the impact of drains on postoperative complications and length of stay.
Main Methods:
- Systematic review and meta-analysis following PRISMA guidelines.
- Searched PubMed, Web of Science, Cochrane Library, and Embase databases.
- Included RCTs and observational studies of adult PPU patients undergoing primary repair; excluded case reports/series <10 patients.
- Assessed risk of bias using Cochrane RoB 2.0 and ROBINS-I V2 tools; graded evidence certainty with GRADE.
Main Results:
- Five studies (1354 patients) were analyzed.
- Drain omission correlated with shorter length of stay (LOS) (MD -2.13 days) and fewer superficial surgical site infections (SSIs) (OR 0.24).
- No significant differences observed in leaks, reoperations, or deep SSIs. Low-certainty evidence suggested higher mortality with drain omission, likely due to bias in observational studies.
Conclusions:
- Drain omission may improve LOS and reduce superficial SSIs, particularly in lower-acuity PPU patients.
- Observed higher mortality in the no-drain group is of very low certainty and likely non-causal due to study biases.
- Further research is needed to confirm findings across the full PPU spectrum due to low evidence certainty and heterogeneity.
Abstract:
Background and Objectives: Perforated peptic ulcer (PPU) is an emergent condition managed by surgical intervention. No conclusive evidence has been produced regarding the need for drain placement after primary repair. Our meta-analysis aimed to provide insight into the short-term outcomes by comparing the two strategies of drain omission or intra-operative placement of at least one drain. Materials and Methods: We performed a systematic review following the PRISMA guidelines. PubMed/MEDLINE, Web of Science, Cochrane Library, and Embase databases were utilized to identify articles of interest. Meta-analysis was performed using RevMan Version 5.4. Eligible studies were comparative studies (RCTs and observational studies) enrolling adult patients (≥18 years) undergoing emergency primary repair for PPU, with or without prophylactic intra-abdominal drain placement; case reports and series of fewer than 10 patients were excluded. The literature search covered January 2010 to 22 February 2026. Risk of bias was assessed using the Cochrane RoB 2.0 tool for RCTs, and the ROBINS-I V2 tool for observational studies; certainty of evidence was graded using the GRADE framework. Pooled effect estimates were calculated using a random-effects model and expressed as odds ratios (OR) or mean differences (MD) with 95% confidence intervals (CI); statistical heterogeneity was quantified using the I2 statistic. Results: Five studies were considered for comparison, for a total of 1354 patients (744 and 610 in the drain and no-drain groups, respectively). Three were randomized controlled trials, and two were retrospective cohort studies, conducted across four countries (India, the USA, Egypt, and Japan). Meta-analysis of the pooled results showed that drain omission was associated with a shorter length of stay (LOS) (MD -2.13, 95% CI [-3.91--0.35], p < 0.0001) and a lower rate of superficial surgical site infections (SSIs) (16.7% vs. 52.7%, OR 0.24, 95%CI [0.11-0.55], p = 0.0007). No difference was observed regarding the rate of leaks, reoperation, or deep SSIs. Low-certainty evidence suggested higher postoperative mortality in the no-drain group (OR: 1.96; 95% CI: 1.10 to 3.48; p = 0.02; I2 = 0%), largely driven by retrospective studies with a high risk of bias. This mortality finding is of very low certainty and is most likely attributable to confounding in the observational studies rather than a true causal effect of drain omission. Several outcomes were based on data from only two to three studies, and the overall certainty of evidence was low to very low. Conclusions: Drain omission after primary repair for PPU may be associated with better outcomes in terms of LOS and superficial SSIs, primarily in lower-acuity patients, as reflected by the inclusion criteria of the contributing RCTs. Pooled analysis showed a higher postoperative mortality in the no-drain group; however, given the significant biases among included studies, our results should be interpreted as non-causal and thus require careful interpretation. Further research encompassing the full clinical spectrum of PPU is needed to confirm our results. Evidence certainty was low to very low across all outcomes, primarily due to a risk of bias, high heterogeneity (I2 up to 95% for LOS), indirectness, and imprecision.
Related Concept Videos
 01:25
Peptic Ulcer Disease V: Surgical Management and Nursing Care
Surgical Interventions for Peptic Ulcer Disease
 01:28
Esophageal Perforation-II: Clinical Manifestations and Management
Clinical Manifestations:
 01:26
Peptic Ulcer Disease IV: Management
The therapeutic approach involves ensuring adequate rest, implementing drug therapy, promoting smoking cessation, making dietary modifications, and emphasizing long-term follow-up care.
Pharmacological management
The prevailing therapy for peptic ulcers involves a combination of managing the patient's current medication...