Related Experiment Video
Updated: May 29, 2026
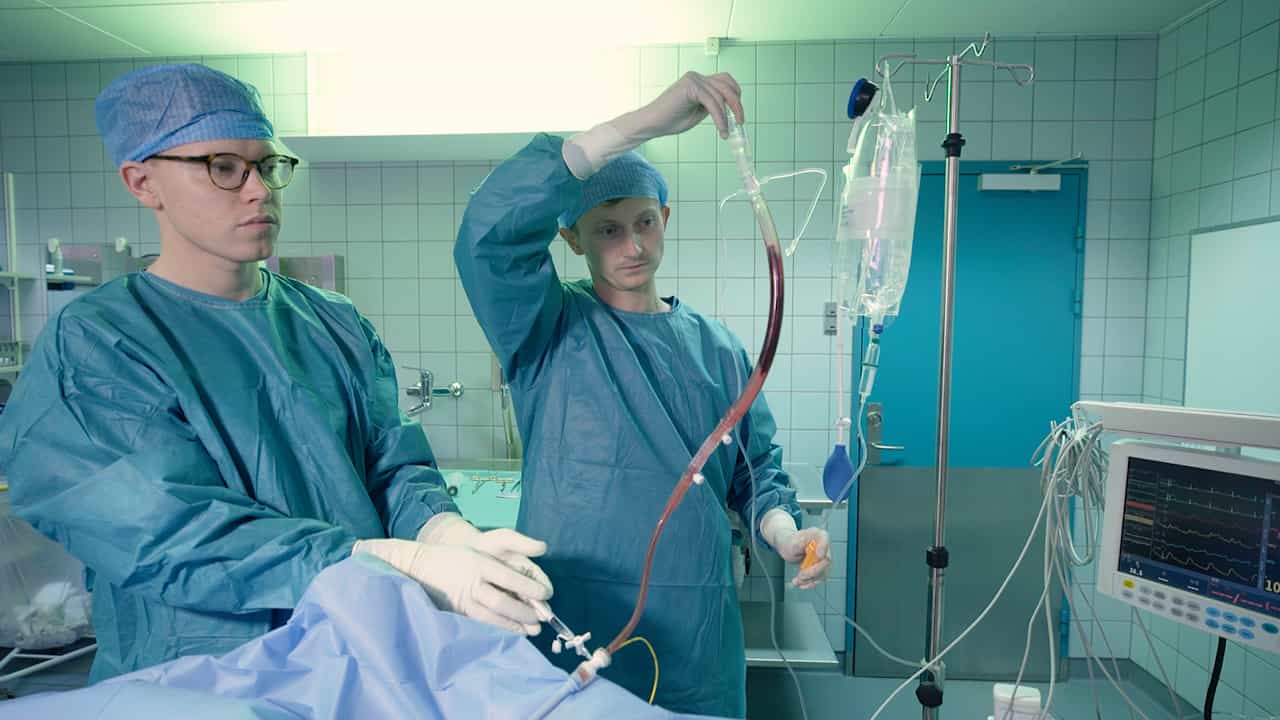

A Porcine Model of Acute Autologous Pulmonary Embolism
Published on: September 6, 2024
Unraveling the economics of pulmonary embolism care in a 23-year resource utilization study
Pablo Cuartas1, Claire Ferguson1, Danylo Orlov1
1Department of Surgery, State University of New York, Downstate Health Sciences University, Brooklyn, NY.

Background:
The systematic assessment of resource utilization in cost-intensive diseases such as pulmonary embolism (PE) is important to optimize health system efficiency. We examined the association between treatment modality, cost, and length of stay among inpatients diagnosed with PE.
Methods:
Using data from the National Inpatient Sample (1998-2021), we performed a retrospective trend analysis. Inpatient charges were converted to costs using the cost-to-charge ratio. Average cost differences between catheter-directed thrombolysis, anticoagulation, systemic thrombolysis, catheter-directed embolectomy, and surgical embolectomy were assessed using survey-weighted linear regressions, with hospital clustering. Differences in median length of stay, by treatment modality, were modeled using quantile regression.
Results:
The sample included 1,375,419 admissions; 1,338,332 (97.3%) received anticoagulation, 22,934 (1.7%) underwent systemic thrombolysis, 8363 (0.6%) underwent catheter-directed thrombolysis, 3453 (0.3%) underwent catheter-directed embolectomy, and 2337 (0.2%) underwent surgical embolectomy. Compared with catheter-directed thrombolysis, surgical embolectomy, catheter-directed embolectomy, and systemic thrombolysis were associated with higher average costs (surgical embolectomy, +$46,156; catheter-directed embolectomy, +$9042; systemic thrombolysis, +$3094, respectively; all P < .001); anticoagulation was less expensive ($9707 less expensive; P < .001). The median length of stay was longer after anticoagulation (+0.2 day), systemic thrombolysis (+1.4 days), and surgical embolectomy (+5.6 days; all P < .001). Catheter-directed embolectomy was associated with a shorter median length of stay (-0.6 day; P < .001).
Conclusions:
Substantial cost disparities exist among PE treatment modalities, spanning thousands of dollars. Although catheter-directed embolectomy was associated with the shortest median length of stay, the least expensive treatment modality was anticoagulation and the most expensive was surgical embolectomy. These insights offer guidance for optimizing resource allocation strategies in managing this prevalent postoperative complication.

Related Concept Videos
 01:29
Pulmonary Embolism II: Diagnostic Studies and Interprofessional Care
 01:27
Pulmonary Embolism III: Nursing Management
 01:19
Pulmonary Embolism I: Introduction
 01:29
Pulmonary Embolism I: Introduction
 01:29
Venous Thrombosis III: Interprofessional Care
 01:30
Venous Thrombosis IV: Nursing Management