Related Experiment Video
Updated: May 29, 2026
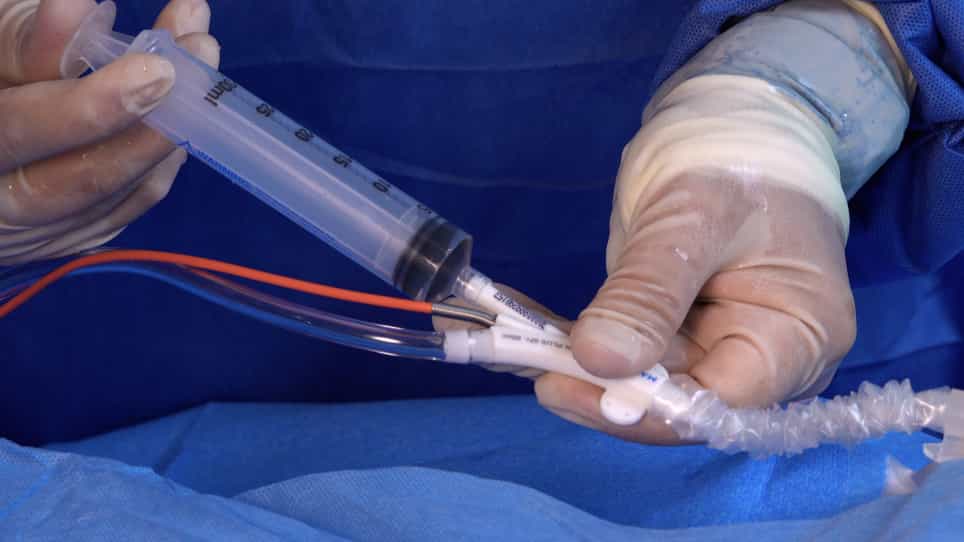

The Intra-Aortic Balloon Pump
Published on: February 5, 2021
Challenges of Intra-Aortic Balloon Pump and Extracorporeal Membrane Oxygenation in Cardiogenic Shock: Real-World
Wei-Ting Wang1,2,3, Chiu-Yang Lee2,3,4, Shao-Sung Huang1,2,3,5
1Division of Cardiology, Department of Internal Medicine, Taipei Veterans General Hospital.

Background:
The aim of this study was to assess the long-term outcomes of patients treated with intra-aortic balloon pump (IABP) alone and in combination with extracorporeal membrane oxygenation (ECMO), focusing on the real-world effectiveness and patient survival.
Objective:
To evaluate the effectiveness and survival outcomes of patients undergoing IABP support alone versus those receiving combined IABP and ECMO support in a tertiary care setting.
Methods:
We conducted a retrospective cohort analysis of 544 patients, of whom 362 received IABP support and 182 received combined IABP and ECMO support. The study was set in a tertiary care environment. Using Cox proportional hazard regression models, we examined biochemical, echocardiographic data, comorbidities, and medication histories to identify factors associated with mortality.
Results:
From January 2001 to June 2018 (median follow-up: 30 months), 544 patients received IABP with or without ECMO. Among the IABP-only group, non-survivors were older and had worse renal function, lower cholesterol, and more frequent cardiopulmonary resuscitation, pulseless electrical activity (PEA), ventricular tachycardia/ventricular fibrillation, and sepsis. Age and PEA independently predicted all-cause mortality (hazard ratio [HR]: 1.020 and 1.653, respectively), while age, peak creatine kinase, shock, and PEA were associated with cardiovascular (CV) death. In the IABP + ECMO group, mortality was similarly associated with older age, renal dysfunction, coronary artery disease, and PEA. After adjustment, age remained an independent predictor of all-cause (HR: 1.012) and CV mortality (HR: 1.014). Compared to IABP alone, the combination group had more critical illness features and higher adjusted risks of all-cause (HR: 1.827) and CV death (HR: 1.953).
Conclusions:
This study underscores the need for precise patient selection for advanced mechanical circulatory support, focusing on age and comorbidities. Our findings advocate for targeted management strategies to enhance the therapeutic potential of mechanical support in cardiogenic shock and improve survival rates among critically ill cardiac patients.

