Related Experiment Video
Updated: May 31, 2026
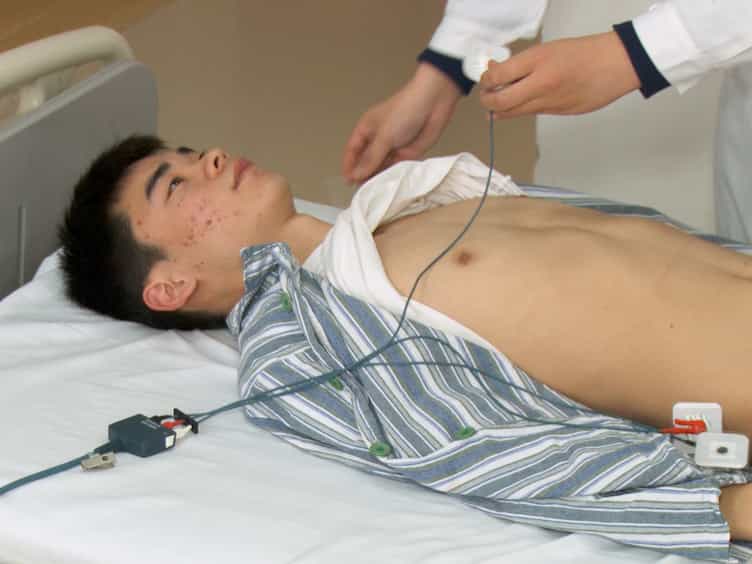
Measuring the Carotid to Femoral Pulse Wave Velocity (Cf-PWV) to Evaluate Arterial Stiffness
Published on: May 3, 2018
Global Divergence in Hypertension Standards: Cardiovascular Outcomes Under U.S. (≥130/80) Versus European/Chinese
Yilin Pan1, Jingru Bi2, Lili Sun1
1Department of Critical Care Medicine, Beijing Anzhen Hospital, Capital Medical University, Beijing, China.

Insights
The American hypertension guideline (ACC/AHA) identifies more people with high blood pressure but does not better predict cardiovascular disease risk compared to European/Chinese guidelines. Focus should be on continuous blood pressure monitoring for personalized risk assessment.
Area of Science:
- Cardiology
- Public Health
- Epidemiology
Background:
- Global debate exists on optimal hypertension diagnostic thresholds, with differing guidelines (ACC/AHA vs. European/Chinese).
- Comparative predictive utility of these hypertension criteria in diverse populations is not well understood.
- This study addresses the need for evidence-based hypertension diagnosis in multi-ethnic cohorts.
Purpose of the Study:
- To systematically compare the performance of American (ACC/AHA) and European/Chinese hypertension diagnostic criteria.
- To evaluate the predictive utility of different hypertension thresholds for incident cardiovascular disease (CVD).
- To assess clinical decision-making utility across diverse, real-world populations.
Main Methods:
- Prospective analysis of 10,120 participants (≥45 years) from CHARLS, HRS, and ELSA cohorts (2010-2018).
- Exclusion of individuals with prior CVD or antihypertensive medication use.
- Assessment of hypertension definitions using multivariable Cox models, time-dependent AUC, NRI, IDI, and Decision Curve Analysis.
Main Results:
- ACC/AHA criteria identified a larger hypertensive population (47.1%) versus European/Chinese (24.5%).
- Lower ACC/AHA threshold showed marginal statistical association with CVD but no superior clinical predictive utility.
- No significant differences in discrimination, risk reclassification, or net clinical benefit between the two guideline models were observed across cohorts.
Conclusions:
- The lower American hypertension threshold identifies more at-risk individuals but lacks superior predictive value for CVD.
- Findings challenge universal adoption of the lower threshold, suggesting limitations in current diagnostic cutoffs.
- Clinical focus should shift towards continuous blood pressure variables and personalized absolute cardiovascular risk assessment.
Introduction:
The optimal diagnostic threshold for hypertension remains debated globally, with American guidelines (American College of Cardiology/American Heart Association) recommending a lower threshold (≥130/80 mmHg) than European and Chinese guidelines (≥140/90 mmHg). This study systematically compared the predictive performance of these 2 standards in multiethnic cohorts.
Methods:
This prospective multicohort study analyzed harmonized data from 10,120 participants aged ≥45 years without prior cardiovascular disease or antihypertensive medication use from 3 nationally representative cohorts: the China Health and Retirement Longitudinal Study, the U.S. Health and Retirement Study, and the English Longitudinal Study of Ageing. Data were collected from 2010 to 2018 and analyzed in 2025. Multivariable Cox proportional hazards models assessed associations between hypertension definitions and incident cardiovascular disease. Predictive performance was evaluated using time-dependent area under the curve, net reclassification improvement, integrated discrimination improvement, and decision curve analysis.
Results:
The American College of Cardiology/American Heart Association criteria classified more individuals as hypertensive than the European/Chinese standard (47.1% vs 24.5%). Although the lower threshold showed a marginally stronger statistical association with incident cardiovascular disease, this did not translate into improved predictive utility. No significant differences were found in discrimination (6-year area under the curve=0.657 vs 0.656), risk reclassification (p>0.05), or net clinical benefit. Findings were consistent across all 3 cohorts.
Conclusions:
The lower American hypertension threshold identifies more at-risk individuals but fails to demonstrate superior predictive value or net clinical benefit. Clinical focus should shift toward integrating blood pressure as a continuous variable within personalized cardiovascular risk assessments.

Related Concept Videos
 01:30
Hypertension III: Clinical Manifestations and Diagnostic Studies
 01:28
Hypertension I: Introduction
 01:15
Assessment of blood pressure in brachial artery(one-step method)
Prepare for the Procedure:
 01:10
Pre-Procedural Guidelines for Assessing Blood Pressure
 01:29
Hypertension II: Pathophysiology
 01:18
Hypertension and Regulation of Blood Pressure