Related Experiment Video
Updated: May 31, 2026
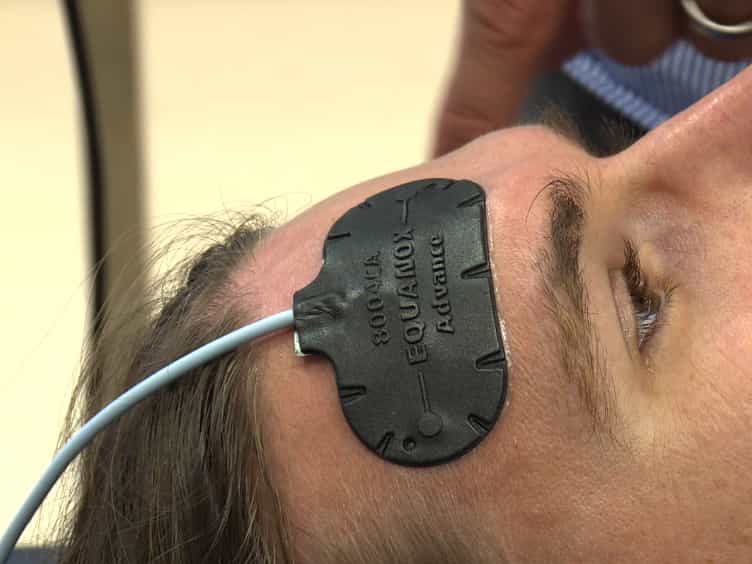
A Model to Simulate Clinically Relevant Hypoxia in Humans
Published on: December 22, 2016
A comparative evaluation of accuracy and response time in ear and finger pulse oximetry during repeated maximal
Antonis Elia1, Michail E Keramidas2
1Division of Environmental Physiology, Department of Physiology and Pharmacology, Karolinska Institute, Stockholm, Sweden.

Introduction:
Pulse oximetry is widely used to monitor training intensity and define safety termination thresholds during breath-hold-related activities, yet its accuracy and response time vary by measurement site, reflecting inherent physiological differences between locations, such as perfusion and vascular tone. Because these physiological variables are markedly altered during breath-holding, this study investigated differences in pulse oximetry dynamics between central (ear) and peripheral (finger) sites during repeated maximal breath-holding.
Methods:
Forty healthy subjects performed three repeated maximal static breath-holds separated by 2-min rest intervals. Finger and earlobe SpO2, systemic cardiovascular variables, and gas exchange were assessed.
Results:
Breath-holds were terminated at progressively lower end-tidal oxygen and SpO2, and higher end-tidal carbon dioxide, arterial pressures, and cardiac output across successive attempts (p ≤ 0.003). SpO2 values at both the breaking point and nadir were consistently higher at the finger than at the earlobe (breaking point: +9-15%; nadir: +7-11%;p ≤ 0.008), with the inter-site differences being amplified across successive attempts (p ≤ 0.012). Finger SpO2 remained significantly higher at breaking point than at the nadir (+4-8%;p < 0.001), whereas no such differences were noted at the ear (p = 0.619). The time to reach SpO2 nadir was longer at the finger than at the earlobe (18-23 s;p < 0.001) and was extended across attempts only at the finger (from 27 s to 32 s;p < 0.001). Breath-hold duration correlated with the inter-site SpO2 differences at breakpoint (r = 0.53;p < 0.001).
Conclusions:
Compared to earlobe measurement, finger pulse oximetry exhibited a consistent temporal delay, and systematically underestimated the severity of hypoxaemia. This divergence increased with longer breath-holds, indicating a duration-dependent amplification of the inter-site SpO2-measurement differences.
More Related Videos
 14:28
Non-Invasive Monitoring of Microvascular Oxygenation and Reactive Hyperemia using Hybrid, Near-Infrared Diffuse Optical Spectroscopy for Critical Care
Published on: May 10, 2024
 08:35
Oxygenation-sensitive Cardiac MRI with Vasoactive Breathing Maneuvers for the Non-invasive Assessment of Coronary Microvascular Dysfunction
Published on: August 17, 2022
Related Concept Videos
 01:24
Pulse Oximetry
Purpose
Average SpO2 values are greater than 95%. If the readings fall below 90%, it indicates that...
 01:19
Guidelines For Measuring Vital Signs
Before taking a patient's vital signs, a nurse would consider and assess the patient's comfort level and ensure appropriate equipment is available.
 01:19
Special considerations while measuring oxygen saturation
Ensuring accuracy in vital sign recordings while prioritizing patient comfort and minimizing anxiety is important.
 01:21
Sites for measuring blood pressure
The Brachial Artery: Primary Site for Blood Pressure Measurement
 01:17
Measurement of Blood Pressure
 01:28
Special considerations while measuring blood pressure
Monitoring Both Arms:
Monitoring BP in both arms during the initial assessment is advisable, as the systolic value may differ by five to ten mm Hg between arms. For subsequent BP assessments, use the arm with the higher reading.