Related Experiment Video
Updated: May 31, 2026
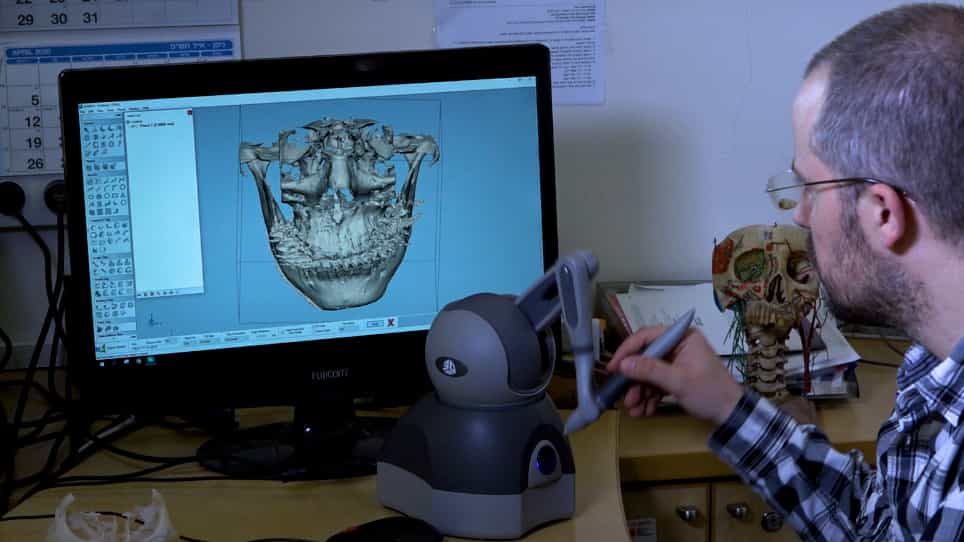

Treatment of Facial Deformities using 3D Planning and Printing of Patient-Specific Implants
Published on: May 23, 2020
Comparative Analysis of Hospital Charges in Infants With Robin Sequence: Nonsurgical Orthodontic Airway Plate Versus
Kelsi N Krakauer1,2, Christopher R Forrest3,4, Joo-Young Park5
1Department of Surgery, Division of Plastic and Reconstructive Surgery, Stanford University School of Medicine, Lucile Packard Children's Hospital Stanford, Palo Alto, CA, USA.

Insights
Nonsurgical orthodontic airway plates (OAP) significantly reduce hospital charges for infants with Robin sequence compared to surgical mandibular distraction osteogenesis (MDO). OAP treatment also leads to shorter hospital stays, accelerating patient recovery and discharge.
Area of Science:
- Pediatric Otolaryngology
- Craniofacial Surgery
- Health Economics
Background:
- Robin sequence (RS) presents significant airway challenges in infants, often requiring complex interventions.
- Current treatment paradigms include nonsurgical and surgical approaches, each with distinct resource implications.
- Evaluating the cost-effectiveness of these treatments is crucial for optimizing patient care and hospital resource allocation.
Purpose of the Study:
- To compare the total hospital charges associated with two primary airway treatments for infants diagnosed with Robin sequence (RS).
- To assess the impact of nonsurgical Stanford orthodontic airway plate (OAP) versus surgical mandibular distraction osteogenesis (MDO) on healthcare costs and hospital resource utilization.
- To determine the cost-effectiveness of OAP as a high-value treatment modality for RS.
Main Methods:
- Retrospective cohort study design analyzing data from a single quaternary pediatric hospital.
- Inclusion criteria: Infants with RS admitted for airway treatment between January 2016 and April 2023.
- Comparison of hospital charges (inflation-adjusted to 2024 USD) between infants treated with OAP and those treated with MDO, from admission to discharge.
Main Results:
- A cohort of 13 OAP-treated and 9 MDO-treated infants was analyzed. Median hospital stay was significantly shorter for OAP (15 days) compared to MDO (23 days) (P=.003).
- Median intensive care unit (ICU) stay was markedly reduced with OAP (3 days) versus MDO (14 days) (P<.001).
- Total inflation-adjusted hospital charges were substantially lower for OAP ($683,549.20) compared to MDO ($1,269,670.00), a 46.2% reduction (P=.006).
Conclusions:
- Nonsurgical OAP treatment demonstrates a significant potential to reduce overall hospital charges for infants with Robin sequence.
- OAP facilitates a faster transition home, indicating improved efficiency and potentially better patient outcomes compared to MDO.
- OAP represents a high-value treatment option, optimizing clinical results and hospital resource allocation for Robin sequence management.
Abstract:
ObjectiveTo compare hospital charges associated with 2 airway treatments in infants with Robin sequence (RS)DesignRetrospective cohort study.SettingSingle quaternary pediatric hospital.PatientsInfants with RS admitted for treatment between January 2016 and April 2023InterventionsNonsurgical Stanford orthodontic airway plate (OAP) or surgical mandibular distraction osteogenesis (MDO)Main Outcome MeasuresHospital charges from admission to discharge, categorized and inflation-adjusted to 2024 United States DollarsResultsThirteen OAP-treated and nine MDO-treated infants were included. All infants were discharged home. Median age (minimum, maximum) at index admission was 38 days (1, 89) in OAP and 18 days (1, 65) in MDO. Median total hospital stay was 15 days (8, 26) in OAP and 23 days (12, 40) in MDO (P = 0.003). This included intensive care unit (ICU) stays of 3 days (0, 6) in OAP and 14 days (4, 21) in MDO (P < 0.001). Median total inflation-adjusted hospital charges were significantly lower in OAP ($683,549.20; interquartile range (IQR): $567,075.90 - $821,018.30) compared to MDO ($1,269,670.00; IQR: $932,087.50 - $1,573,712.00; P = 0.006), representing a 46.2% reduction. Non-ICU stay, ICU stay, and professional services were the top three contributors to the total hospital charges in OAP, while ICU stay, non-ICU stay, and operating room utilization were those in MDO during index admission.ConclusionsNonsurgical OAP has the potential to reduce hospital charges and accelerate the transition home compared to MDO, serving as a high-value treatment modality for optimizing both clinical outcomes and hospital resource allocation.
